Flatfoot: post-operative pathway after arthroereisis with Achilles lengthening
Pathway after arthroereisis with Achilles tendon lengthening: a below-knee cast for about 30 days as prescribed, followed by gradual recovery of movement and strength within authorised limits.
Cast for the prescribed period · Motion after removal and clearance · Strengthening after recovery and clearance · Running and sport based on criteria and review
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Changing phase restores its full exercise list. Timing alone does not determine the phase.
Exclude exercises if needed
14 of 14 exercise cards included
The full web page remains available. Your selection is not saved or shared.
This protocol is part of the post-operative pathway and must be adapted to the surgeon’s instructions and to the individual clinical response.
These documents are protocol templates for information and education only: they do not replace the rehabilitation prescription for the individual case. Timing, loading and progressions must always be adapted to the patient, the lesion pattern, the surgical technique used and the clinical course, in collaboration between orthopaedic surgeon, physiotherapist and, where appropriate, physiatrist. Progression is driven by objective criteria, not by the calendar alone.
At a glance — the full pathway
- Weight bearing
- During casting, use two crutches and a cast shoe only with the weight bearing specified at discharge. After removal, progress only as authorised and reduce aids when gait is controlled.
- Active mobilisation
- During casting, move only permitted free joints. After removal and review, perform the authorised active ankle movements without forcing the hindfoot. Follow the duration and frequency set by the physiotherapist.
- Passive mobilisation
- After cast removal, only if stretching has been authorised: perform the manoeuvre demonstrated by the physiotherapist within the prescribed range and dose. Do not tension a tendon repair that still requires protection.
- Surgical wound
- Follow discharge instructions for dressings and washing. Keep the wound protected and dry as directed; do not apply unprescribed antiseptics or creams. Washing and scar massage require a fully closed wound and clinician approval.
- Running and jumping
- Running and jumping from month 2, only with restored dorsiflexion and a possible heel raise.
- Return to sport
- Sport at 2-3 months, conditional on triceps surae strength recovery (single-leg heel raise).
- Night splint
- If prescribed, a night splint or brace for a further 30 days after cast removal. Use and adjust it only as taught.
Subtalar arthroereisis mechanically limits some hindfoot movements using an implant. Implant type, associated procedures and healing determine the postoperative pathway. The times below are indicative: follow the surgeon’s written instructions for the individual procedure.
Step by step
Each phase offers exercise options: perform only those selected by your clinician, without bringing later phases forward or automatically adding earlier exercises. Dosage, frequency and rests are individualised; the complete catalogue is not a single session.
Before surgery — Preparation for surgery
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
When it applies
- •Before elective arthroereisis (with or without associated procedures).
- •A standard course of preoperative physiotherapy has not been shown to improve the outcome of arthroereisis: preparation is mainly educational and organisational.
Goals before surgery
- •Understand the planned post-operative weight bearing and be able to use crutches.
- •Organise home and school for the first weeks.
- •Check baseline foot and ankle mobility and strength, where useful.
- •Know when motion starts and its limits for the specific procedure: with a cast, no ankle mobility until removal and movement clearance.
- •Know that after Achilles lengthening calf strength returns gradually and this must be respected.
Activities
- •Practical crutch training before surgery, on level ground and stairs.
- •Home and school organisation: pathways, bathroom, transport, accessible desk, temporary PE exemption.
- •Where useful, simple ankle and foot mobility exercises, without turning preparation into a mandatory programme.
Preoperative exercises
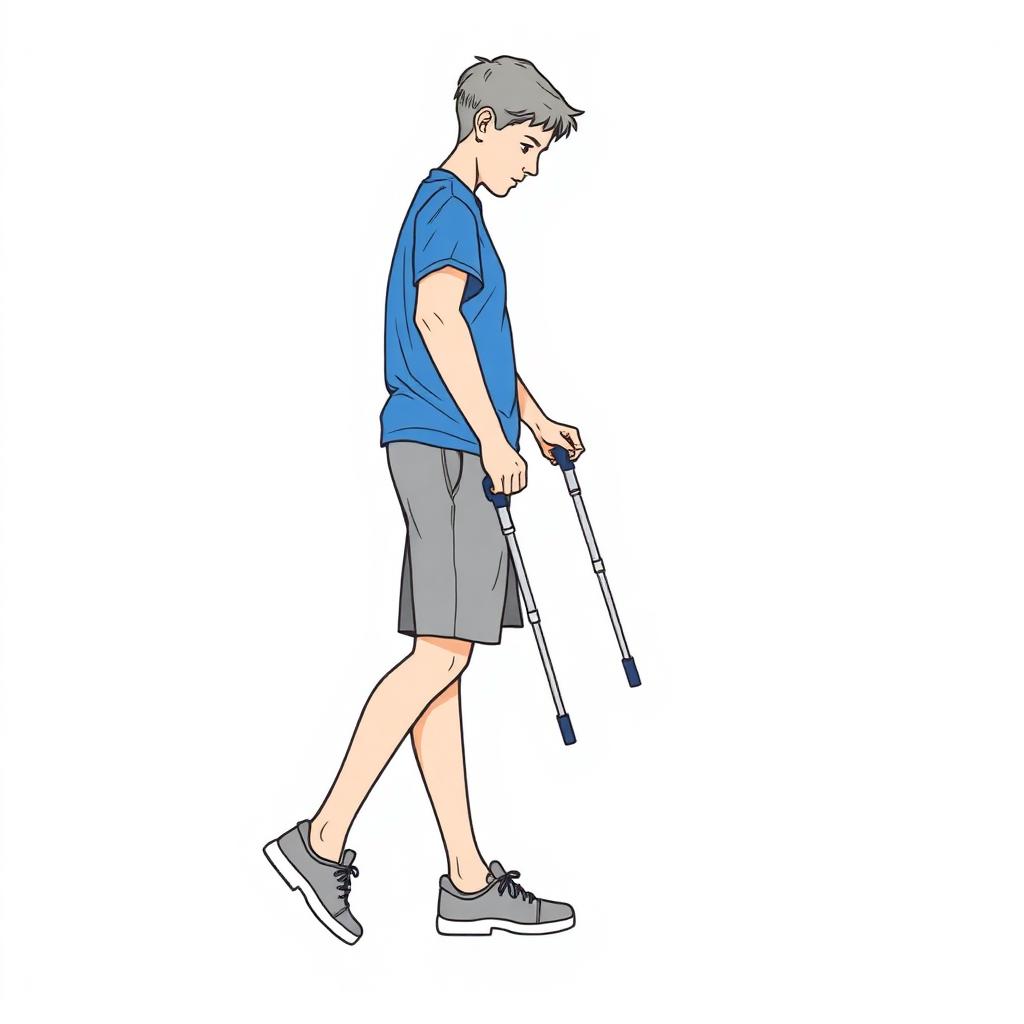
Crutch and weight-bearing training
- •Try the crutches before surgery, with correct height and the weight-bearing status set by the surgeon.
- •Practise on level ground, stairs and the entrance to your home, with someone assisting.
- •Also practise sitting, standing and moving in the bathroom while respecting the planned loading restrictions.
Dosage: At least one training session before admission; repeat until the technique is safe.
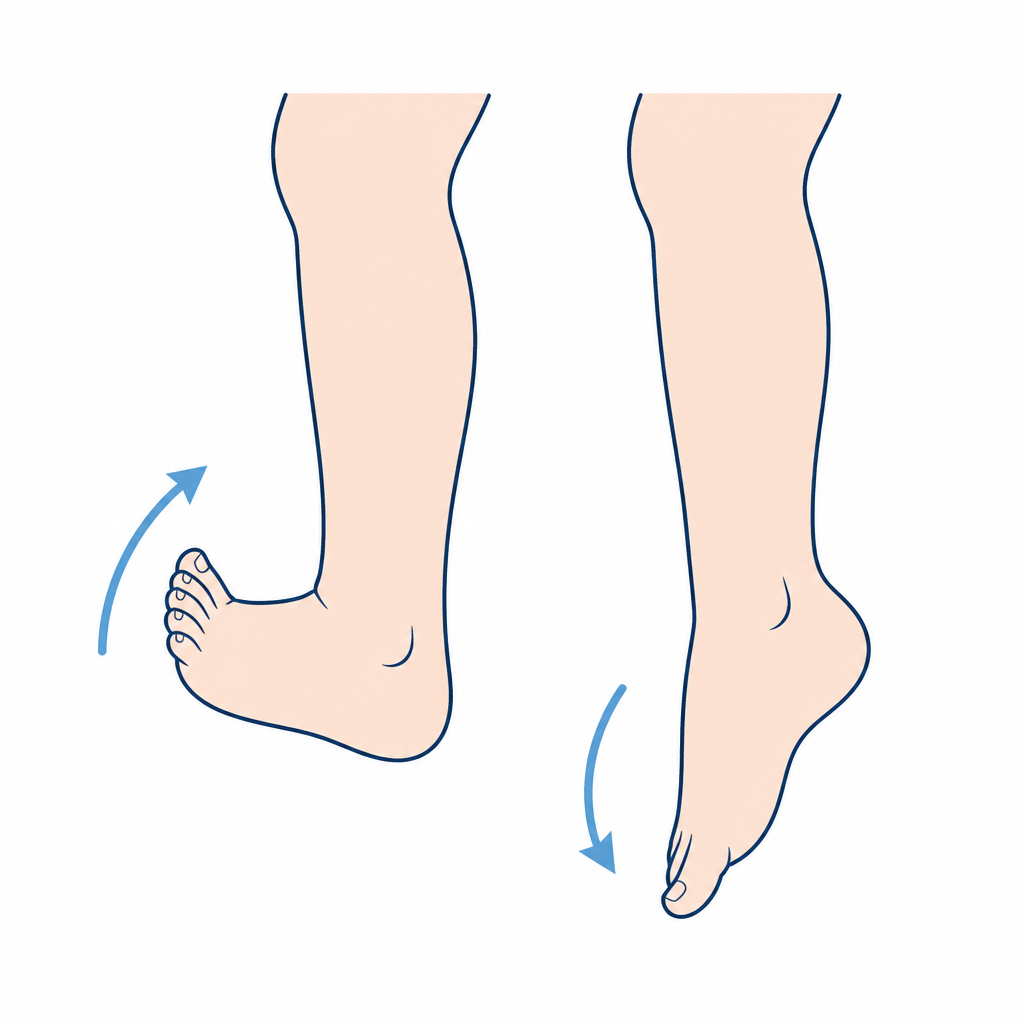
Active ankle mobility
- •Seated or lying, move the ankle into flexion, extension and slow circles, within the pain-free range.
- •Keep the movement smooth, without forcing the painful end range.
Dosage: Indicative: 10-15 movements per direction, 2-3 times a day.
Readiness criteria for surgery
- ☐Safe crutch use with the planned weight bearing.
- ☐Family informed about weight bearing, crutch use and return to school.
- ☐Home and school organised for the return after surgery.
When surgery must not be delayed
- •Preparation is not a prerequisite: elective surgery should not be postponed to complete preoperative exercises.
What to prepare at home and school
- •Prepare clear pathways, a place to keep the foot elevated and comfortable wide shoes for the return home.
- •Check stairs, bathroom and school transport with crutches.
- •Inform the school: expected absence, accessible desk, temporary PE exemption.
Phase 1 — First 72 hours: swelling, pain and cast care
Indicative timing: Days 0-3
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Control swelling and pain
- •Protect the wound and the cast
- •Maintain toe, knee and hip motion
What to do
- •Limb elevated above heart level whenever sitting or lying, as much as possible in the first 72 hours
- •Ice pack over the cast at the operated site, 15-20 minutes, 4-6 times a day
- •During casting, use two crutches and a cast shoe only with the weight bearing specified at discharge. After removal, progress only as authorised and reduce aids when gait is controlled.
- •Move free toes and activate the quadriceps as instructed. Calf contractions in the cast only if specifically prescribed; do not push against immobilisation.
- •Free knee and hip mobilisation to avoid stiffness and proximal weakness
- •Analgesia as prescribed
Restrictions and precautions
- •Keep the cast dry; never insert objects inside to scratch
- •No full weight bearing without crutches
- •Contact the surgeon if the cast feels tight, breaks or rotates
Exercises for this phase
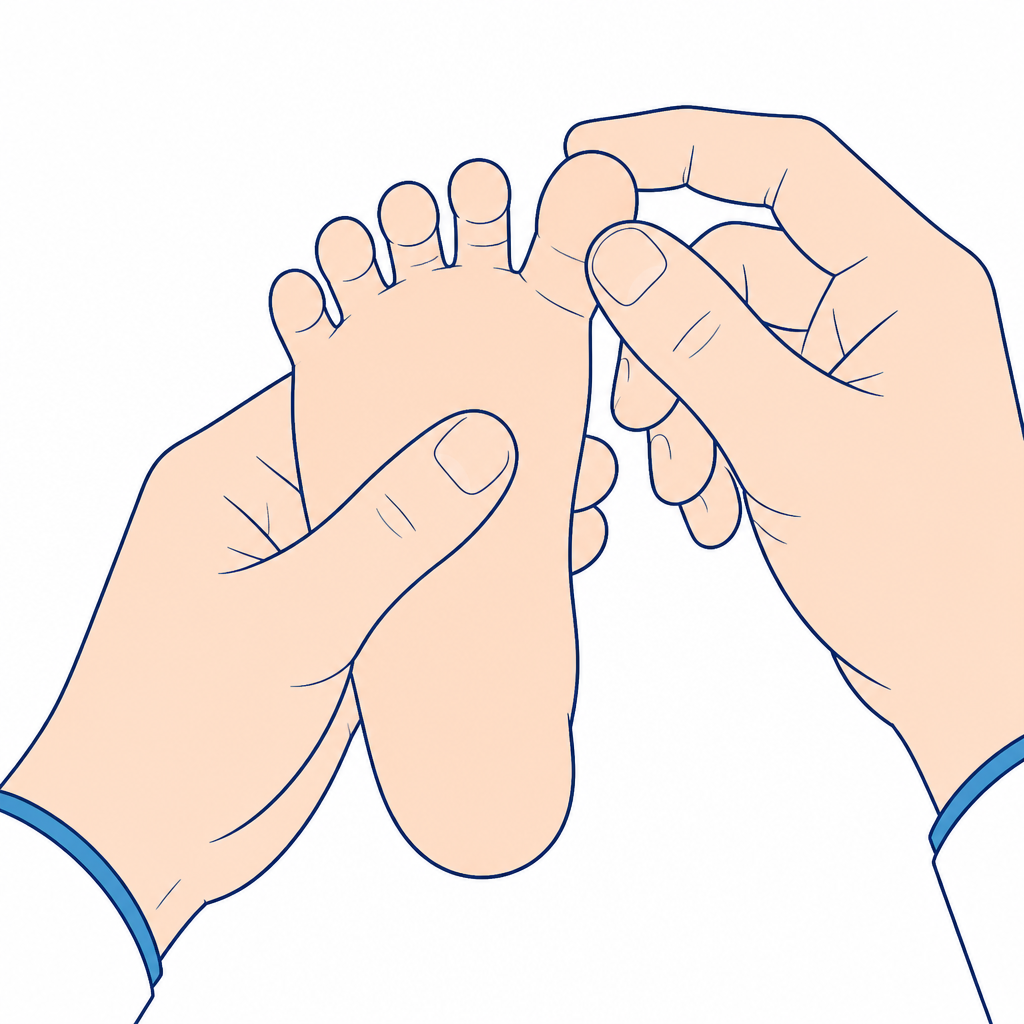
1. Toe mobilityAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Open and close the toes, then try to lift only the big toe and then only the others.
- •If a cast is in place, still move the toes that remain free.
- •It is the simplest way to activate the venous pump and reduce swelling.
Dosage: 20 repetitions, 5-6 times a day
Ready for the next phase when
- ☐Pain controlled
- ☐Toes pink, warm and mobile
- ☐Swelling decreasing with elevation and ice
Note for the physiotherapist
In this phase the physiotherapist educates the family: elevation, ice, correct crutch use, toe motion and cast surveillance.
Phase 2 — Immobilisation period (below-knee cast ~30 days)
Indicative timing: From day 4 to about day 30
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Allow healing of the operated tissues
- •Maintain knee, hip and toe strength and mobility
- •Walk safely with crutches
What to do
- •Walk with two crutches and a cast shoe only within authorised weight bearing; a cast shoe does not automatically permit loading.
- •Move free toes and activate the quadriceps as instructed. Calf contractions in the cast only if specifically prescribed; do not push against immobilisation.
- •Knee and hip exercises (flexion-extension, side-lying abduction) to maintain tone
- •Compatible aerobic activity: upper limbs, trunk, cycling with the contralateral limb
- •Scheduled review of wound and cast
Restrictions and precautions
- •No ankle mobilisation while the cast is in place
- •Keep the cast dry
- •No full weight bearing without crutches
No additional exercise cards are assigned here. Follow this phase’s indications and the programme selected by your physiotherapist; do not automatically continue or progress every previous exercise.
Ready for the next phase when
- ☐Healed wound at review
- ☐No sign of skin or vascular compromise
- ☐Good knee and hip muscle control
Note for the physiotherapist
The goal of this phase is to reach cast removal without proximal deficits: ankle recovery will then be much faster.
Phase 3 — After cast removal: gradual mobility recovery
Indicative timing: From day 30 for 2-3 weeks
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Recover the ankle range lost during immobilisation
- •Resume walking without crutches
- •Reactivate calf and tibialis posterior
What to do
- •Active ankle mobility within the permitted range, without resistance. Use short sessions at the prescribed frequency; do not force full hindfoot movement.
- •Assisted mobilisation and stretching only after specific clearance: respect healing of the operated tissues and the hand placement, range and dose demonstrated by the physiotherapist. Cast removal alone does not authorise belt traction.
- •Reduce crutches according to authorised weight bearing and gait quality, without a mandatory deadline after cast removal.
- •Toe grip exercises (towel, marbles) as daily play
- •Cycling and swimming once the wound has healed
- •After Achilles lengthening: stretch only within the authorised limits for tendon healing; use any night splint according to the individual prescription.
Restrictions and precautions
- •No painful or forced manoeuvres
- •Still no running or jumping
- •No resisted work in this phase; wait for phase 4 criteria and specific clearance.
Exercises for this phase
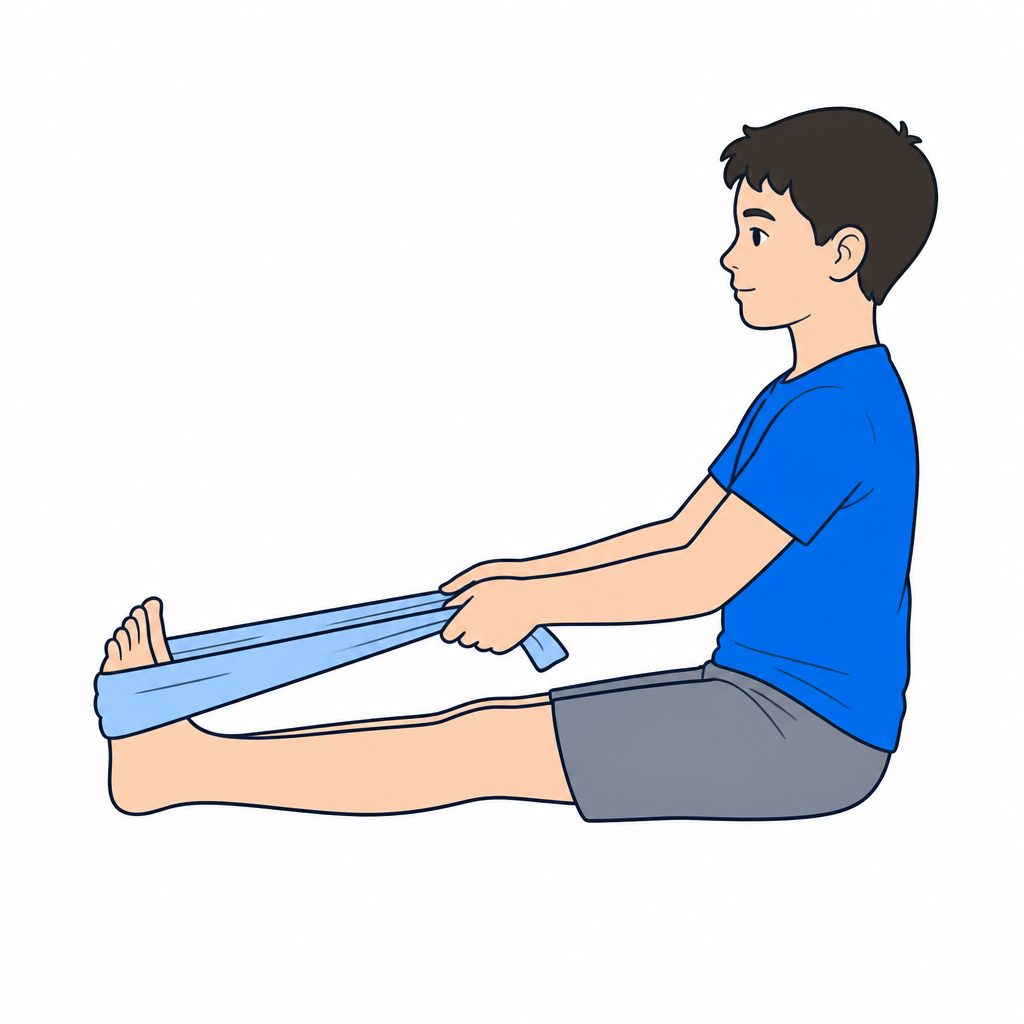
2. Static belt stretch (passive mobilisation)After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sit on the floor with a straight back and knees fully extended.
- •Loop a bathrobe belt around the base of the toes of the affected foot.
- •Pull gently towards you until you feel tension in the Achilles tendon, never pain.
- •Keep the knee in the position demonstrated for this variant. Do not force it: bending changes the tension on the calf muscles but does not automatically eliminate the stretch of the calf–Achilles complex.
Dosage: Hold 30 seconds, 10 repetitions every day
3. Active ankle mobilisationAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sitting or lying, move the ankle (not just the toes) pulling the foot up and then pointing it down.
- •Then draw wide circles with the foot, first clockwise then anticlockwise.
- •The movement must be gentle, wide and complete, up to the pain-free limit.
Dosage: 20 seconds of continuous motion, 10 times a day
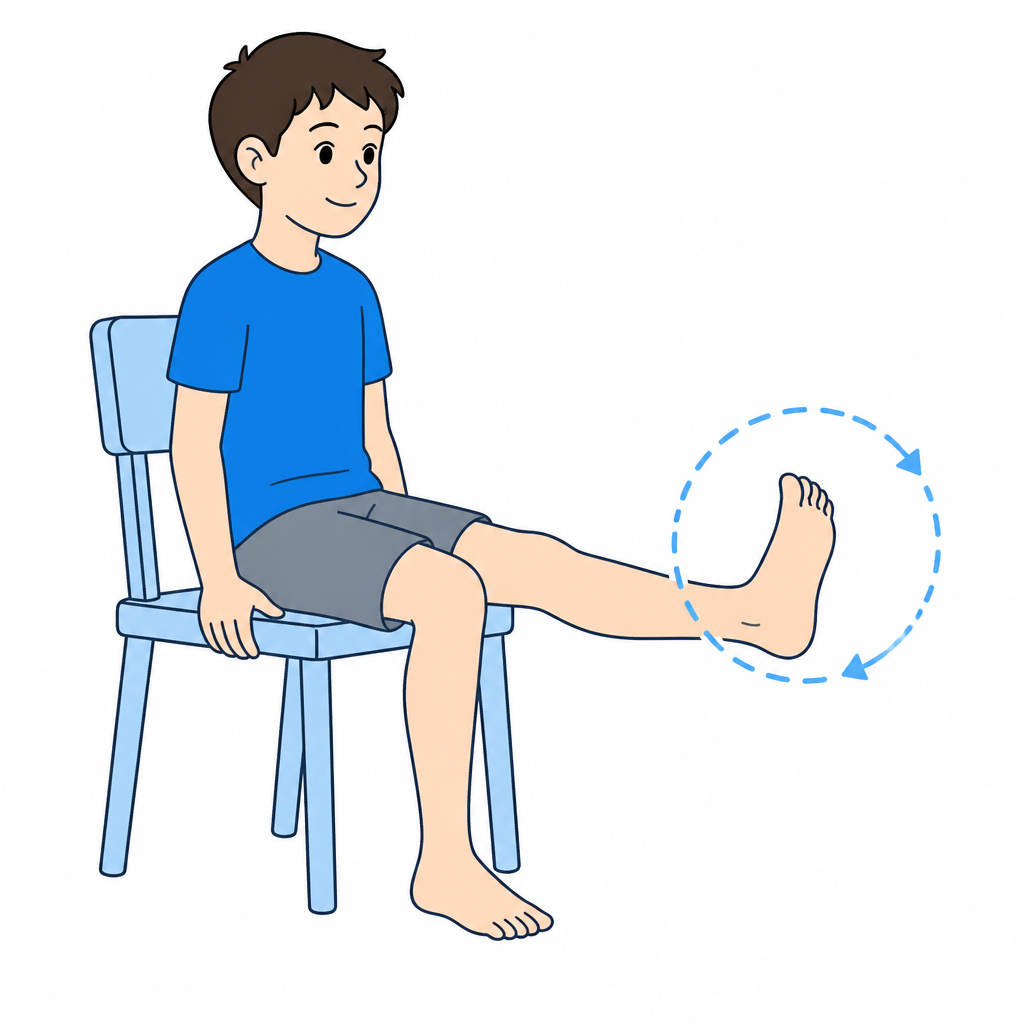
4. Foot alphabetAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •With the leg supported and the foot free in the air, “write” the alphabet letters with the big toe.
- •Move only the ankle, keeping the knee still.
- •Make big letters: they are meant to explore the whole range of motion.
Dosage: 1-2 alphabets, 2-3 times a day
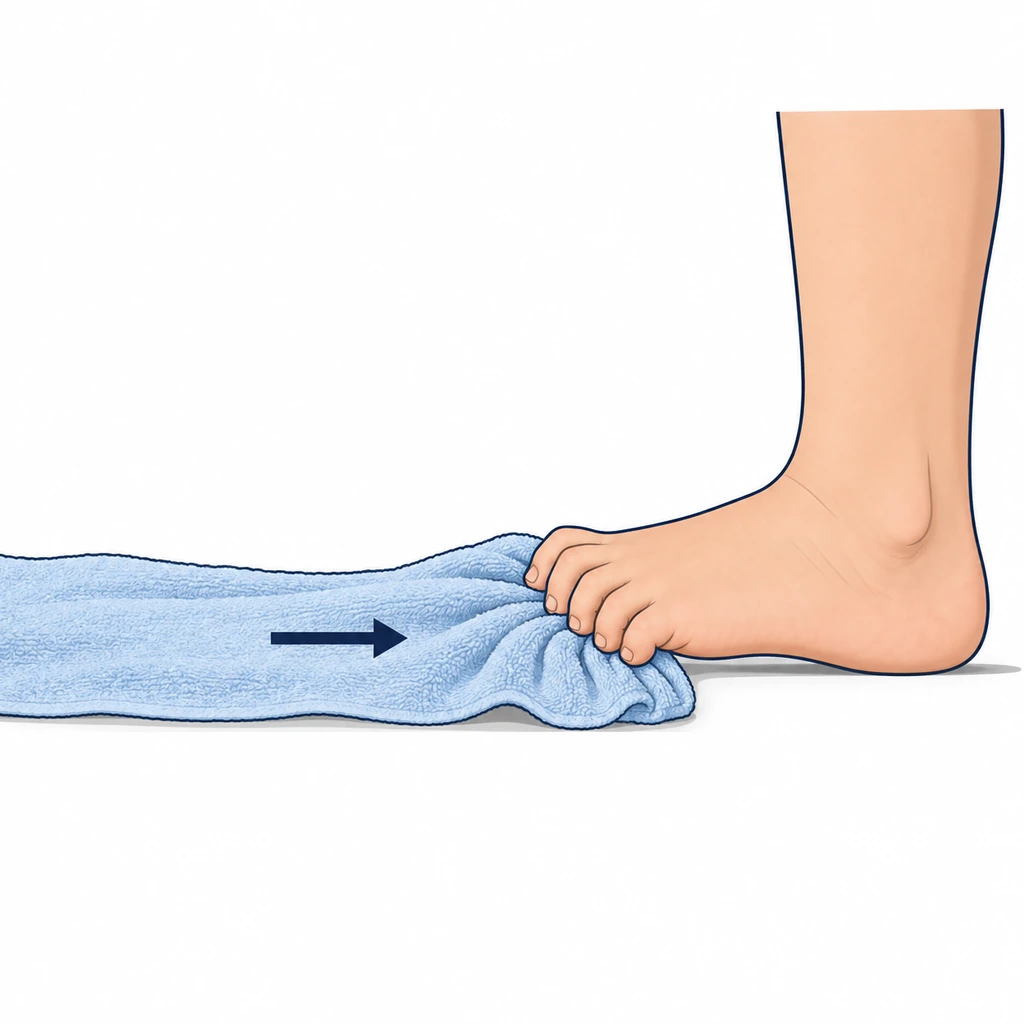
5. Towel curlsAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sitting, place the foot on a towel spread on the floor.
- •Scrunch the towel towards you using only the toes, without lifting the heel.
- •Then try to grasp it and move it sideways.
Dosage: 5 minutes a day

6. Picking up small objectsAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Scatter marbles, bottle caps or small bricks on the floor.
- •Grasp each object with the toes and drop it into a container.
- •It works best as a timed game: how many objects in 2 minutes?
Dosage: 5 minutes a day
Ready for the next phase when
- ☐Independent walking without crutches
- ☐Dorsiflexion progressively approaching the healthy side
- ☐No significant end-of-day swelling
Note for the physiotherapist
Stiffness after the cast is expected: it resolves with short, very frequent sessions, never with forced single-session manoeuvres.
Phase 4 — Strengthening, proprioception and gait retraining
Indicative timing: After phase 3: recovered mobility and gait, resistance authorised
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Strengthen tibialis posterior, peroneals and intrinsic foot muscles
- •Restore single-leg balance
- •Normalise foot contact, reducing walking on the outer border
What to do
- •Short foot exercise: shorten the foot by drawing the forefoot towards the heel without curling the toes, 10 reps of 5 seconds, 3 times a day
- •Toe yoga: lift the big toe keeping the others down and vice versa, 10 reps each way
- •Tibialis posterior strengthening with a band in resisted inversion (first introduction of resistance), 3 sets of 15
- •Calf raises, double-leg then progressively single-leg, 3 sets of 10-15
- •Single-leg balance on firm ground with eyes open, next to a stable support; unstable surfaces only under direct professional supervision.
- •Heel walking and toe walking alternated for 10-15 metres, as daily play
Restrictions and precautions
- •No running, jumping or team sport before the times given in phase 5
Exercises for this phase
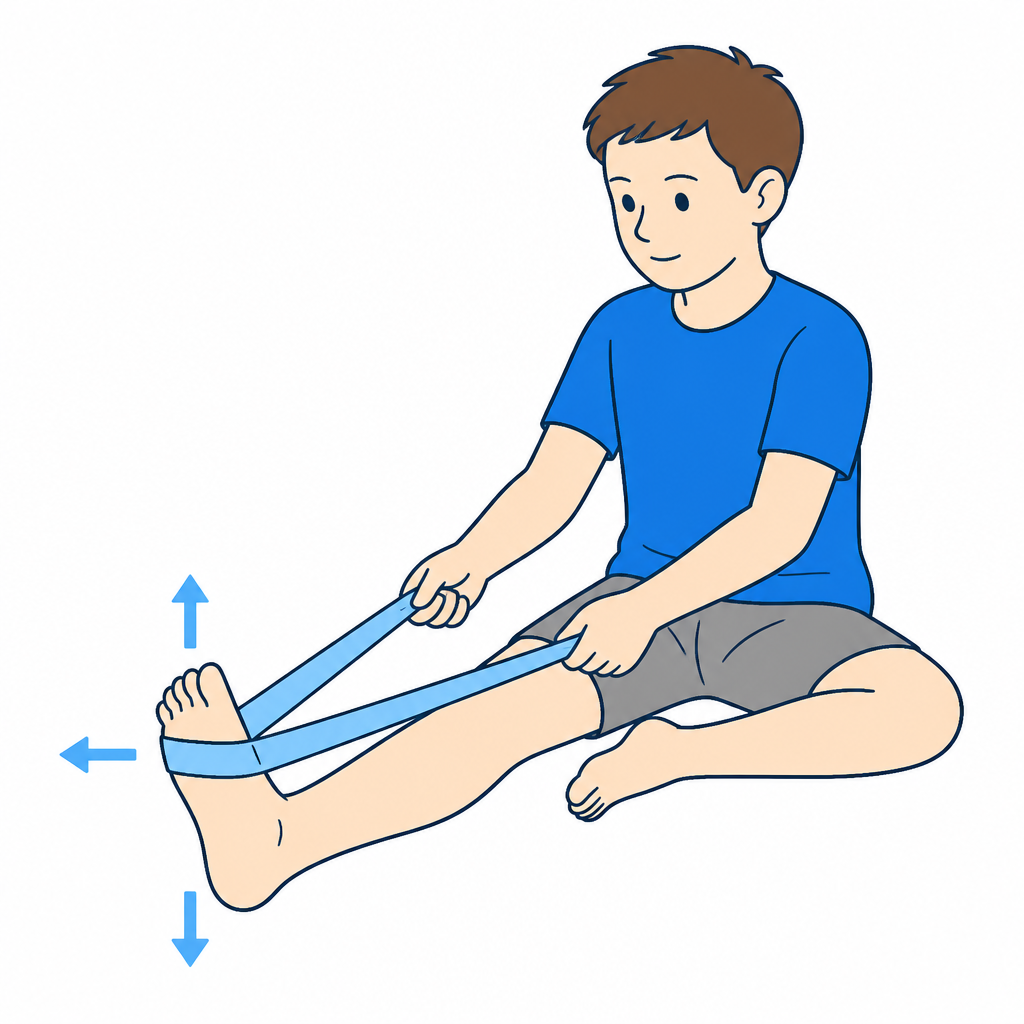
7. Dynamic band stretching (4 directions)After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Anchor an elastic band (TheraBand type) to a fixed support such as a table leg.
- •Move against the band’s pull: foot up, foot down, inwards, outwards.
- •Control the return: the slow part of the movement is what strengthens most.
- •Increase resistance (a stiffer band) once the exercise feels easy.
Dosage: 15 movements per direction, every day
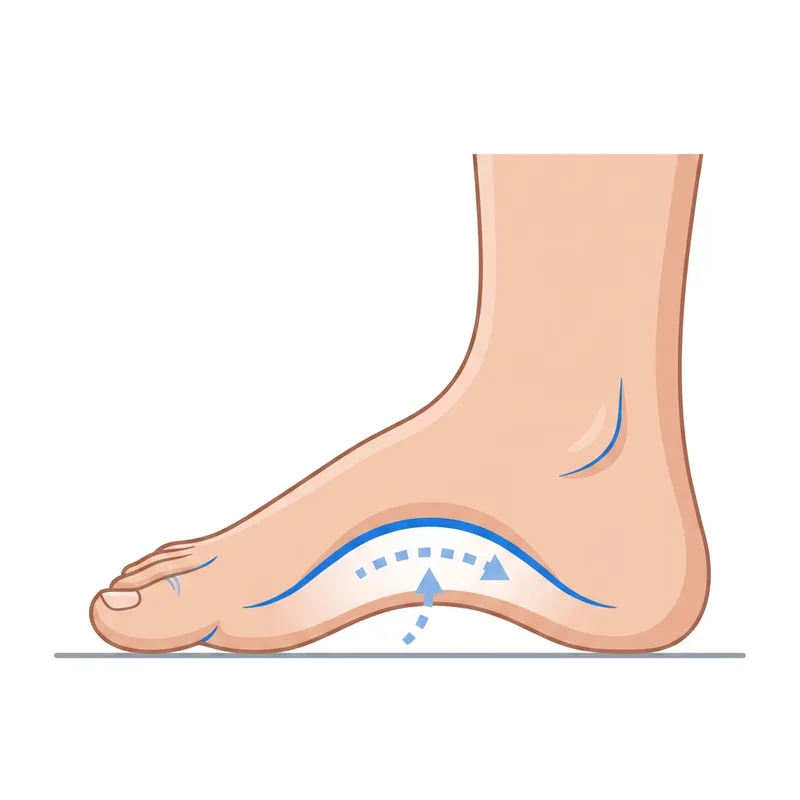
8. Short foot exerciseAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sitting with the foot flat on the floor, heel and toes in contact.
- •Draw the forefoot towards the heel, “shortening” the foot and lifting the arch, without curling the toes.
- •Aim to keep the toes long and relaxed. If they curl, reduce the effort and ask for help finding the movement; this is not a test of an individual muscle.
Dosage: 10 repetitions of 5 seconds, 3 times a day
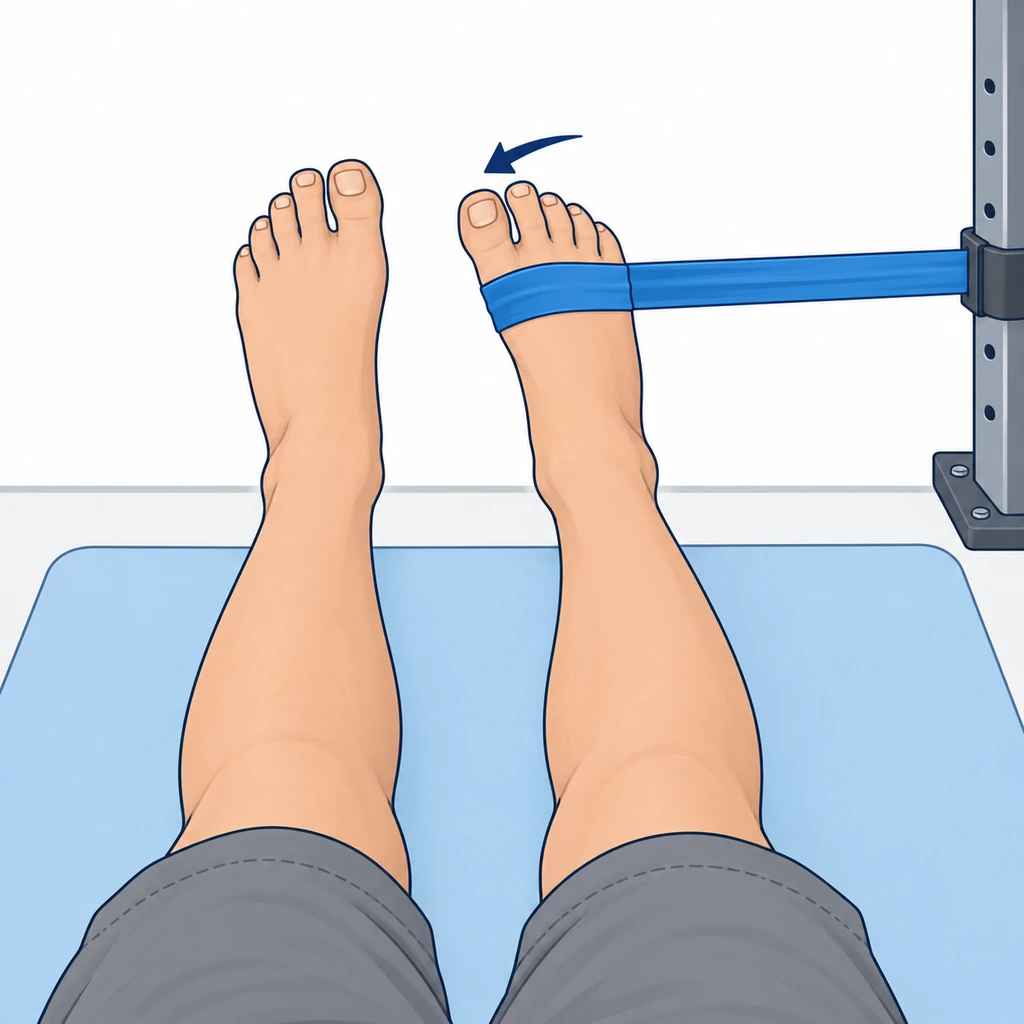
9. Tibialis posterior strengthening with a bandAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Band anchored to the side, looped around the forefoot.
- •Move the foot inwards and downwards against the resistance, keeping the knee still.
- •Return to the start position slowly, over 3 seconds.
Dosage: 3 sets of 15, daily
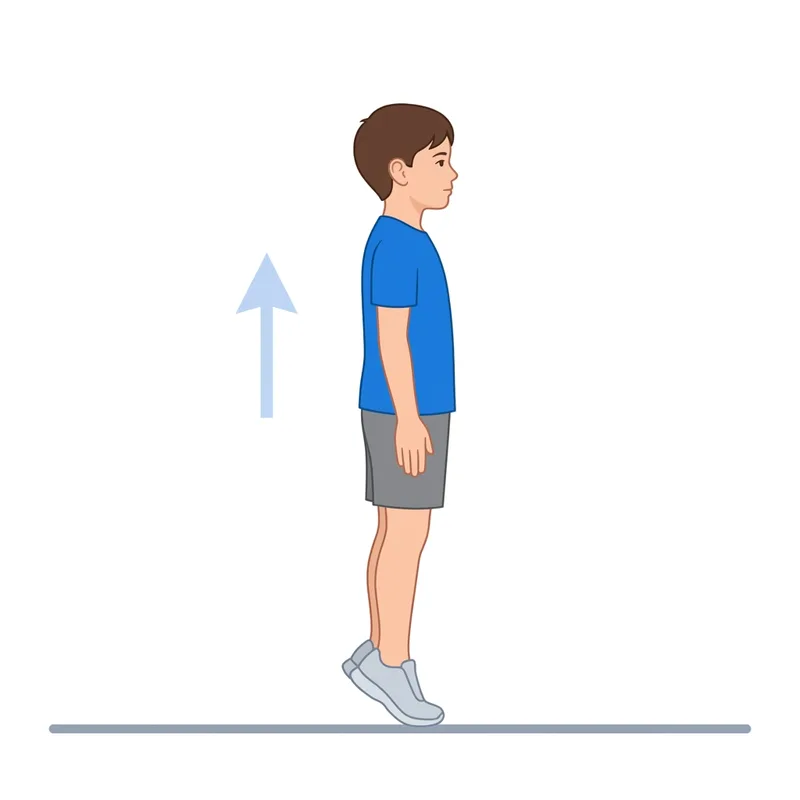
10. Calf raisesAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Standing, hands on a wall for balance.
- •Rise onto the toes keeping the heels aligned, then lower slowly over 3 seconds.
- •Agree progression to single-leg work or greater resistance with the physiotherapist, taking the procedure, control and load response into account.
Dosage: 3 sets of 10-15, daily
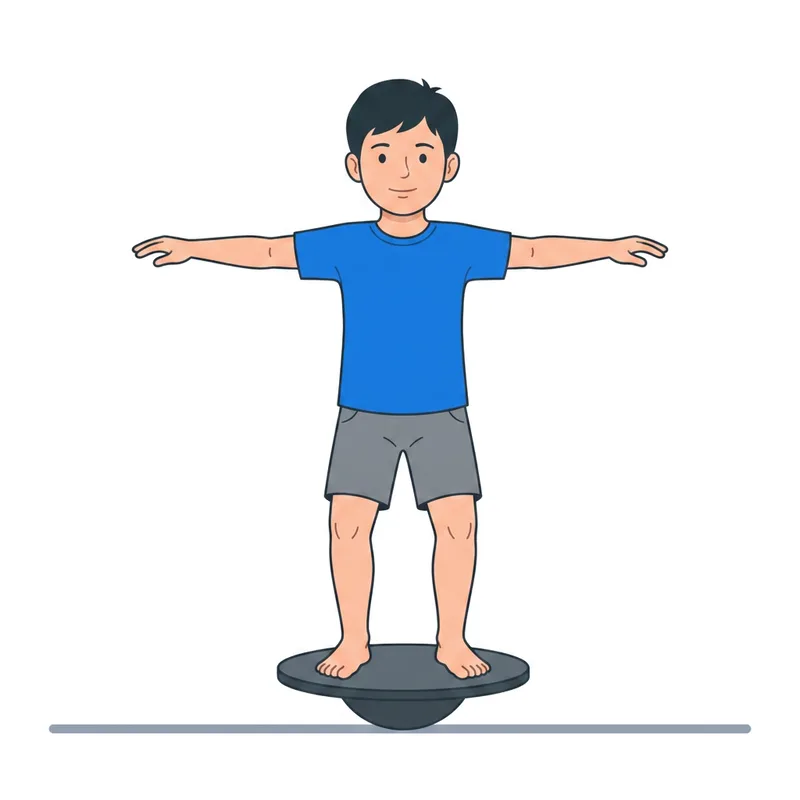
11. Balance on an unstable surfaceAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Only under direct physiotherapy supervision, in the authorised phase and after recovering balance on firm ground.
- •On the selected cushion or board keep your eyes open, the knee slightly bent and a stable support within reach.
- •Put the other foot down if you lose control. At home use the demonstrated firm-ground variant; do not add closed eyes or perturbations independently.
Dosage: 3 x 30 seconds per side, daily
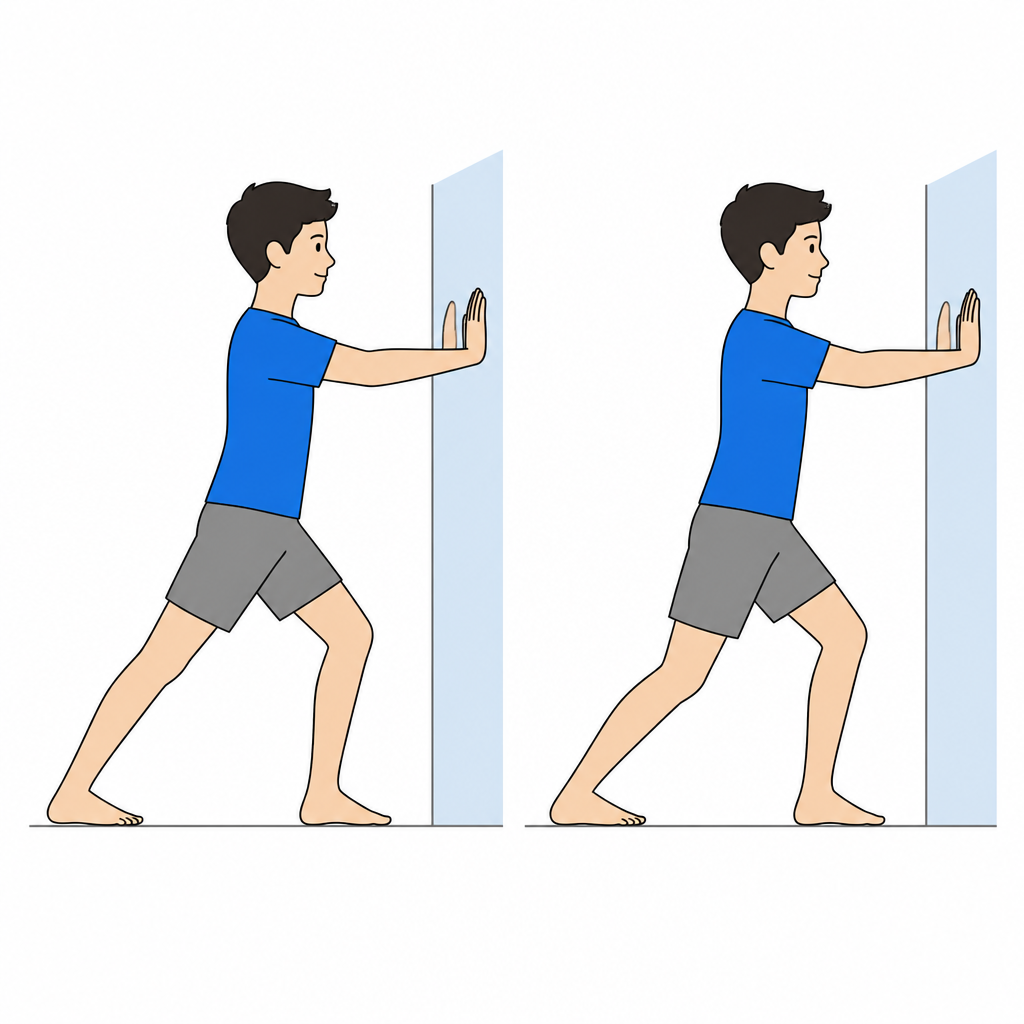
12. Wall calf stretch (two positions)After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Hands on the wall, operated leg behind, heel firmly on the floor.
- •First position: back knee straight (stretches gastrocnemius).
- •Second position: back knee slightly bent (stretches soleus).
- •The heel must never lift off the floor.
Dosage: 3 x 30 seconds per position, daily
Ready for the next phase when
- ☐Single-leg heel raise performed with the heel inverting
- ☐Single-leg balance ≥30 seconds
- ☐More symmetrical foot contact with less outer-border walking
Note for the physiotherapist
If outer-border loading persists, reassess pain, mobility and implant tolerance before progressing. Do not correct it with forced passive movement.
Phase 5 — Return to running, jumping and sport
Indicative timing: Running and jumping from month 2, only with restored dorsiflexion and a possible heel raise.
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Progressively resume running and jumping
- •Return to the chosen sport without pain or reactive swelling
What to do
- •Running progression: brisk walking, then walk/jog alternation, then continuous running on even ground
- •Introduction of jumping: double-leg hops, then single-leg, then jumps with direction changes
- •Return to team training before matches/competition
- •Daily maintenance of calf stretching and intrinsic foot exercises
Restrictions and precautions
- •Stop the progression if sinus tarsi pain or swelling persisting the next day appears
No additional exercise cards are assigned here. Follow this phase’s indications and the programme selected by your physiotherapist; do not automatically continue or progress every previous exercise.
Ready for the next phase when
- ☐Continuous running for 10-15 minutes without pain
- ☐Symmetrical single-leg hop compared with the healthy side
- ☐No swelling the morning after activity
Note for the physiotherapist
In children progression often happens spontaneously during play: the physiotherapist’s role is more to contain than to push.
Phase 6 — Follow-up and implant management
Indicative timing: From month 3 until screw removal
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Maintain the correction obtained and a mobile foot
- •Monitor implant tolerance
- •Plan screw removal when indicated
What to do
- •Scheduled clinical review assessing foot contact, dorsiflexion and sinus tarsi pain
- •Long-term maintenance of calf stretching and short-foot exercises, especially in high-impact sports
- •Comfortable shoes with a supportive heel counter; insoles only if specifically prescribed
- •Implant removal is not automatic: the indication and timing depend on implant type, growth, symptoms and follow-up findings.
No additional exercise cards are assigned here. Follow this phase’s indications and the programme selected by your physiotherapist; do not automatically continue or progress every previous exercise.
Ready for the next phase when
- ☐Pain-free foot with a maintained arch on weight bearing
- ☐Full and symmetrical ankle range of motion
- ☐Sport performed without limitations
If symptoms appear after a progression
If persistent pain, effusion or swelling, or loss of movement appears after moving to a new phase or increasing load, stop progression and contact the treating clinician or physiotherapist to review the programme. Seek prompt assessment for the red flags below. This document does not replace individual clinical assessment.
Return to sport / full activity
Sport at 2-3 months, conditional on triceps surae strength recovery (single-leg heel raise).
- ☐Normal gait, without limp and without predominant outer-border loading
- ☐Ankle dorsiflexion symmetrical to the other side (knee-to-wall test)
- ☐Single-leg heel raise x 10 repetitions without pain
- ☐Single-leg balance ≥30 seconds, including on an unstable surface
- ☐Continuous running for 10-15 minutes and symmetrical single-leg hop, without sinus tarsi pain
- ☐No swelling the day after sport-level loading
After a period of casting the limiting factor is triceps surae strength: resuming jumping requires recovery of the single-leg heel raise, which comes later than range of motion.
Red flags: stop and contact us
- •Fever, spreading redness, discharge or bad smell from the wound (suspected infection)
- •Pain that increases instead of decreasing after the first days, or is not controlled by prescribed analgesics
- •Marked swelling not settling with elevation and ice, or a hard, painful calf
- •Persistent pins and needles, numbness, or cold, pale or bluish toes (dressing or cast too tight: seek advice immediately)
- •Progressive inability to move the ankle, or stiffness worsening despite exercises
- •Persistent focal pain in the sinus tarsi (in front of and below the lateral malleolus) not improving after month 2: possible implant intolerance
- •Cast broken, wet or rotating on the limb
- •Sudden loss of push-off strength or inability to rise on tiptoe after cast removal (suspected failure of the lengthening)
Author: Dott. Daniele Priano, Paediatric Orthopaedics. Content version: 9 September 2026.
Timings are indicative: progression depends on clinical and functional criteria and on the treating clinician’s instructions.
Full introduction and references at ortopediaevolutiva.com/en/rehabilitation/flatfoot-surgery-arthroereisis-achilles-lengthening
Flatfoot: post-operative pathway after arthroereisis with Achilles lengthening — Dott. Daniele Priano, Pediatric Orthopaedics · Information document: it does not replace an in-person assessment.
 Latest online version
This protocol may be used and shared for clinical and informational purposes provided that attribution to the author and to the original source is kept intact. Republishing or distributing it as one’s own work is not allowed.
Other protocols

Any questions?
For information or questions, email me or view the locations and contact details.
Email: daniele.priano@ortopediaevolutiva.com