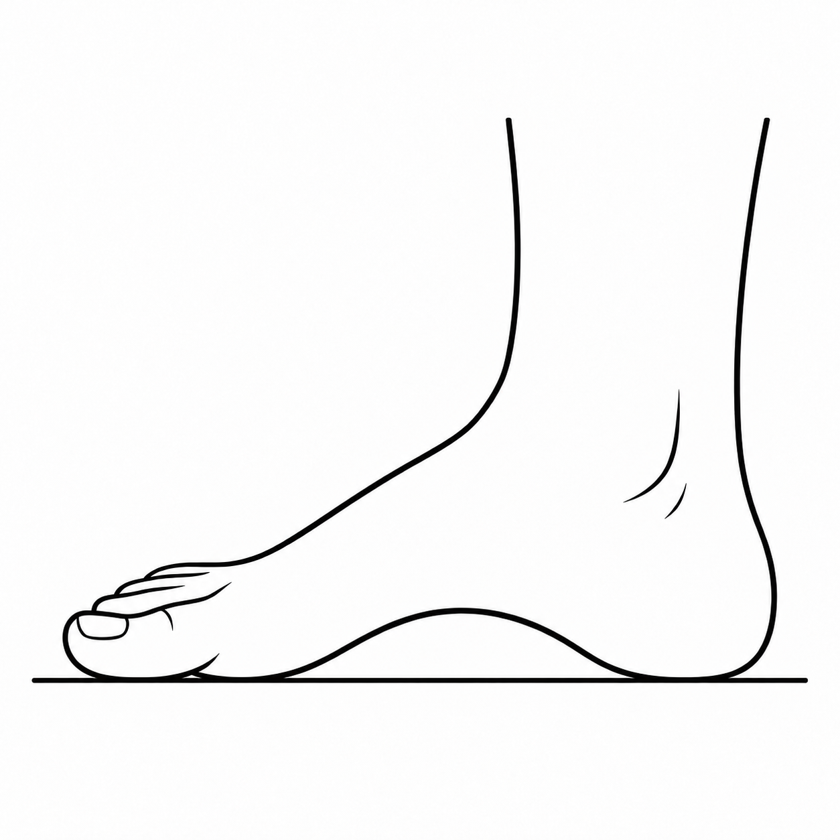
Flatfoot: post-operative pathway after exosinotarsal arthroereisis
Recovery after isolated arthroereisis: walking and motion within discharge instructions, followed by strength and sport.
Personal practice: no running or jumping for 45 days; sport around 2 months only if ready.
For physiotherapists: adapt exercises, dosage and progression to the injury or procedure, protection, permitted loading and movement; check clinical criteria, not elapsed time alone.
Scope and before starting
For isolated arthroereisis in flexible flatfoot. Associated tendon or bone procedures require their specific pathway.
Before starting
Confirm technique, side, associated procedures and prescribed loading. Dates describe Dr Priano’s personal pathway, not a standard for every surgeon.
Motion
Gentle ankle motion if cleared. The implant limits hindfoot motion: do not force eversion or aim to restore pre-correction mobility.
Practical rule
Increase work if gait, pain and swelling remain stable after the session too. The checks below are a practical checklist adapted from the sources, not a return-to-sport test validated for all children.
The picture shows the movement; use the range and dose selected for you. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Do not force the foot to loosen it: use only permitted movements, without pushing against pain or resistance.
Return to sport when ready and cleared, not just because a date has arrived.
Treatment phases and illustrated exercises
Exercises are shown in their assigned starting phase, with their instructions and precautions. The physiotherapist selects them for the individual plan; the complete protocol is not a prescription to perform them all.
Respect the minimum times and protection required for the procedure. Time alone does not authorise progression: the treating team checks the clinical criteria.
Preparation for surgery
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
Goals
Understand the planned post-operative weight bearing and be able to use crutches.
Organise home and school for the first weeks.
Check baseline foot and ankle mobility and strength, where useful.
Know when motion starts and its limits for the specific procedure: with a cast, no ankle mobility until removal and movement clearance.
Preparation plan
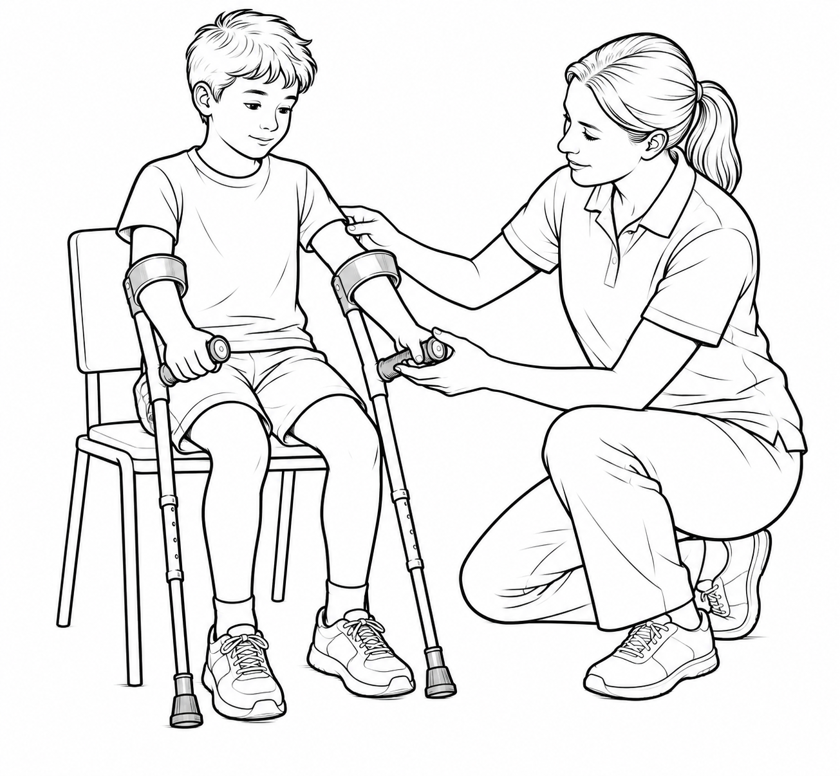
Practical crutch training before surgery, on level ground and stairs.
Home and school organisation: pathways, bathroom, transport, accessible desk, temporary PE exemption.
Where useful, simple ankle and foot mobility exercises, without turning preparation into a mandatory programme.
Precautions
Preparation is not a prerequisite: elective surgery should not be postponed to complete preoperative exercises.
Criteria checked by the treating team
Safe crutch use with the planned weight bearing.
Family informed about weight bearing, crutch use and return to school.
Home and school organised for the return after surgery.
When preparation is useful
Before elective arthroereisis (with or without associated procedures).
A standard course of preoperative physiotherapy has not been shown to improve the outcome of arthroereisis: preparation is mainly educational and organisational.
Home and school preparation
Prepare clear pathways, a place to keep the foot elevated and comfortable wide shoes for the return home.
Check stairs, bathroom and school transport with crutches.
Inform the school: expected absence, accessible desk, temporary PE exemption.
Crutch and weight-bearing training
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
Try the crutches before surgery, with correct height and the weight-bearing status set by the surgeon.
Practise on level ground, stairs and the entrance to your home, with someone assisting.
Also practise sitting, standing and moving in the bathroom while respecting the planned loading restrictions.
Dose and progression: At least one training session before admission; repeat until the technique is safe.
Active ankle mobility
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
Seated or lying, move the ankle into flexion, extension and slow circles, within the pain-free range.
Keep the movement smooth, without forcing the painful end range.
Dose and progression: Indicative: 10-15 movements per direction, 2-3 times a day.
1. Initial protection
First days
Goals
Control swelling and make transfers safe.
Physiotherapy plan
Move toes and the ankle up/down only within the authorised range.
Use crutches and weight bearing as instructed at discharge; elevate at rest if helpful.
Precautions
No forced hindfoot movement, large circles or belt stretching.
Criteria the treating team checks before progression
Pain controlled and dressing/cast without problems.
Safe transfers within prescribed loading.
Illustrated exercise options
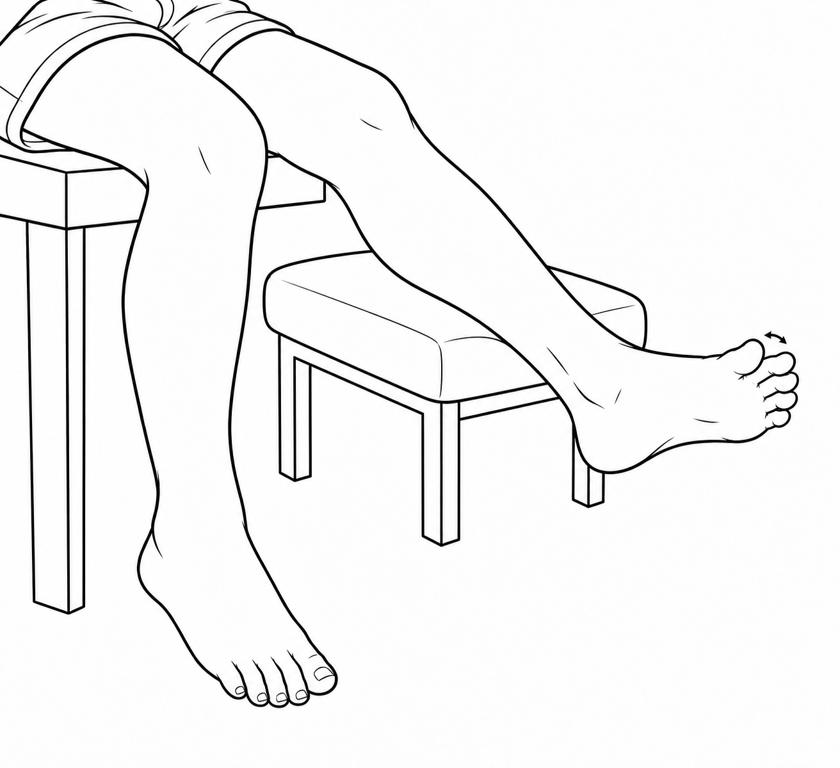
Toe mobility
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
With the leg supported, gently move the free toes without pulling them by hand.
If wearing a cast, do not move the ankle inside it or remove it to follow the picture.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
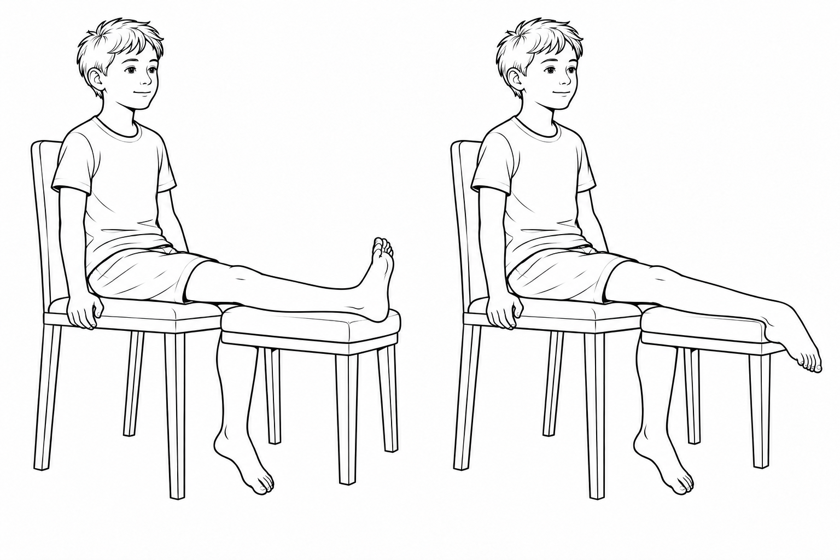
Unloaded ankle motion
Up/down motion only if cleared and out of the cast. Do not force eversion or rotations against the implant.
With the leg supported and foot free, slowly move the foot towards and away from you within the permitted range.
The figure shows the two directions, not the range to achieve. Do not use bands or manual pressure.
Stop for deep pain; do not add rotations unless authorised.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
2. Independence during protection
Until wound review
Goals
Manage school and travel without overload.
Physiotherapy plan
Short walks within permitted loading and already-cleared gentle motion.
Monitor comfort, pain and swelling; adjust walking distances.
Precautions
No running, jumping or games with a fall risk.
Criteria the treating team checks before progression
Favourable wound review.
Clearance to continue recovery.
3. Motion and gait
After initial review
Goals
Restore regular gait and comfortable motion.
Physiotherapy plan
Active up/down motion, gait retraining and gentle static foot-muscle activation only if cleared.
Gradually reduce crutches when permitted loading and control allow walking without a limp.
Precautions
Do not force eversion or rotations against the implant limit.
Criteria the treating team checks before progression
Gait improving without persistent pain increase.
Strengthening cleared and wound healed.
4. Strength and balance
After strengthening clearance
Goals
Restore push-off and foot control.
Physiotherapy plan
After strengthening clearance, progress from static activation to supported bilateral calf raises and intrinsic-foot work; advance according to strength and symptoms.
Supported firm-ground balance, then single-leg balance if controlled; resistance selected for identified deficits.
Precautions
No exercise should force the hindfoot against the implant.
Criteria the treating team checks before progression
Limp-free walking; record quality and number of bilateral calf raises and single-leg balance, if cleared, comparing them across reviews without later pain or swelling.
Impact clearance with the specified minimum protection period also respected.
Illustrated exercise options
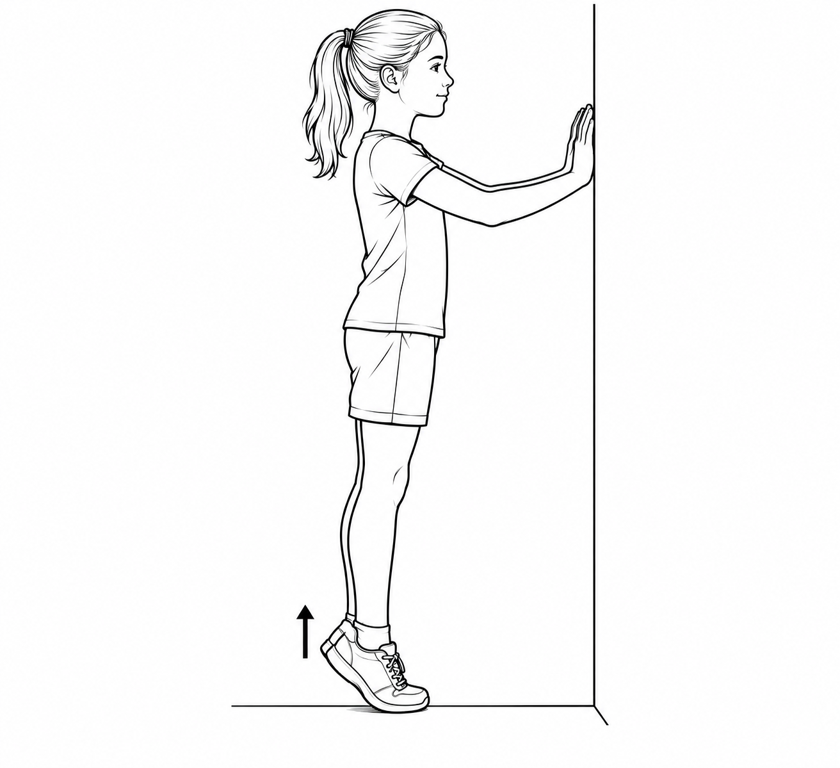
Supported double-leg calf raises
Only after clearance for full weight bearing and calf strengthening.
On a level floor, place your hands on a stable support as illustrated.
With both feet, slowly raise the heels and lower them with control.
Do not independently progress to one leg or a step edge. Stop for joint pain and monitor the subsequent response.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
Short foot exercise
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Sitting with the foot flat on the floor, heel and toes in contact.
Draw the forefoot towards the heel, “shortening” the foot and lifting the arch, without curling the toes.
Aim to keep the toes long and relaxed. If they curl, reduce the effort and ask for help finding the movement; this is not a test of an individual muscle.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
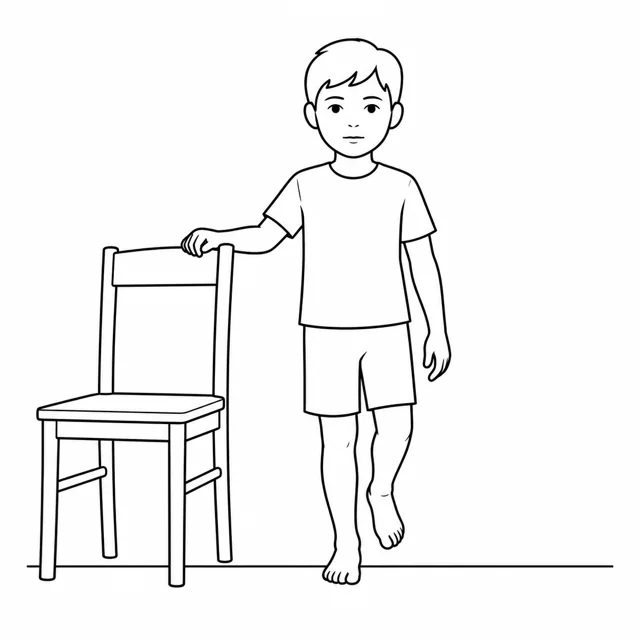
Firm-ground balance
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
On firm ground with eyes open, slightly lift the other foot while keeping the pelvis level.
Keep one hand on a stable support as illustrated; an adult must be able to assist the child.
Put the free foot down before losing control. Do not add cushions, closed eyes or perturbations.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
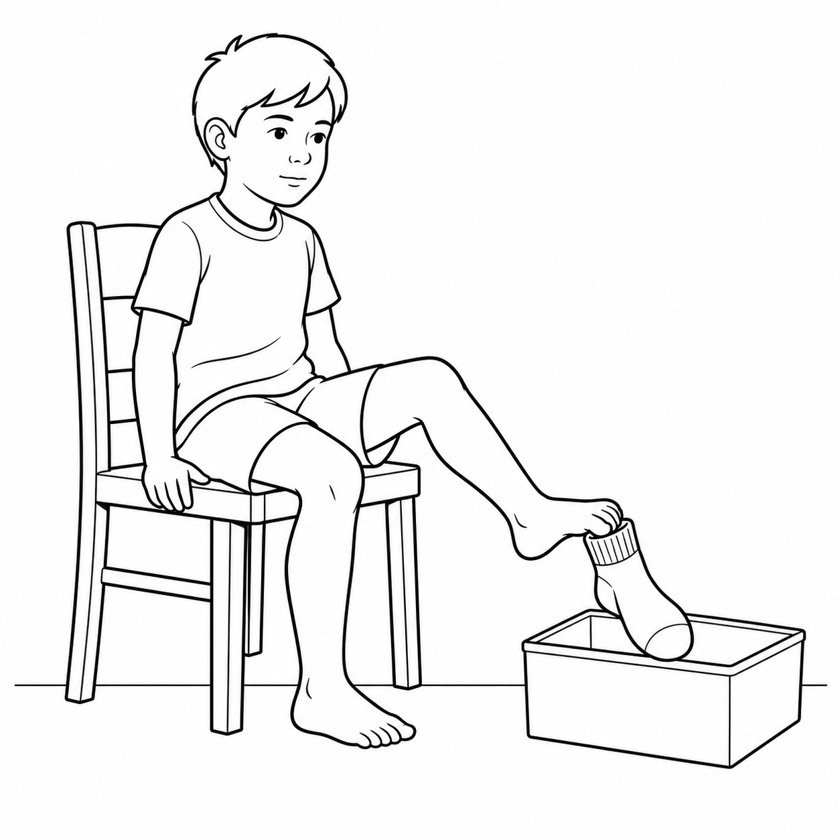
Towel curl
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Sit with the foot on a large towel laid on the floor.
Gently curl the toes to draw the fabric closer, keeping the heel down. Release without forcing.
Adult supervision is required; do not use marbles, buttons or other small objects that can be swallowed.
Dose and progression: Brief supervised play, only if selected; stop before discomfort.
5. Resume impact
Not before day 45 in the personal pathway, if ready
Goals
Restore controlled running and landing.
Physiotherapy plan
After impact clearance, with limp-free gait and controlled calf raises and balance, alternate walking and short straight-line running intervals on an even surface.
Only after running is well tolerated, introduce small hops with controlled landings alongside the physiotherapist; check subsequent pain and swelling.
Precautions
Do not progress with limping, focal pain or persistent swelling.
Criteria the treating team checks before progression
Progressive tasks tolerated after the session too.
Adequate control for sport training.
Illustrated exercise options
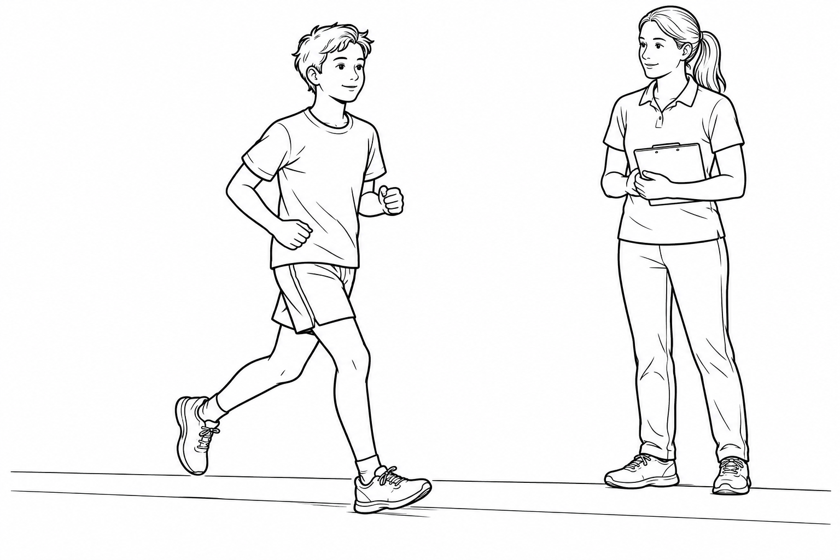
Straight-line walk–run progression
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
On level, even ground, alternate walking with short bouts of easy straight-line jogging according to the physiotherapist’s programme.
Keep an even gait without limping. Begin without sprinting, hills, jumping or direction changes.
Increase one demand at a time. If joint pain, limping or swelling occurs during the work or the next day, stop the progression and report it to the physiotherapist.
Dose and progression: Run/walk intervals, duration and recovery set by the physiotherapist for the procedure, age and response to loading; the phase does not provide an automatic dose.
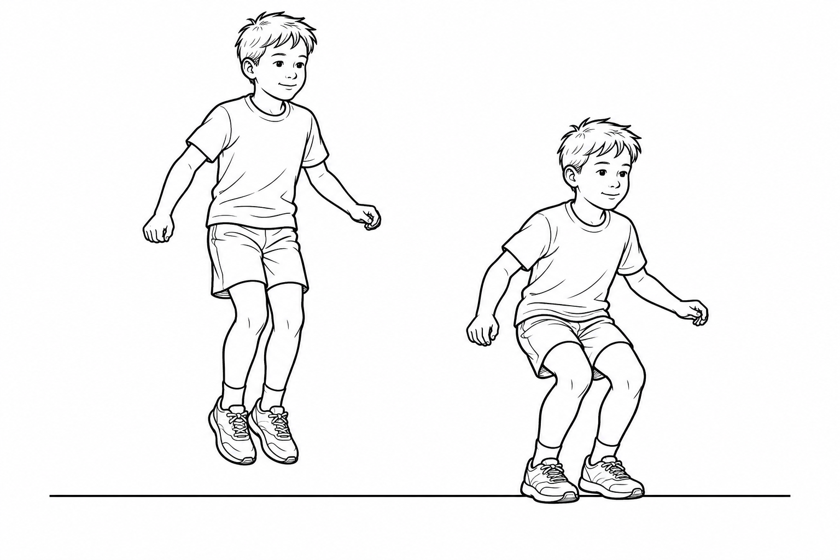
Small two-foot forward hops
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
With the physiotherapist, make one small two-foot forward hop on a firm, even surface, as illustrated.
Land on both feet with control and pause before repeating. The physiotherapist selects distance and number of hops; no sideways or single-leg hops without further instruction.
Stop for pain or loss of control and report pain or swelling afterwards.
Dose and progression: Initial attempts and dose selected by the physiotherapist; increase only after checking the subsequent response.
6. Sport
Approximately 2 months in the personal pathway
Goals
Gradually return to the usual level.
Physiotherapy plan
After controlled landings, introduce deceleration and direction changes; partial then full training before competition.
Maintain strength and control work useful for the sport.
Precautions
The date does not replace recovery assessment.
Criteria the treating team checks at the end of the pathway
Full training tolerated without pain or swelling.
Return agreed at review.
Illustrated exercise options
Planned braking and direction changes
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
With the physiotherapist, begin with controlled slowing and wide turns at low speed in agreed directions.
Control the trunk, knee and foot. Increase speed and turning angle separately; sharp, reactive or contact movements require further assessment.
Stop for pain, giving way or limping; also report swelling or pain after the session and the next day.
Dose and progression: Intervals, rests and recovery days selected for age, sport and previous level. No independent maximal tests; tolerate full training before competition.
Return to sport / full activity
Personal practice: no running or jumping for 45 days; sport around 2 months only if ready.
Limp-free gait; reassess calf-raise and single-leg balance quality across reviews, without universal cutoffs.
Running, small hops and full training without subsequent focal pain or swelling.
Favourable clinical review and all associated-procedure restrictions respected.
Do not force the hindfoot to match its pre-correction movement; symmetry alone is insufficient in bilateral cases.
Warning signs: stop and contact the treating team
Fever, increasing wound redness or warmth, or drainage: contact the surgical team the same day, even without fever.
Increasing focal pain, worsening limp or sudden difficulty pushing off: stop progression and arrange review.
A cold, pale or numb foot, or severe pain under the cast: go to emergency care immediately. A wet or broken cast: contact the team to have it checked.
Guidelines and literature
Sources inform the pathway; they do not validate every dose for an individual child.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
Select the exact phase assigned by the treating team, then choose each prescribed activity. No exercise is selected automatically. The team sets loading, movement, aids, dose and frequency; missing instructions must be completed before use, including by hand.
Browse illustrated exercise options
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
Short phase in the weeks before elective surgery: it does not require a structured course of physiotherapy.
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Up/down motion only if cleared and out of the cast. Do not force eversion or rotations against the implant.
Only after clearance for full weight bearing and calf strengthening.
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
Choose the current phase to prepare a printable sheet.
Phase safety summary ·
COMPLETE BEFORE EXERCISING — The treating team must complete the blank instructions, including handwritten entries, before this sheet is used.
Follow the assigned phase and instructions confirmed by the treating team; filling in fields does not authorise exercise.
No exercises assigned. This is a safety summary, not a complete exercise prescription.
Individual instructions for this phase
Loading (how much weight on the leg): ________________________________
Brace and crutches: ________________________________
Procedure and starting conditions
Before starting: Confirm technique, side, associated procedures and prescribed loading. Dates describe Dr Priano’s personal pathway, not a standard for every surgeon.
Motion: Gentle ankle motion if cleared. The implant limits hindfoot motion: do not force eversion or aim to restore pre-correction mobility.
Practical rule: Increase work if gait, pain and swelling remain stable after the session too. The checks below are a practical checklist adapted from the sources, not a return-to-sport test validated for all children.
Advice before starting
The picture shows the movement; use the range and dose selected for you. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Do not force the foot to loosen it: use only permitted movements, without pushing against pain or resistance.
Return to sport when ready and cleared, not just because a date has arrived.
Warning signs: stop and contact the treating team
Fever, increasing wound redness or warmth, or drainage: contact the surgical team the same day, even without fever.
Increasing focal pain, worsening limp or sudden difficulty pushing off: stop progression and arrange review.
A cold, pale or numb foot, or severe pain under the cast: go to emergency care immediately. A wet or broken cast: contact the team to have it checked.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.