Paediatric Orthopaedic Specialist
Out-toeing (walking with feet turned out)
Home Exercise Program
Not every exercise listed here is suitable for every child: the selection is individual and is defined during the consultation.
For whom: Activities for coordination and function after assessment. Do not force foot rotation to correct bony torsion. Limp or hip pain require review.
Dose and frequency: Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Equipment and supervision: A stable, clear surface, comfortable clothing and a secure support. Check resistance-band anchors. Adult supervision; avoid marbles and small objects if the child may put them in their mouth, using a towel instead.
Avoid: Forcing a painful or unauthorised movement; Increasing load, resistance or frequency without the agreed rest periods; Doing balance exercises without stable support or supervision.
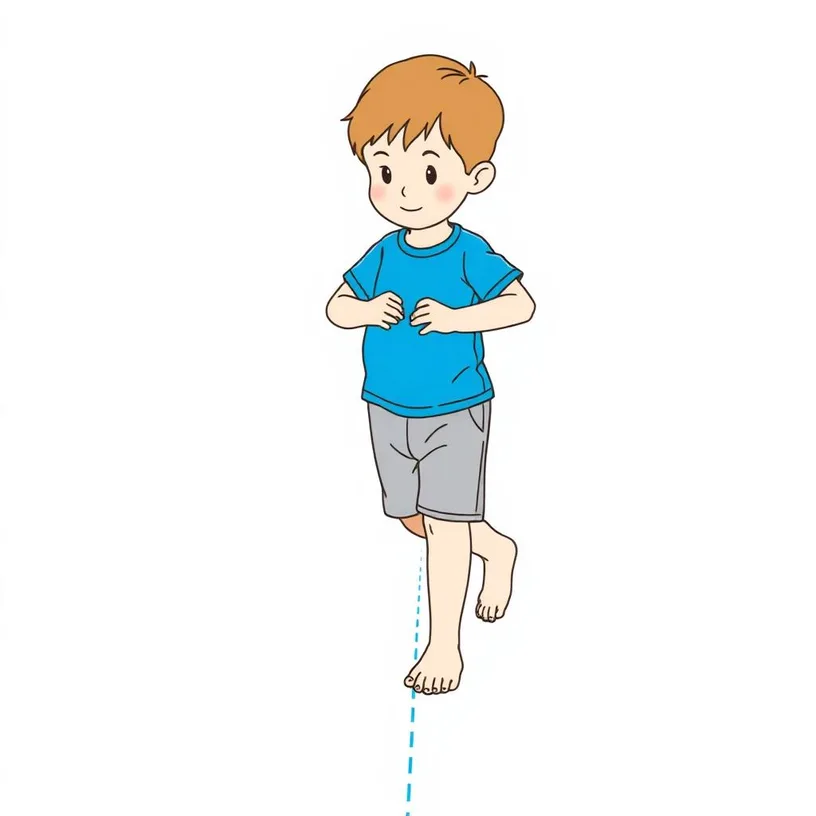
1.Natural walking and coordination
Movement play does not change bone torsion.
Walk along a clear path or broad line as a coordination game, allowing the feet their comfortable direction. Do not force straight or outward-pointing toes or correct every step. Pain, limping or worsening requires assessment.
Play according to interest and tolerance; not a compulsory daily treatment.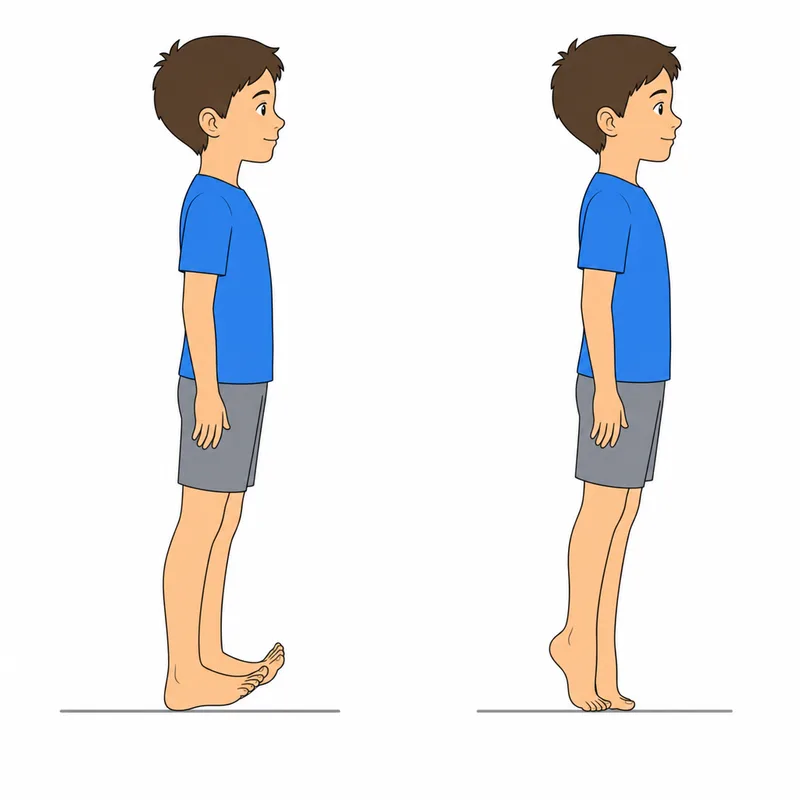
2.Toe walking
Strengthens calf muscles and improves foot control
If offered as a game, take a few tiptoe steps near an adult or stable support, without imposing foot rotation. This does not correct femoral or tibial torsion. Stop if balance is lost or pain occurs.
3-5 walks of 10-15 meters, 1-2 times daily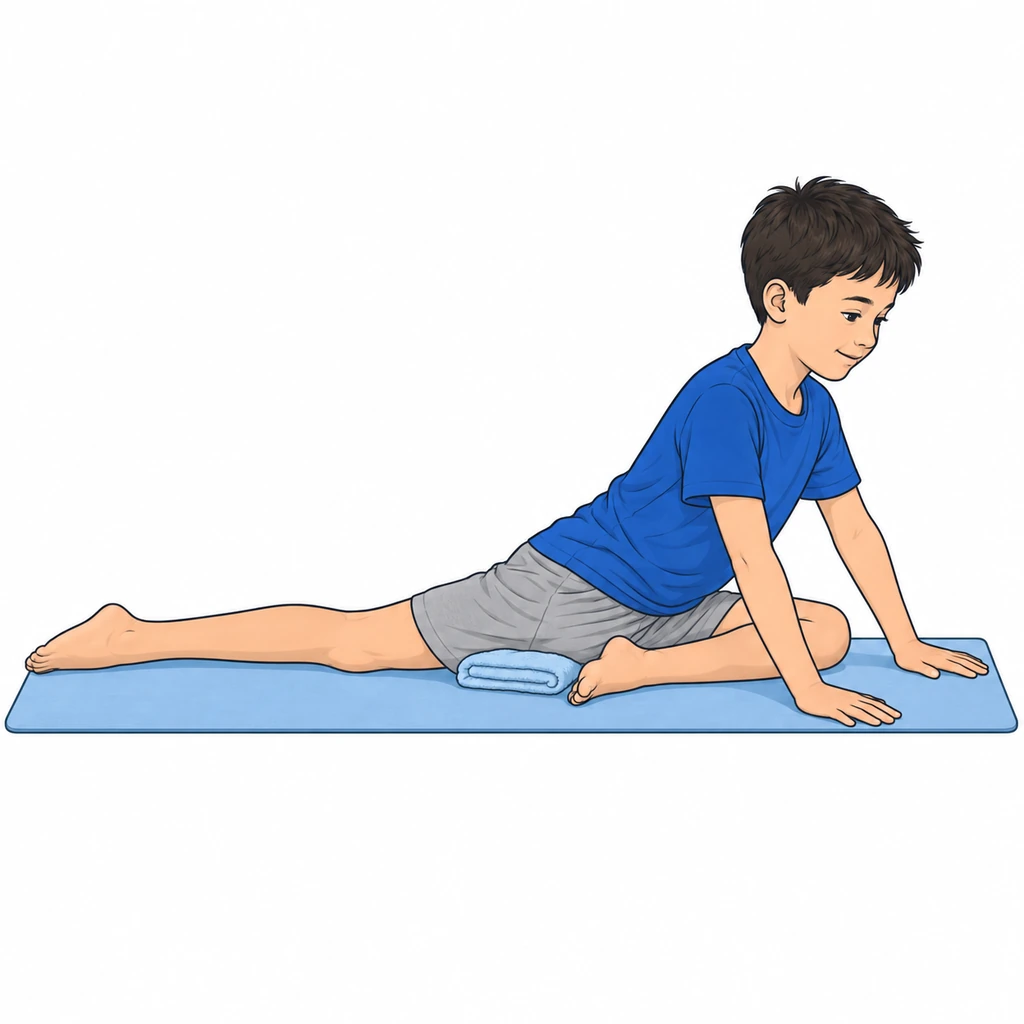
3.External rotator stretch (pigeon pose)
Stretch for muscles that externally rotate hip
Use this version only if selected and demonstrated by the physiotherapist, not to correct bony torsion. Support the body in the taught position without trying to make the shin parallel to the trunk or twisting the knee. Seek only a mild gluteal stretch; stop and reassess for hip, groin or knee pain.
3 × 30 seconds each side, 1-2 times daily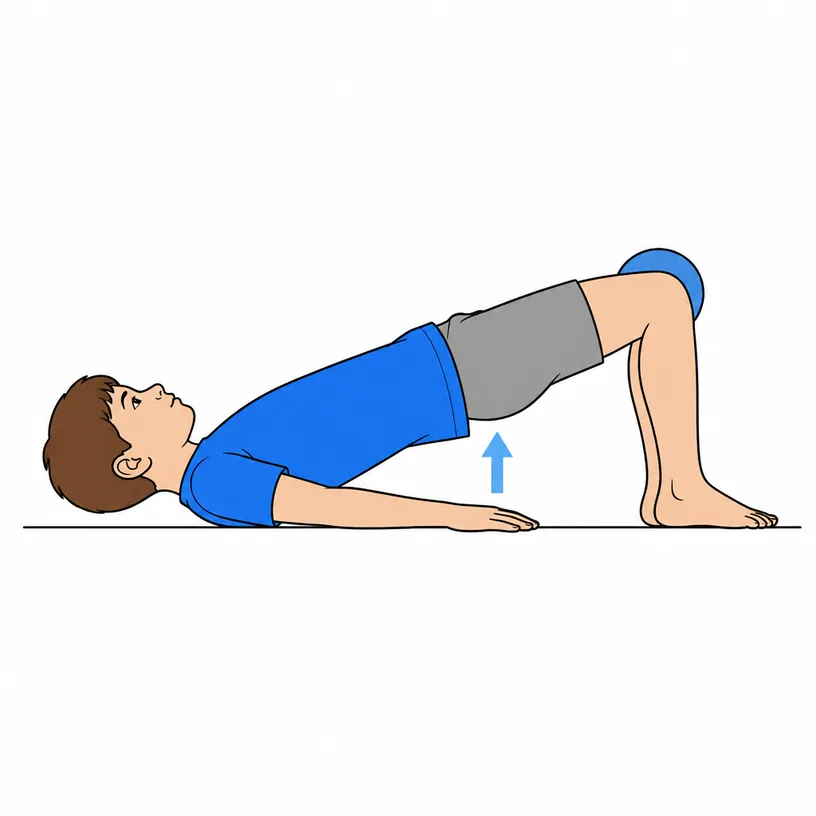
4.Bridge with a cushion between the knees
Trunk and pelvic control; this does not selectively train the internal rotators.
Lying on back, knees bent, feet on floor shoulder-width apart. Place soft ball or cushion between knees. Squeeze ball while lifting pelvis into glute bridge. Maintain compression throughout movement. Lower with control continuing to squeeze.
3 × 15 repetitions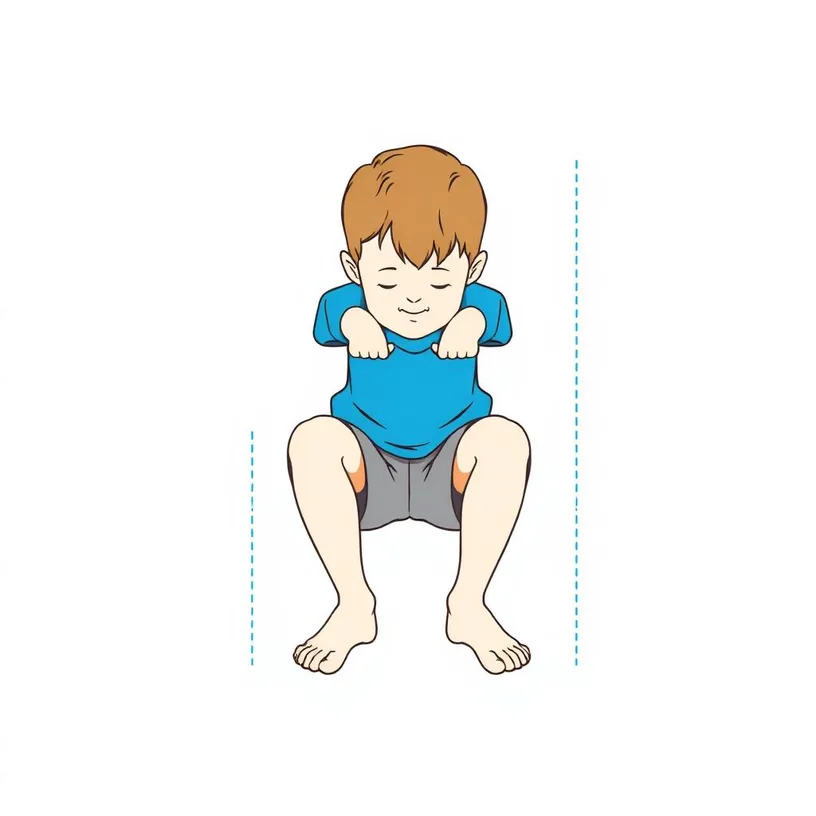
5.Squat with a natural foot position
Practice foot position control under load
If prescribed, perform a small body-weight squat near a support. Keep a comfortable foot angle and control knee movement without forcing parallel toes. Reduce depth if the movement is difficult or painful.
3 × 10 repetitions, slow and controlled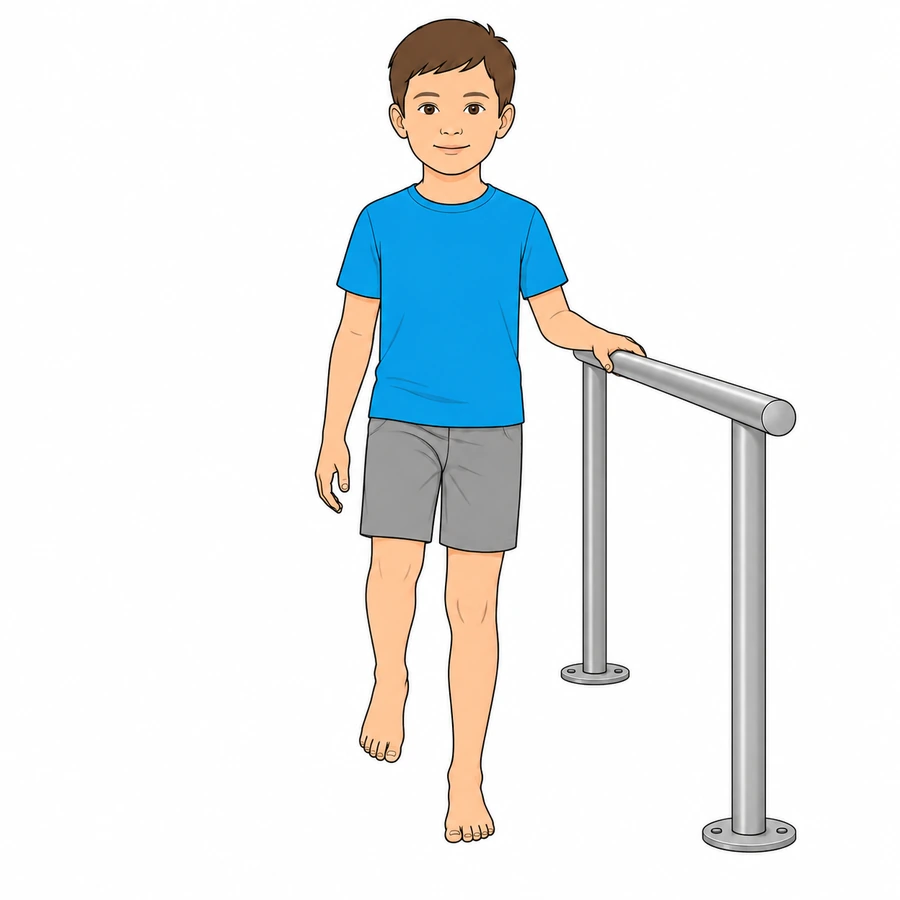
6.Balance in a comfortable stance
Improves foot position control
Near a stable support, briefly try standing on one leg with eyes open. Allow the foot its natural direction without twisting the hip or knee to straighten the toes. Put the other foot down before losing balance.
3 × 30 seconds each leg
RED FLAGS - When to stop and contact the doctor immediately
Stop the exercises immediately and contact the specialist (or go to the emergency department if severe) if any of the following occur:
- Acute or sudden pain during exercise
- Significant swelling after exercises
- Pain that progressively worsens over days
- Fever or general malaise
- Difficulty walking or using the limb after exercises
- Any neurological symptoms (tingling, numbness, sudden weakness)
- A red or hot joint, or inability to bear weight: seek prompt assessment; use emergency care if severe.
In case of doubt, always prefer a check-up over continuing the exercises.
Dott. Daniele Priano
Paediatric Orthopaedics - ASST Gaetano Pini-CTO
Content version: 21 September 2026
ortopediaevolutiva.com • Printed: 18/10/2026
 Full exercise sheet
https://ortopediaevolutiva.com/en/parents-kids/exercises/gait-rotation/out-toeing
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Exclude exercises if needed
6 of 6 exercise cards included
The full web page remains available. Your selection is not saved or shared.
Before You Start
Who is this guide for?
Activities for coordination and function after assessment. Do not force foot rotation to correct bony torsion. Limp or hip pain require review.
What you need
A stable, clear surface, comfortable clothing and a secure support. Check resistance-band anchors. Adult supervision; avoid marbles and small objects if the child may put them in their mouth, using a towel instead.
Suggested frequency
Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Common mistakes to avoid
- •Forcing a painful or unauthorised movement
- •Increasing load, resistance or frequency without the agreed rest periods
- •Doing balance exercises without stable support or supervision
⚠️ Red flags — when to stop and contact the doctor immediately
Stop exercises immediately and contact the specialist if any of the following occur:
- Acute or sudden pain during exercise
- Significant swelling after exercises
- Pain that progressively worsens over days
- Fever or general malaise
- Difficulty walking or using the limb after exercises
- Any neurological symptoms (tingling, numbness, sudden weakness)
- A red or hot joint, or inability to bear weight: seek prompt assessment; use emergency care if severe.
Detailed Exercises
- 1
Natural walking and coordination
Movement play does not change bone torsion.
Walk along a clear path or broad line as a coordination game, allowing the feet their comfortable direction. Do not force straight or outward-pointing toes or correct every step. Pain, limping or worsening requires assessment.
Play according to interest and tolerance; not a compulsory daily treatment. - 2
Toe walking
Strengthens calf muscles and improves foot control
If offered as a game, take a few tiptoe steps near an adult or stable support, without imposing foot rotation. This does not correct femoral or tibial torsion. Stop if balance is lost or pain occurs.
3-5 walks of 10-15 meters, 1-2 times daily - 3
External rotator stretch (pigeon pose)
Stretch for muscles that externally rotate hip
Use this version only if selected and demonstrated by the physiotherapist, not to correct bony torsion. Support the body in the taught position without trying to make the shin parallel to the trunk or twisting the knee. Seek only a mild gluteal stretch; stop and reassess for hip, groin or knee pain.
3 × 30 seconds each side, 1-2 times daily - 4
Bridge with a cushion between the knees
Trunk and pelvic control; this does not selectively train the internal rotators.
Lying on back, knees bent, feet on floor shoulder-width apart. Place soft ball or cushion between knees. Squeeze ball while lifting pelvis into glute bridge. Maintain compression throughout movement. Lower with control continuing to squeeze.
3 × 15 repetitions - 5
Squat with a natural foot position
Practice foot position control under load
If prescribed, perform a small body-weight squat near a support. Keep a comfortable foot angle and control knee movement without forcing parallel toes. Reduce depth if the movement is difficult or painful.
3 × 10 repetitions, slow and controlled - 6
Balance in a comfortable stance
Improves foot position control
Near a stable support, briefly try standing on one leg with eyes open. Allow the foot its natural direction without twisting the hip or knee to straighten the toes. Put the other foot down before losing balance.
3 × 30 seconds each leg
Frequently Asked Questions
Is out-toeing normal in young children?
Mild out-toeing can be normal, especially in early years. Physiological external tibial torsion is common. If marked or associated with pain/limitation, specialist evaluation is needed.
Can out-toeing cause knee problems?
Marked out-toeing can alter forces on knee during walking and running. Strengthening muscles that control rotation helps optimize biomechanics.