Paediatric Orthopaedic Specialist
Flexible metatarsus adductus
Home Exercise Program
Not every exercise listed here is suitable for every child: the selection is individual and is defined during the consultation.
For whom: After assessment of foot flexibility. Flexible cases often need observation only; parent manoeuvres are performed only when prescribed and demonstrated. Do not correct with pressure on bones or forced footwear.
Dose and frequency: Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Equipment and supervision: A stable, clear surface, an adult continuously present and an age-appropriate toy. The baby should be awake and calm; place them on their back for sleep. Follow the cast or harness programme.
Avoid: Forcing the head or a limb, persisting through crying or provoking joint clicks; Repeating manoeuvres not demonstrated with your baby; Changing straps, brace settings or wearing time without instructions.
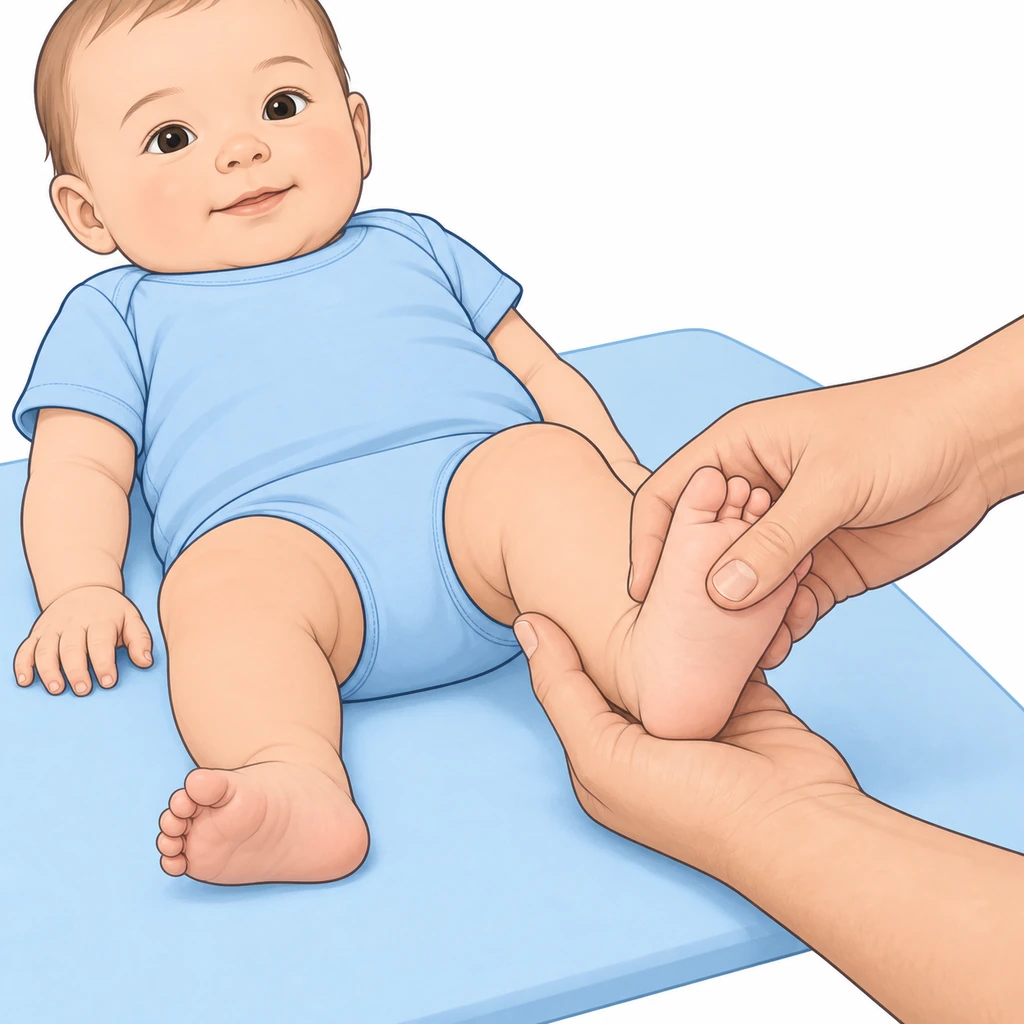
1.Forefoot mobilisation, only if prescribed
It is not needed for every flexible foot; stretching has not been shown to routinely speed correction.
The illustration shows initial foot support. The mobilisation direction must be demonstrated with your own baby.
If mobilisation is prescribed, repeat only the hand placement, direction and range demonstrated on your baby. Do not twist the heel or lever through the midfoot. Do not force a stiff foot straight. Stop if the baby cries, stiffens or appears in pain and have the technique checked.
Use only the individual dosage prescribed at the assessment.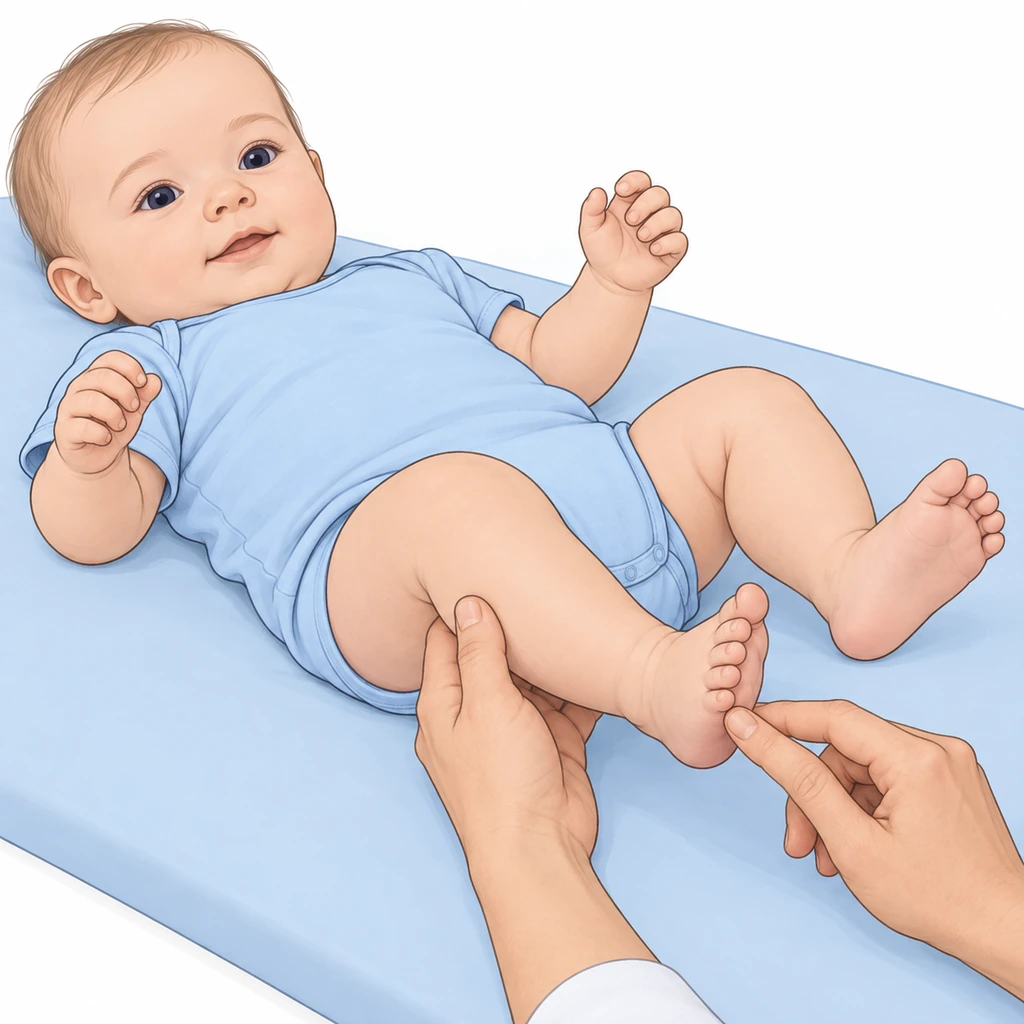
2.Active outer border stimulation
Sensory play, without expecting a fixed corrective response.
While awake, gently stroke the foot and let the baby move it freely. Do not use painful stimuli or repeatedly try to elicit a particular muscle response. Stimulation does not replace any prescribed casts or other treatment.
Short periods of play, if enjoyed.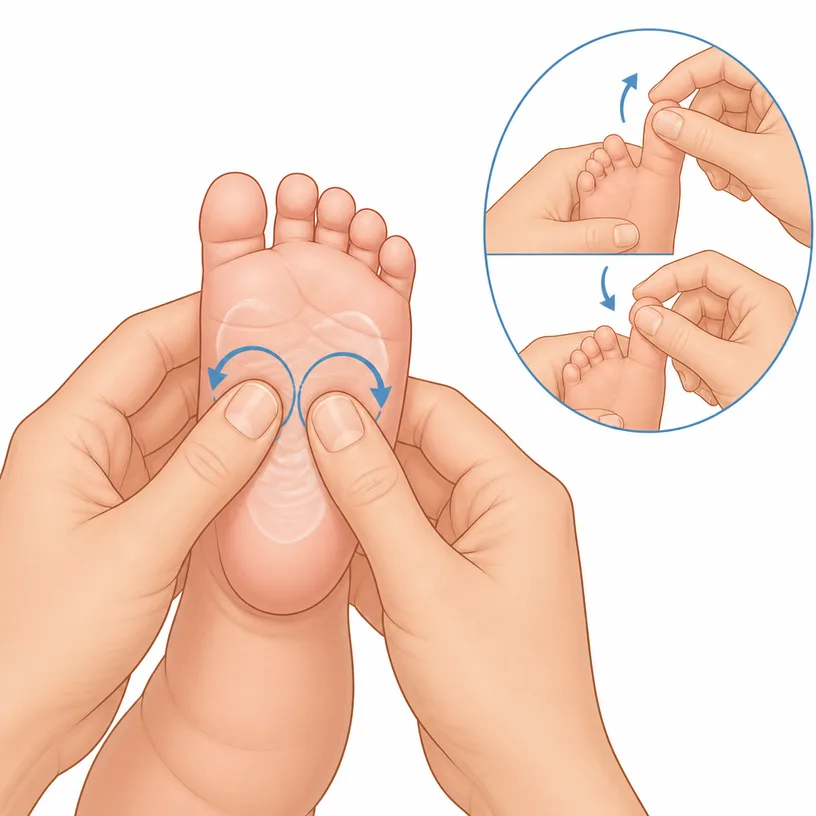
3.Preparatory massage and toe mobilization
Gentle contact for the baby’s comfort.
Stroke the foot without pulling or twisting the toes or trying to change the forefoot shape through massage. Creams or oils are not needed to make a correction effective. Stop if the skin is irritated or the baby does not enjoy it.
Briefly, if comfortable.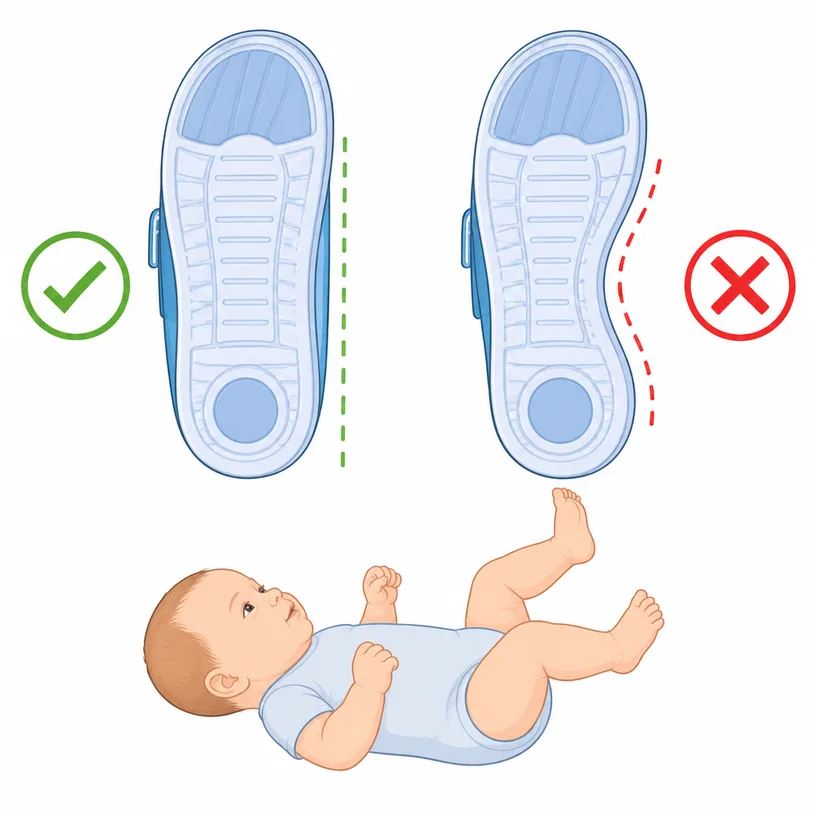
4.Positioning, clothing and footwear
Allow room for spontaneous movement.
Use clothing that does not compress the toes. For sleep, place the baby on their back on a clear, flat surface. Once walking, choose comfortable shoes of the correct size; do not buy corrective shoes to change foot alignment without an individual prescription.
During usual daily care.
RED FLAGS - When to stop and contact the doctor immediately
Stop the exercises immediately and contact the specialist (or go to the emergency department if severe) if any of the following occur:
- Persistent crying, pain or resistance during handling: stop and contact the treating clinician.
- Fever, malaise, swelling or redness: seek prompt assessment.
- Sudden reduction of limb movement, cold or discoloured toes, or a compressive cast or harness: urgent assessment.
- Sudden head tilt, especially after injury or with fever, unusual eye movements or weakness: do not stretch and seek assessment.
In case of doubt, always prefer a check-up over continuing the exercises.
Dott. Daniele Priano
Paediatric Orthopaedics - ASST Gaetano Pini-CTO
Content version: 21 September 2026
ortopediaevolutiva.com • Printed: 18/10/2026
 Full exercise sheet
https://ortopediaevolutiva.com/en/parents-kids/exercises/parent-mobilizations/metatarsus-adductus
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Exclude exercises if needed
4 of 4 exercise cards included
The full web page remains available. Your selection is not saved or shared.
Before You Start
Who is this guide for?
After assessment of foot flexibility. Flexible cases often need observation only; parent manoeuvres are performed only when prescribed and demonstrated. Do not correct with pressure on bones or forced footwear.
What you need
A stable, clear surface, an adult continuously present and an age-appropriate toy. The baby should be awake and calm; place them on their back for sleep. Follow the cast or harness programme.
Suggested frequency
Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Common mistakes to avoid
- •Forcing the head or a limb, persisting through crying or provoking joint clicks
- •Repeating manoeuvres not demonstrated with your baby
- •Changing straps, brace settings or wearing time without instructions
⚠️ Red flags — when to stop and contact the doctor immediately
Stop exercises immediately and contact the specialist if any of the following occur:
- Persistent crying, pain or resistance during handling: stop and contact the treating clinician.
- Fever, malaise, swelling or redness: seek prompt assessment.
- Sudden reduction of limb movement, cold or discoloured toes, or a compressive cast or harness: urgent assessment.
- Sudden head tilt, especially after injury or with fever, unusual eye movements or weakness: do not stretch and seek assessment.
Detailed Exercises
- 1
Forefoot mobilisation, only if prescribed
It is not needed for every flexible foot; stretching has not been shown to routinely speed correction.
The illustration shows initial foot support. The mobilisation direction must be demonstrated with your own baby.
If mobilisation is prescribed, repeat only the hand placement, direction and range demonstrated on your baby. Do not twist the heel or lever through the midfoot. Do not force a stiff foot straight. Stop if the baby cries, stiffens or appears in pain and have the technique checked.
Use only the individual dosage prescribed at the assessment. - 2
Active outer border stimulation
Sensory play, without expecting a fixed corrective response.
While awake, gently stroke the foot and let the baby move it freely. Do not use painful stimuli or repeatedly try to elicit a particular muscle response. Stimulation does not replace any prescribed casts or other treatment.
Short periods of play, if enjoyed. - 3
Preparatory massage and toe mobilization
Gentle contact for the baby’s comfort.
Stroke the foot without pulling or twisting the toes or trying to change the forefoot shape through massage. Creams or oils are not needed to make a correction effective. Stop if the skin is irritated or the baby does not enjoy it.
Briefly, if comfortable. - 4
Positioning, clothing and footwear
Allow room for spontaneous movement.
Use clothing that does not compress the toes. For sleep, place the baby on their back on a clear, flat surface. Once walking, choose comfortable shoes of the correct size; do not buy corrective shoes to change foot alignment without an individual prescription.
During usual daily care.
Frequently Asked Questions
Does metatarsus adductus correct on its own?
Many flexible feet improve with growth. A randomised trial did not show a routine advantage from parent stretching over observation. Stiffness and age guide the specialist’s assessment. Perform a mobilisation only if individually prescribed and demonstrated; do not force a stiff foot.
How do I know if metatarsus adductus is flexible or rigid?
Flexibility should be assessed during the visit. Do not force the foot straight to classify it at home. Report stiffness, pain or marked asymmetry; the specialist will show whether and how to handle it.