Paediatric Orthopaedic Specialist
Sinding-Larsen-Johansson syndrome
Home Exercise Program
Not every exercise listed here is suitable for every child: the selection is individual and is defined during the consultation.
For whom: Diagnosed apophysitis: adapt activity and strengthening to irritability. Do not automatically apply adult tendinopathy protocols or use temporary relief to play through pain.
Dose and frequency: Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Equipment and supervision: A stable, clear surface, comfortable clothing and a secure support. Check resistance-band anchors. Adult supervision; avoid marbles and small objects if the child may put them in their mouth, using a towel instead.
Avoid: Forcing a painful or unauthorised movement; Increasing load, resistance or frequency without the agreed rest periods; Doing balance exercises without stable support or supervision.
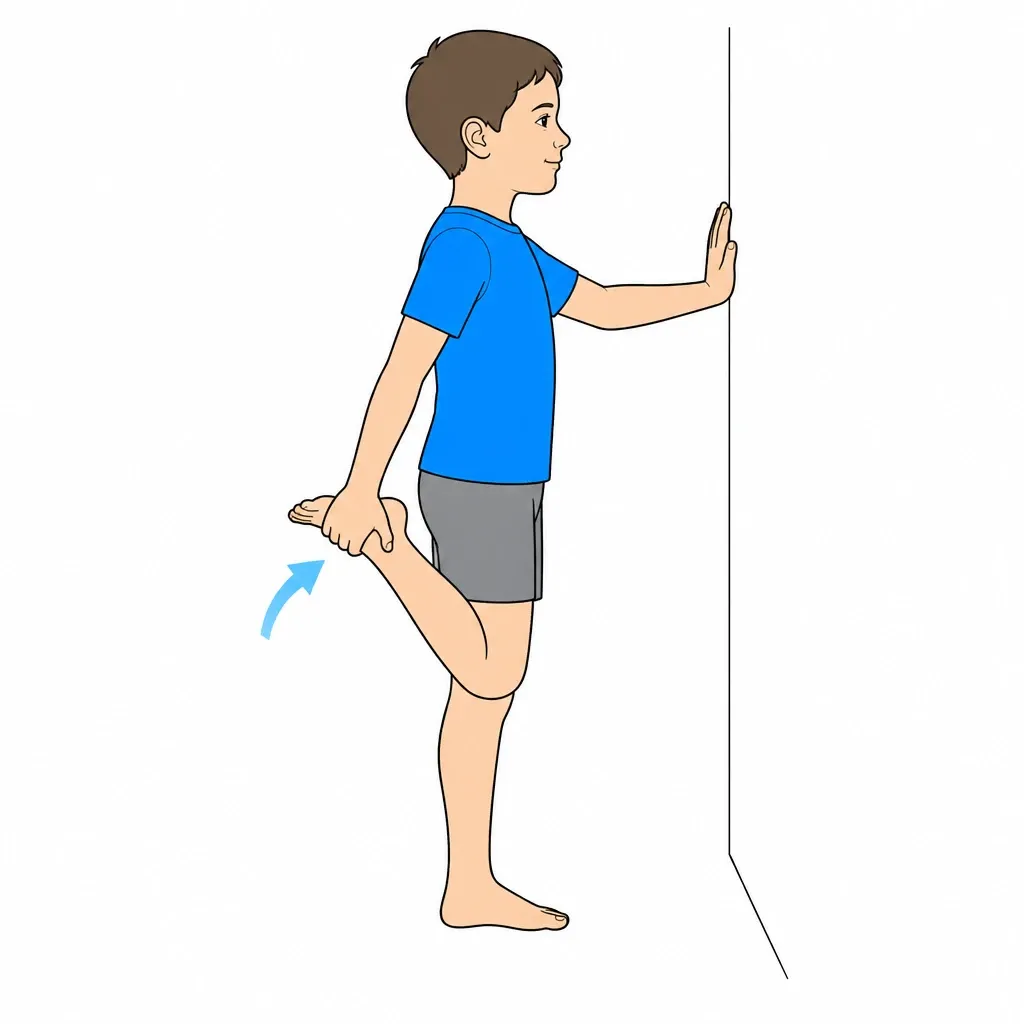
1.Quadriceps stretch, when indicated
Reduce tension on the inferior pole of the patella, where the patellar tendon originates
Standing, grasp ankle and bring heel toward buttock. Keep knees together and torso upright. Feel stretch on front of thigh. If balance is difficult, hold support. Stretch should be gentle and never painful at knee. The goal is to reduce quadriceps traction on the patella.
3 × 30 seconds each side, 2-3 times daily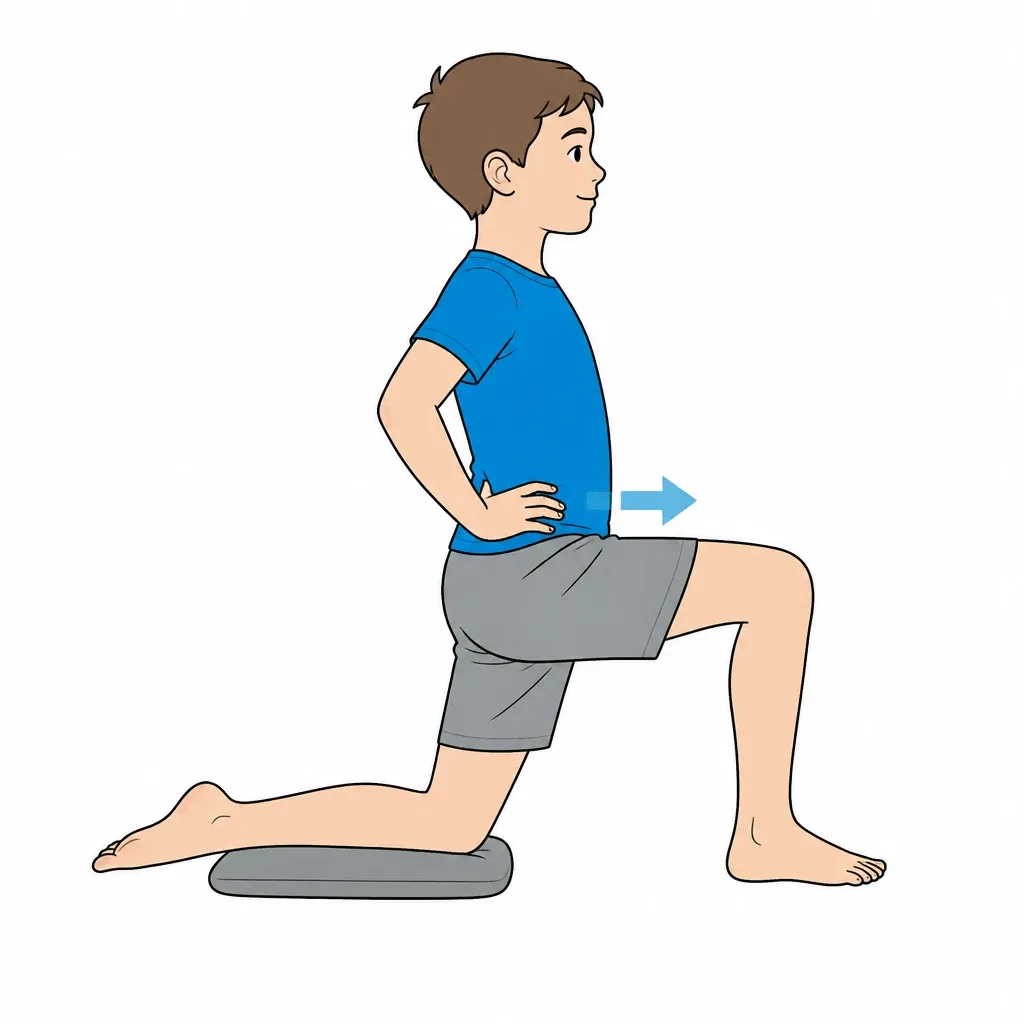
2.Hip flexor stretch (iliopsoas)
Reduces tension contributing to anterior knee overload
Lunge with back knee on cushion. Squeeze glute of back leg and GENTLY push hips forward. Stretch felt in front of back leg's hip. DON'T arch back. Keep torso vertical.
3 × 30 seconds each side, twice daily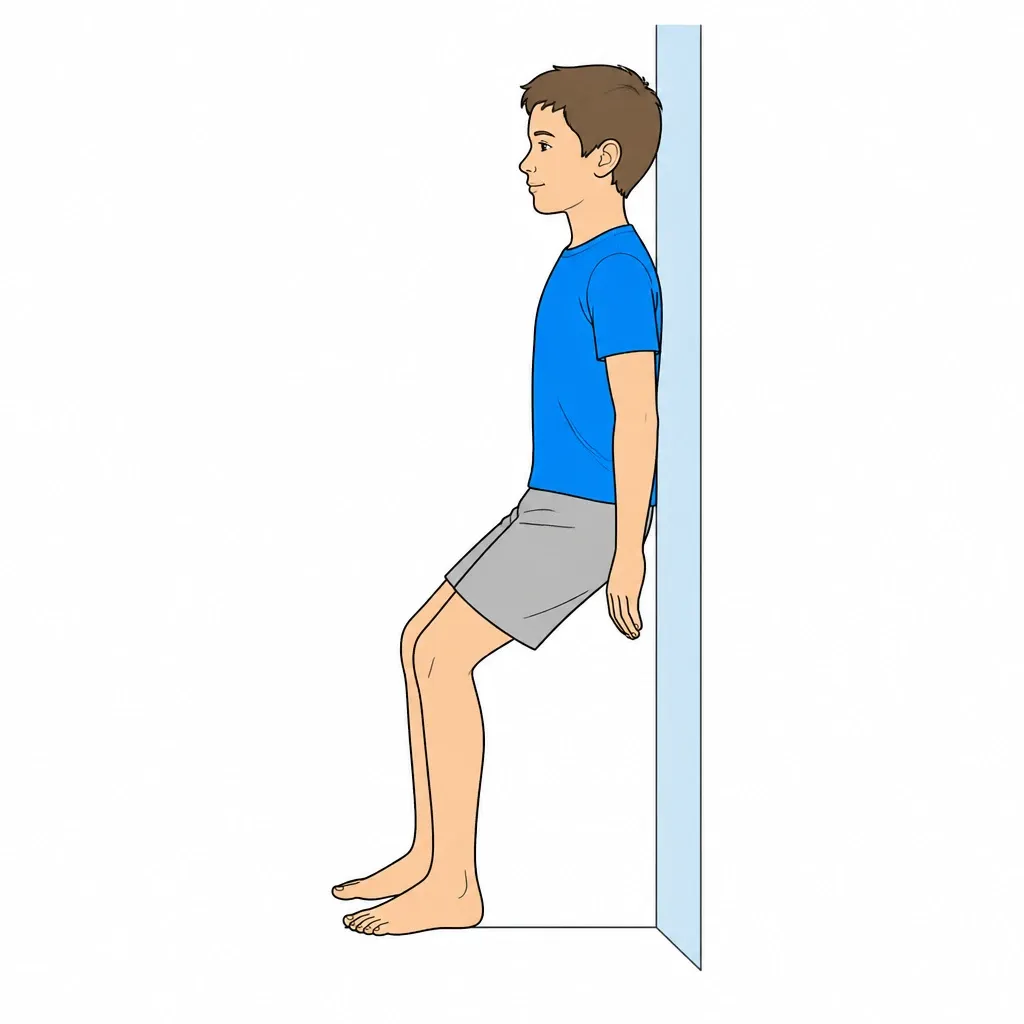
3.Isometric wall sit (low range)
A static contraction at a tolerated angle; not necessarily suitable during the acute phase.
Use only if selected in the programme and tolerated. With your back against the wall and feet stable, lower to the agreed shallow knee-bend angle and hold without local pain. If pain occurs, stop and review loading, angle or exercise choice with the physiotherapist. A wall sit is not automatically safer than a squat during the acute phase: an isometric contraction also loads the extensor mechanism. Do not use it to reduce pain and keep playing.
3-5 × 20-30 seconds, progressing when easy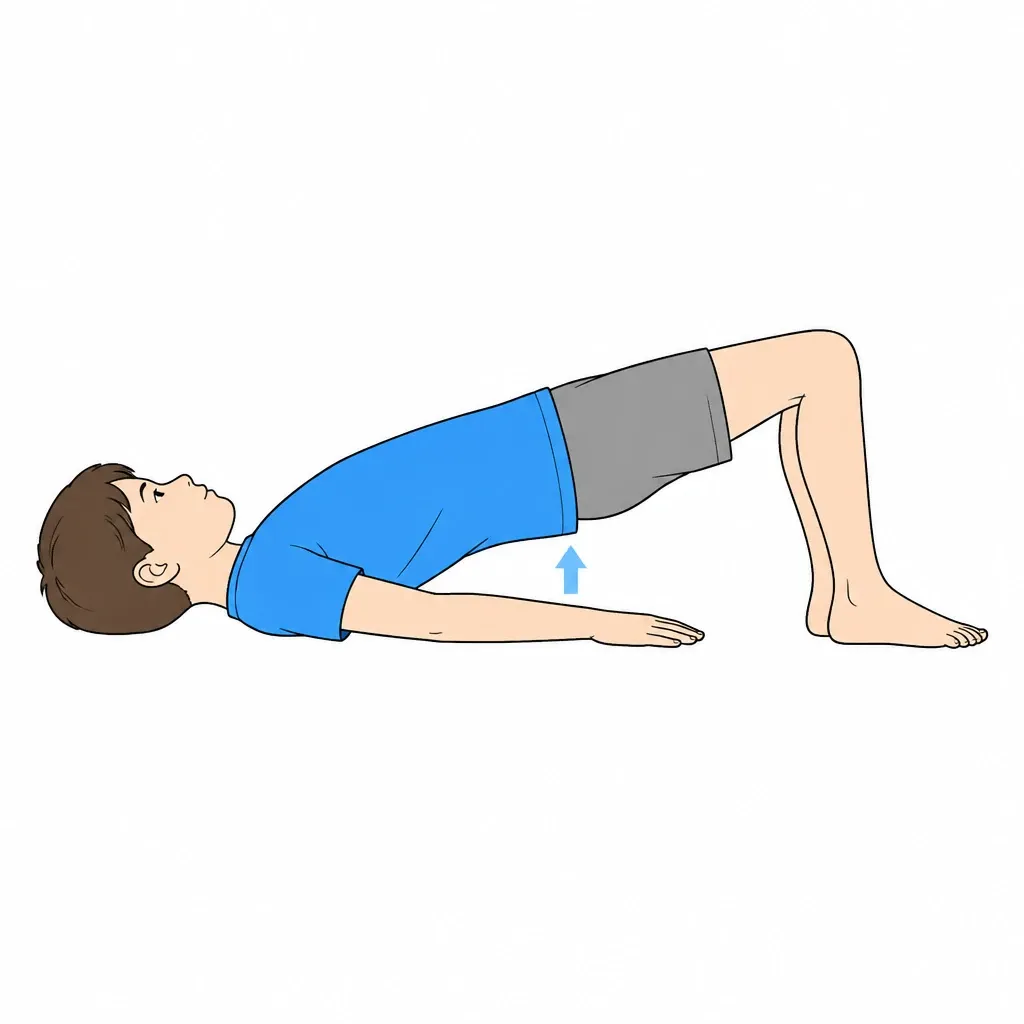
4.Glute bridge
Gluteal and posterior-chain strengthening, if tolerated by the knee.
Lying on your back with knees bent and feet on the floor, lift the pelvis without arching the back, hold briefly and lower with control. Select support and range with the physiotherapist. A bridge does not eliminate knee loading: stop for local pain.
3 × 15 repetitions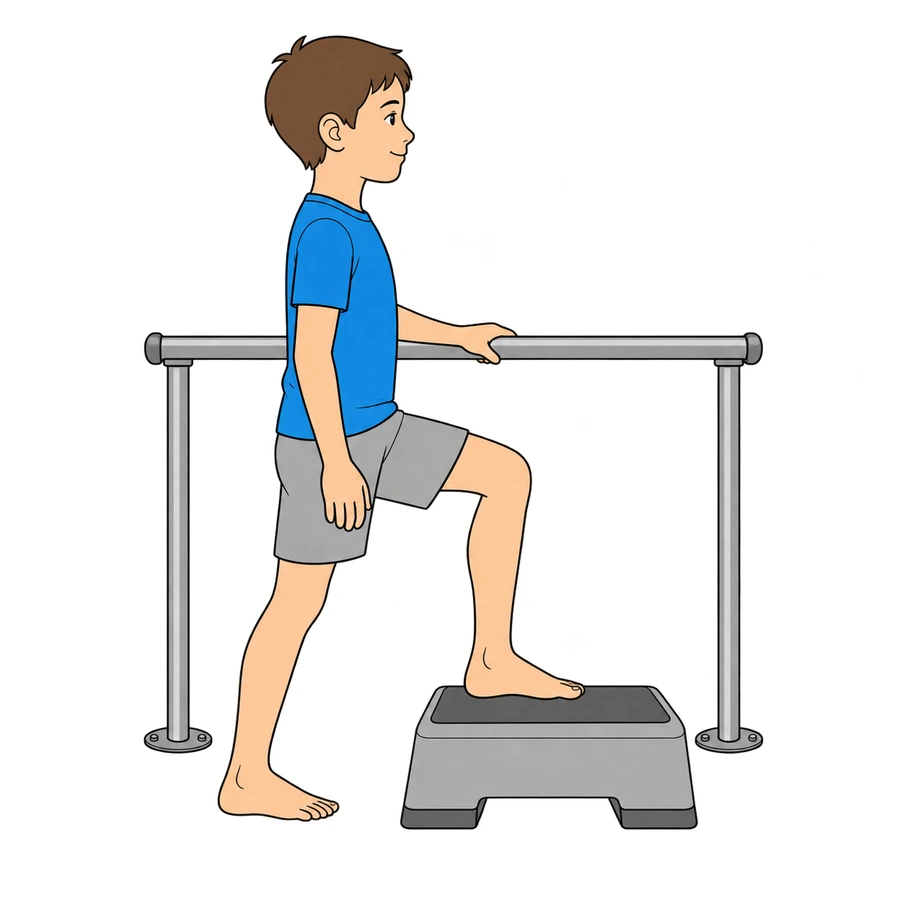
5.Gradual step-up
Progressive functional strengthening when pain decreases
ONLY when acute pain has subsided. Step up onto low step (10-15 cm) with control. Focus on technique: knee aligned over foot, not inward. Start with very low step and gradually increase height. If pain returns, lower the step.
3 × 10 per leg, starting with low step
6.Sports load management
Activity modification is fundamental - follows same principle as Osgood-Schlatter
Reduce running, jumping and movements that provoke pain. Choose alternative activities only if tolerated: cycling and swimming may also need adaptation. Agree a gradual return of volume and then intensity, checking symptoms during, afterwards and the following morning. If limping or worsening occurs, reduce loading and reassess.
Personalized plan discussed during visit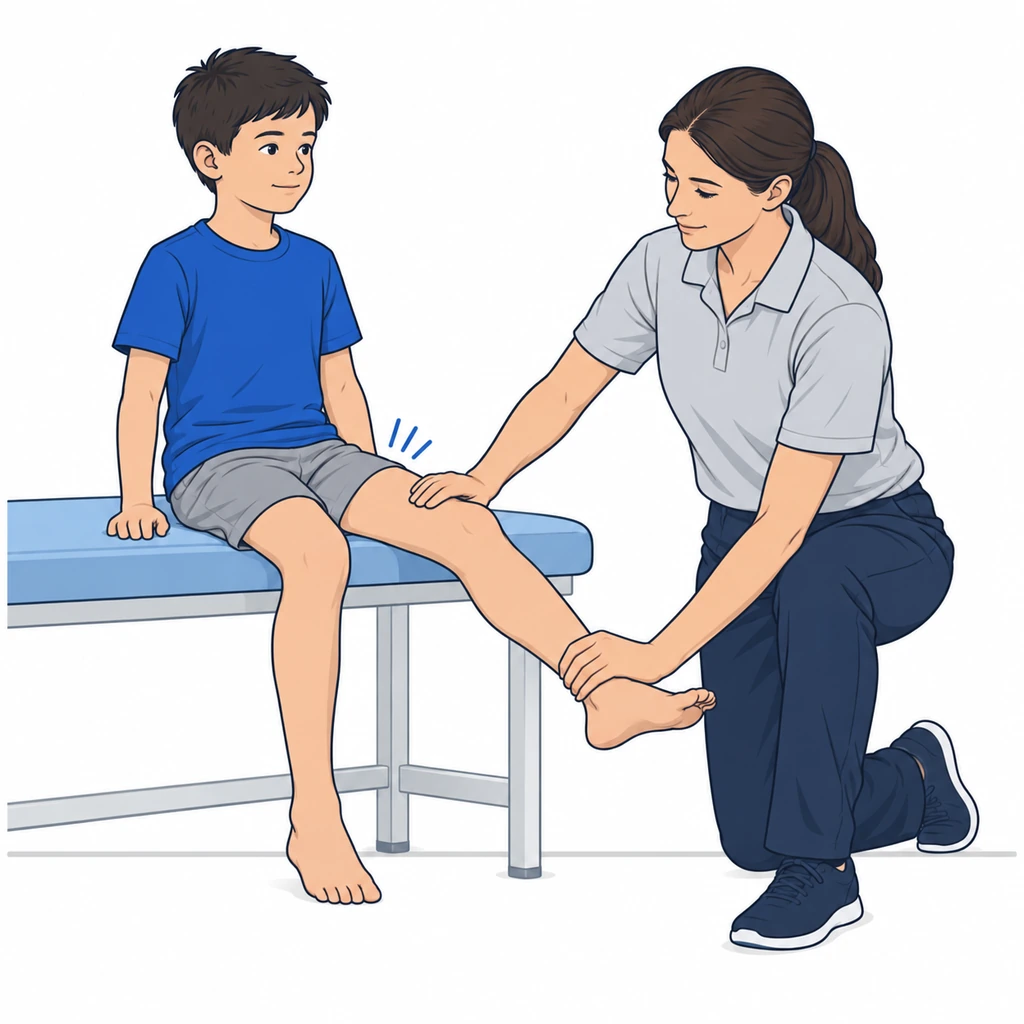
7.Quadriceps isometric, if tolerated
Loading must be adapted to apophysitis; this is not pain relief to enable playing through pain.
Sit in the position taught by the physiotherapist and tighten the thigh against stable resistance without moving the knee. Do not trap the foot under furniture. Use a comfortable effort without local pain or breath holding. Stop or reduce the effort if pain occurs; any immediate relief does not authorise return to sport.
Agree dosage according to age, strength and symptoms; start with a light effort.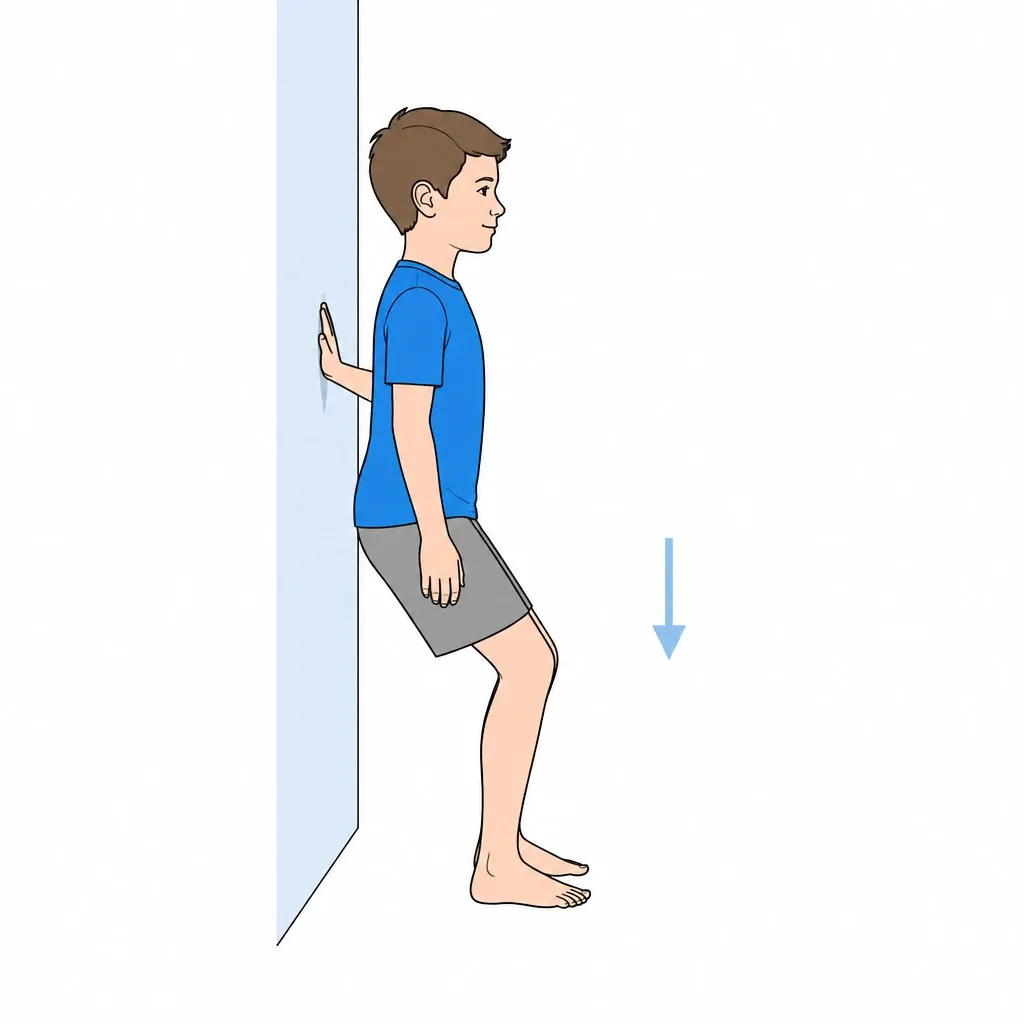
8.Slow squat with individual progression
Gradual strengthening after reducing activities that provoke pain.
Start with body weight near a stable support, using a shallow squat in the agreed pain-free range. Lower and rise slowly with controlled knees and feet. Do not add weights or depth based only on the week reached. Progress with the physiotherapist when technique is sound and there is no pain, limp or worsening the following day.
Individualise sets, repetitions and recovery days; no automatic increase in weights.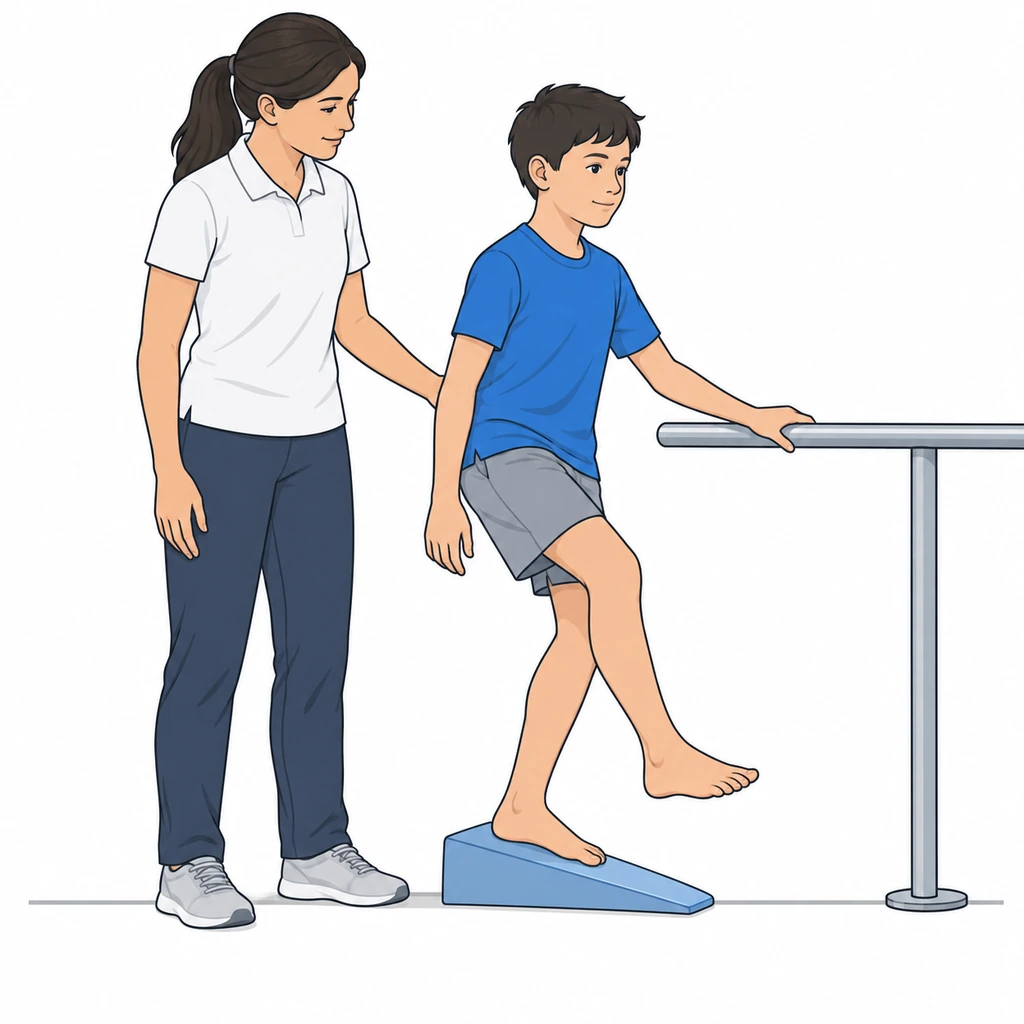
9.Single-leg progression, only if prescribed
An advanced option that is not a required part of SLJ treatment.
Use the decline-board variant only if prescribed; the slope and squat depth are individual.
Do not independently start a single-leg decline squat. This demanding exercise has mainly been studied for adult tendinopathy and is not a standard prescription for apophysitis. If selected by the physiotherapist, use only the demonstrated support, incline, depth and load, without pain or subsequent worsening.
Use only the individually prescribed dose after technique has been checked.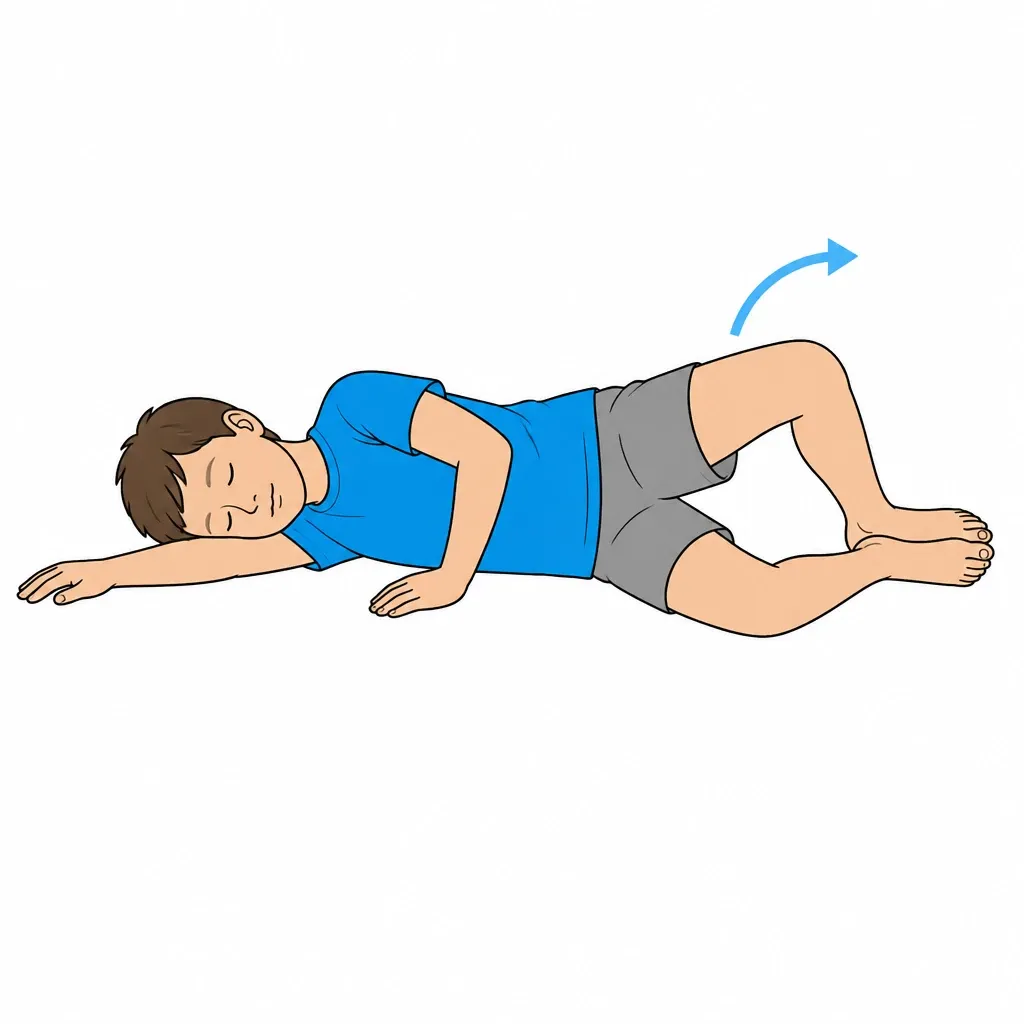
10.Gluteus medius and core strengthening
A stable hip reduces repeated overload on the lower patellar pole
Clamshell: lie on your side with knees bent and feet together; open the top knee while keeping the pelvis still. Side plank: if prescribed, begin on the forearm and knees. Both require selection and dosage according to tolerance; do not assume they place no load on the knee.
Clamshell 3 × 15 each side; side plank 3 × 20-30 seconds
11.Gradual return to jumping and running
The tendon must be re-accustomed to explosive load before returning to the team
Resume when daily activities and basic exercises are pain-free without limping, and the physiotherapist confirms recovery of control and strength. Introduce straight-line running, then acceleration, jumping and direction changes according to the sport. Progression requires sound technique and no worsening the following day; elapsed weeks alone are insufficient. Complete full training before competition.
Individual progression checked with the treating clinician; reduce loading if symptoms increase.
RED FLAGS - When to stop and contact the doctor immediately
Stop the exercises immediately and contact the specialist (or go to the emergency department if severe) if any of the following occur:
- Acute or sudden pain during exercise
- Significant swelling after exercises
- Pain that progressively worsens over days
- Fever or general malaise
- Difficulty walking or using the limb after exercises
- Any neurological symptoms (tingling, numbness, sudden weakness)
- A red or hot joint, or inability to bear weight: seek prompt assessment; use emergency care if severe.
In case of doubt, always prefer a check-up over continuing the exercises.
Dott. Daniele Priano
Paediatric Orthopaedics - ASST Gaetano Pini-CTO
Content version: 21 September 2026
ortopediaevolutiva.com • Printed: 18/10/2026
 Full exercise sheet
https://ortopediaevolutiva.com/en/parents-kids/exercises/knee/sinding-larsen
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Exclude exercises if needed
11 of 11 exercise cards included
The full web page remains available. Your selection is not saved or shared.
Before You Start
Who is this guide for?
Diagnosed apophysitis: adapt activity and strengthening to irritability. Do not automatically apply adult tendinopathy protocols or use temporary relief to play through pain.
What you need
A stable, clear surface, comfortable clothing and a secure support. Check resistance-band anchors. Adult supervision; avoid marbles and small objects if the child may put them in their mouth, using a towel instead.
Suggested frequency
Perform only the exercises selected during the visit. The listed dosages are examples to adapt: follow the dose, frequency, rest and progression prescribed for age, symptoms and phase. Do not automatically perform the whole list.
Common mistakes to avoid
- •Forcing a painful or unauthorised movement
- •Increasing load, resistance or frequency without the agreed rest periods
- •Doing balance exercises without stable support or supervision
⚠️ Red flags — when to stop and contact the doctor immediately
Stop exercises immediately and contact the specialist if any of the following occur:
- Acute or sudden pain during exercise
- Significant swelling after exercises
- Pain that progressively worsens over days
- Fever or general malaise
- Difficulty walking or using the limb after exercises
- Any neurological symptoms (tingling, numbness, sudden weakness)
- A red or hot joint, or inability to bear weight: seek prompt assessment; use emergency care if severe.
Detailed Exercises
- 1
Quadriceps stretch, when indicated
Reduce tension on the inferior pole of the patella, where the patellar tendon originates
Standing, grasp ankle and bring heel toward buttock. Keep knees together and torso upright. Feel stretch on front of thigh. If balance is difficult, hold support. Stretch should be gentle and never painful at knee. The goal is to reduce quadriceps traction on the patella.
3 × 30 seconds each side, 2-3 times daily - 2
Hip flexor stretch (iliopsoas)
Reduces tension contributing to anterior knee overload
Lunge with back knee on cushion. Squeeze glute of back leg and GENTLY push hips forward. Stretch felt in front of back leg's hip. DON'T arch back. Keep torso vertical.
3 × 30 seconds each side, twice daily - 3
Isometric wall sit (low range)
A static contraction at a tolerated angle; not necessarily suitable during the acute phase.
Use only if selected in the programme and tolerated. With your back against the wall and feet stable, lower to the agreed shallow knee-bend angle and hold without local pain. If pain occurs, stop and review loading, angle or exercise choice with the physiotherapist. A wall sit is not automatically safer than a squat during the acute phase: an isometric contraction also loads the extensor mechanism. Do not use it to reduce pain and keep playing.
3-5 × 20-30 seconds, progressing when easy - 4
Glute bridge
Gluteal and posterior-chain strengthening, if tolerated by the knee.
Lying on your back with knees bent and feet on the floor, lift the pelvis without arching the back, hold briefly and lower with control. Select support and range with the physiotherapist. A bridge does not eliminate knee loading: stop for local pain.
3 × 15 repetitions - 5
Gradual step-up
Progressive functional strengthening when pain decreases
ONLY when acute pain has subsided. Step up onto low step (10-15 cm) with control. Focus on technique: knee aligned over foot, not inward. Start with very low step and gradually increase height. If pain returns, lower the step.
3 × 10 per leg, starting with low step - 6
Sports load management
Activity modification is fundamental - follows same principle as Osgood-Schlatter
Reduce running, jumping and movements that provoke pain. Choose alternative activities only if tolerated: cycling and swimming may also need adaptation. Agree a gradual return of volume and then intensity, checking symptoms during, afterwards and the following morning. If limping or worsening occurs, reduce loading and reassess.
Personalized plan discussed during visit - 7
Quadriceps isometric, if tolerated
Loading must be adapted to apophysitis; this is not pain relief to enable playing through pain.
Sit in the position taught by the physiotherapist and tighten the thigh against stable resistance without moving the knee. Do not trap the foot under furniture. Use a comfortable effort without local pain or breath holding. Stop or reduce the effort if pain occurs; any immediate relief does not authorise return to sport.
Agree dosage according to age, strength and symptoms; start with a light effort. - 8
Slow squat with individual progression
Gradual strengthening after reducing activities that provoke pain.
Start with body weight near a stable support, using a shallow squat in the agreed pain-free range. Lower and rise slowly with controlled knees and feet. Do not add weights or depth based only on the week reached. Progress with the physiotherapist when technique is sound and there is no pain, limp or worsening the following day.
Individualise sets, repetitions and recovery days; no automatic increase in weights. - 9
Single-leg progression, only if prescribed
An advanced option that is not a required part of SLJ treatment.
Use the decline-board variant only if prescribed; the slope and squat depth are individual.
Do not independently start a single-leg decline squat. This demanding exercise has mainly been studied for adult tendinopathy and is not a standard prescription for apophysitis. If selected by the physiotherapist, use only the demonstrated support, incline, depth and load, without pain or subsequent worsening.
Use only the individually prescribed dose after technique has been checked. - 10
Gluteus medius and core strengthening
A stable hip reduces repeated overload on the lower patellar pole
Clamshell: lie on your side with knees bent and feet together; open the top knee while keeping the pelvis still. Side plank: if prescribed, begin on the forearm and knees. Both require selection and dosage according to tolerance; do not assume they place no load on the knee.
Clamshell 3 × 15 each side; side plank 3 × 20-30 seconds - 11
Gradual return to jumping and running
The tendon must be re-accustomed to explosive load before returning to the team
Resume when daily activities and basic exercises are pain-free without limping, and the physiotherapist confirms recovery of control and strength. Introduce straight-line running, then acceleration, jumping and direction changes according to the sport. Progression requires sound technique and no worsening the following day; elapsed weeks alone are insufficient. Complete full training before competition.
Individual progression checked with the treating clinician; reduce loading if symptoms increase.
Frequently Asked Questions
What is the difference between Sinding-Larsen-Johansson and Osgood-Schlatter?
Both are traction osteochondroses of the knee extensor mechanism. Osgood-Schlatter affects the tibial tuberosity (below the knee), Sinding-Larsen-Johansson the inferior pole of the patella (above the patellar tendon). Treatment is similar: stretching, sports load management and progressive strengthening.
At what age does Sinding-Larsen-Johansson syndrome appear?
It typically appears between ages 10 and 14, slightly earlier than Osgood-Schlatter, during rapid growth spurts. It's more common in athletic children, especially those in sports involving jumping and running (soccer, basketball, volleyball).