Non-operative pathway for a stable talar osteochondral lesion, separate from ankle-sprain rehabilitation.
Protection and progression follow lesion reassessment, not a sprain timetable.
The treating team selects exercises individually during the consultation. Choosing or progressing exercises without medical guidance can be dangerous. Follow only the assigned phase, activities and amounts; no progression is automatic.
Scope and before starting
For a stable osteochondral lesion of the talus, involving ankle cartilage and the bone beneath it. The treating clinician must have selected non-operative treatment. Not for unstable fragments, locking or after surgery; less pain does not mean running is cleared.
Record first
Lesion stability/site, weight bearing, any cast or brace, permitted motion and review date.
Progression
Loading, motion and impact require separate clearance. Do not remove immobilisation to follow an illustration. Functional checks are a practical checklist adapted from the sources, not validated paediatric return-to-sport tests.
Perform only the exercises selected for you, at the prescribed dose. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Do not try running or hopping to check whether you have healed.
Report pain or swelling that develops after the session too.
Treatment phases and illustrated exercises
Exercises are shown in their assigned starting phase, with their instructions and precautions. The physiotherapist selects them for the individual plan; the complete protocol is not a prescription to perform them all.
Respect the minimum times and protection required for the procedure. Time alone does not authorise progression: the treating team checks the clinical criteria.
1. Protection
For the prescribed period
Goals
Reduce symptoms and lesion loading.
Physiotherapy plan
Use crutches as prescribed and check transfers.
Move free toes and use static hip/knee contractions without loading or moving the protected ankle.
Precautions
No sport, running or jumping; maintain the prescribed cast/brace.
Criteria the treating team checks before progression
Protection followed and symptoms controlled.
Motion permitted by the treating clinician.
Illustrated exercise options
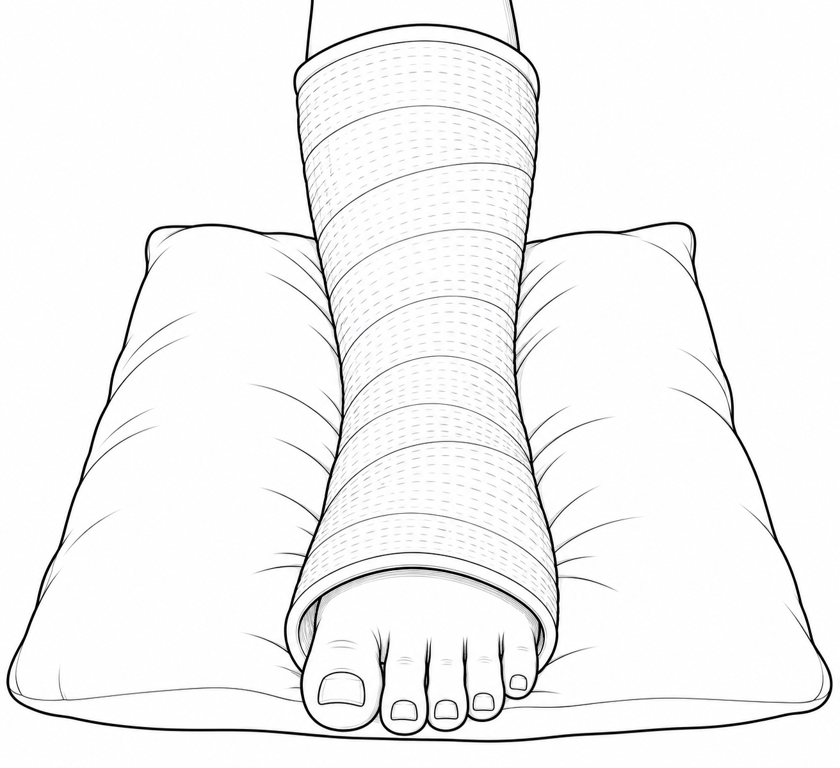
Free-toe movement
Only for toes left free and if allowed; keep the cast or brace as prescribed.
With the leg supported and no weight through the foot, gently move the free toes.
You may gently spread them as shown if comfortable; do not pull them with your hands.
Do not move the ankle inside the cast or remove immobilisation to follow the figure.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
2. Unloaded motion
When brace removal for exercises is allowed
Goals
Restore comfortable ankle motion.
Physiotherapy plan
Slow active up/down movement within the permitted range; gentle ankle isometrics only if the clinician allows them, never pushing against cast or brace.
Maintain proximal strength and correct crutch use.
Precautions
Do not force dorsiflexion or rotations; no bands, calf raises or single-leg balance until cleared.
Criteria the treating team checks before progression
Permitted movement without deep pain or reactive swelling.
Loading and strengthening cleared.
Illustrated exercise options
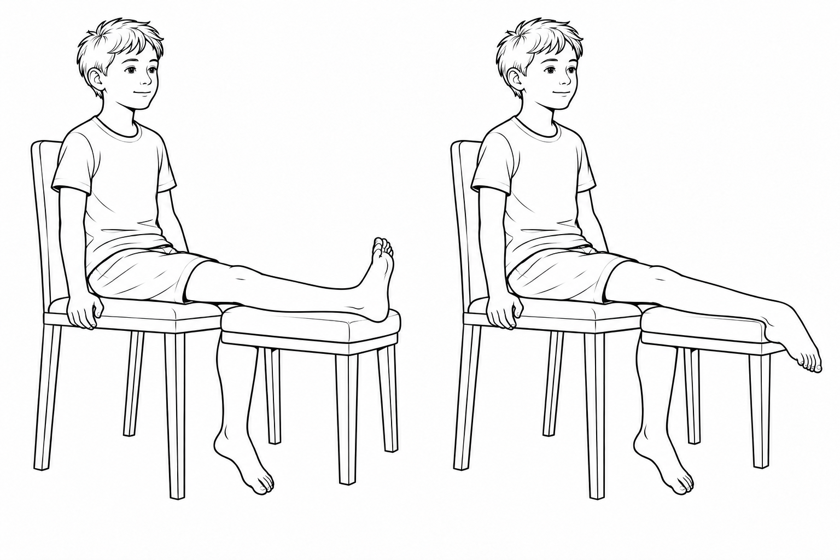
Unloaded ankle motion
Only after clearance for motion and brace removal for this exercise.
With the leg supported and foot free, slowly move the foot towards and away from you within the permitted range.
The figure shows the two directions, not the range to achieve. Do not use bands or manual pressure.
Stop for deep pain; do not add rotations unless authorised.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
3. Walking and strength
After loading clearance
Goals
Walk without a limp; restore strength and control.
Physiotherapy plan
Retrain gait and reduce aids according to control.
After strengthening clearance, bands in permitted directions and supported bilateral calf raises; firm-ground balance with nearby support, then single-leg stance if cleared. Cycling if tolerated.
Precautions
No trial hopping or running to test healing.
Criteria the treating team checks before progression
Walking and selected work without pain or new swelling.
Favourable lesion assessment and impact clearance.
Illustrated exercise options
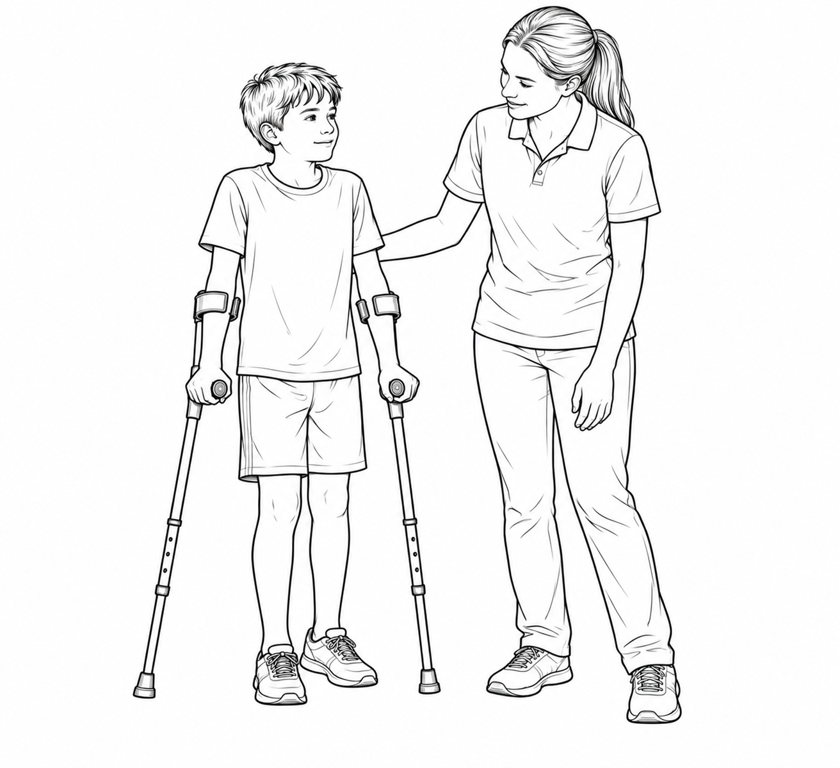
Walking with crutches and prescribed foot contact
Only when some foot contact is permitted. The figure does not show a fully non-weight-bearing pattern: if contact is prohibited, you need specific instruction.
Have the crutches adjusted and learn the sequence appropriate to your loading limit from the physiotherapist.
Practise on a level, clear path with an adult nearby; the foot contacts the ground only as prescribed.
Stop if limping, pain or fatigue increase. Practise stairs with assistance; do not stop using crutches solely because pain decreases.
Dose and progression: Agreed short distances with rests; duration and frequency depend on prescribed loading and gait quality.
Resisted ankle eversion
Only after clearance for resisted eversion and demonstration by the physiotherapist.
Sit with the legs supported; have the band positioned to pull inwards, as shown.
Move the forefoot slightly outwards while keeping the leg still; the movement should not come from the hip.
Return slowly without letting the band snap back. Do not force end range; stop for deep pain.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
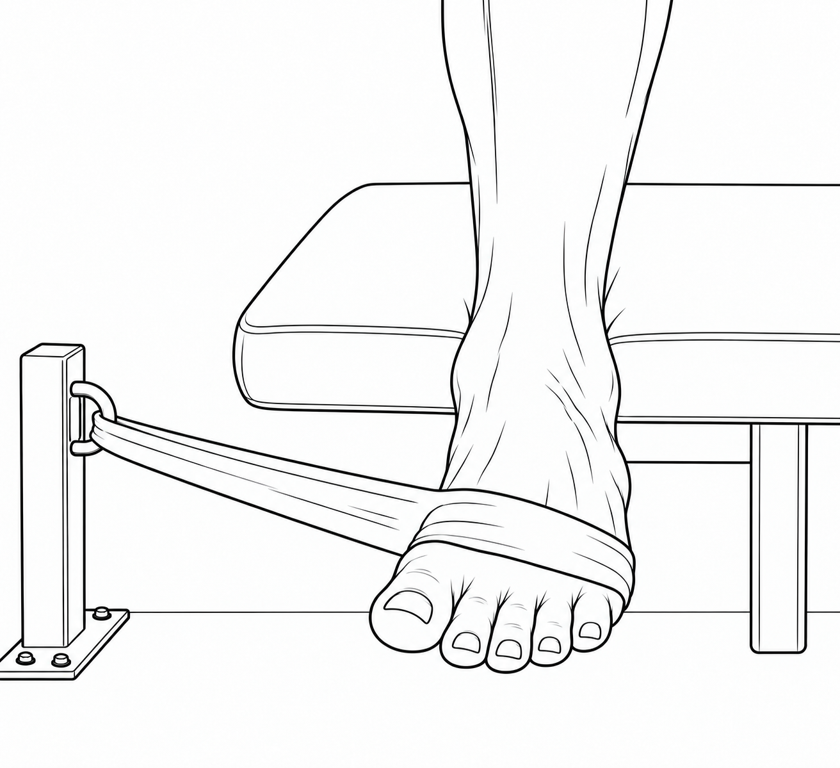
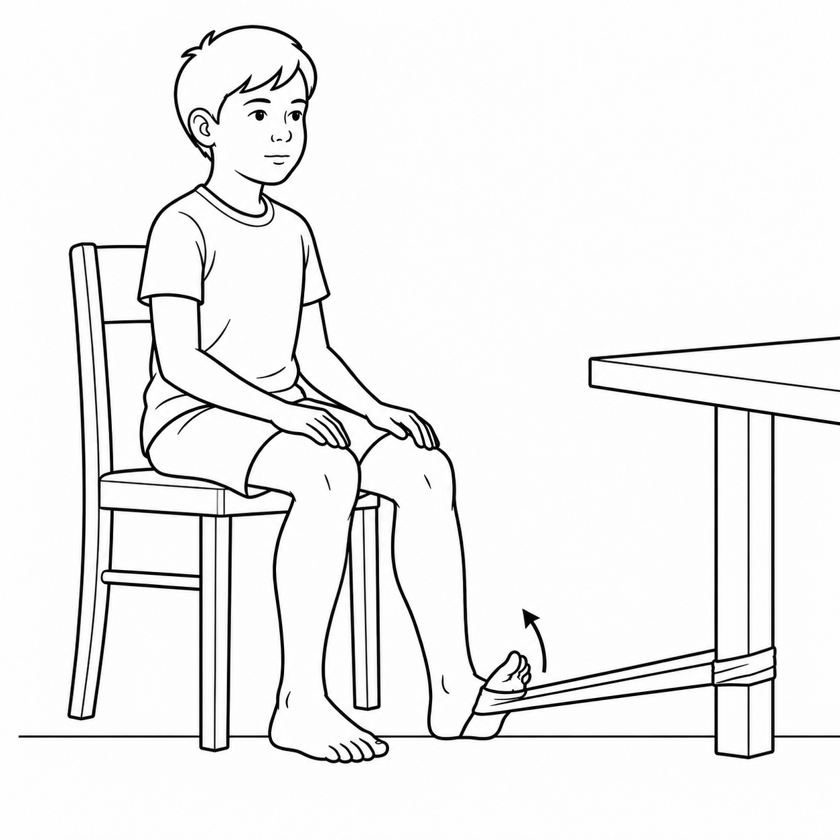
Resisted ankle dorsiflexion
When ankle strengthening and resisted dorsiflexion are permitted; have the physiotherapist check the band setup.
Sit with the leg supported. Secure the band in front of the foot to a safe anchor as shown, without compressing the foot.
Slowly draw the foot towards you within the permitted range, keeping the leg still; return without jerking.
Do not aim for maximal dorsiflexion. Stop for deep pain or painful pinching at the front of the ankle.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
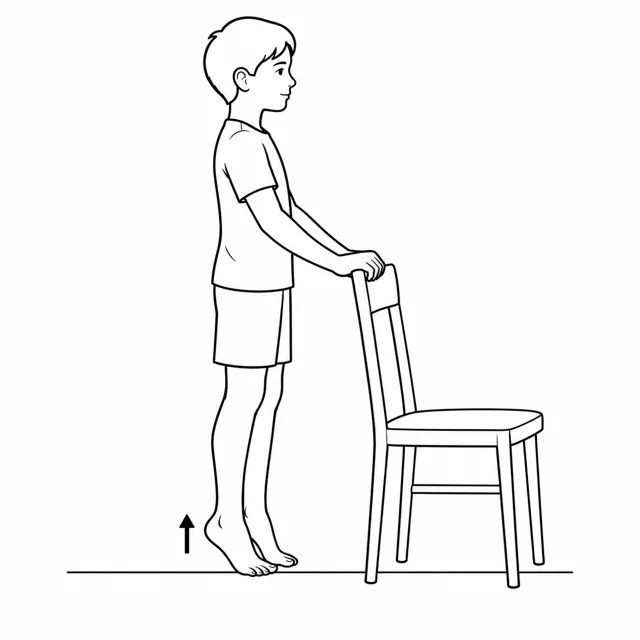
Supported double-leg calf raises
Only after clearance for full weight bearing and calf strengthening.
On a level floor, place your hands on a stable support as illustrated.
With both feet, slowly raise the heels and lower them with control.
Do not independently progress to one leg or a step edge. Stop for joint pain and monitor the subsequent response.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
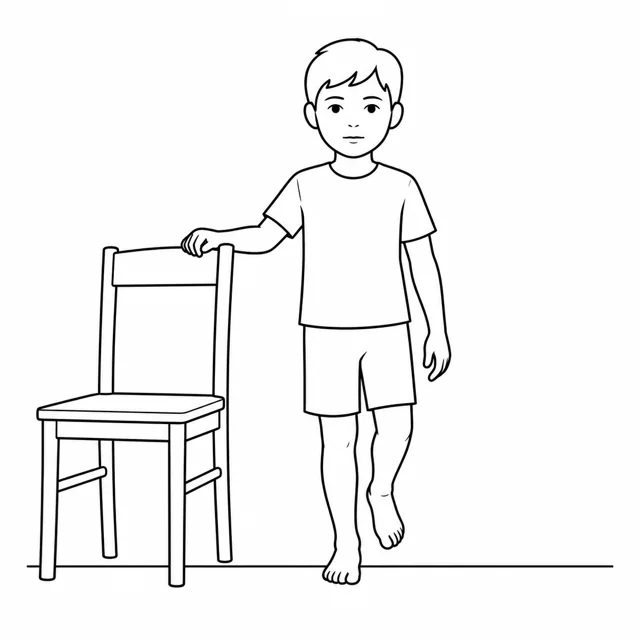
Firm-ground balance
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
On firm ground with eyes open, slightly lift the other foot while keeping the pelvis level.
Keep one hand on a stable support as illustrated; an adult must be able to assist the child.
Put the free foot down before losing control. Do not add cushions, closed eyes or perturbations.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
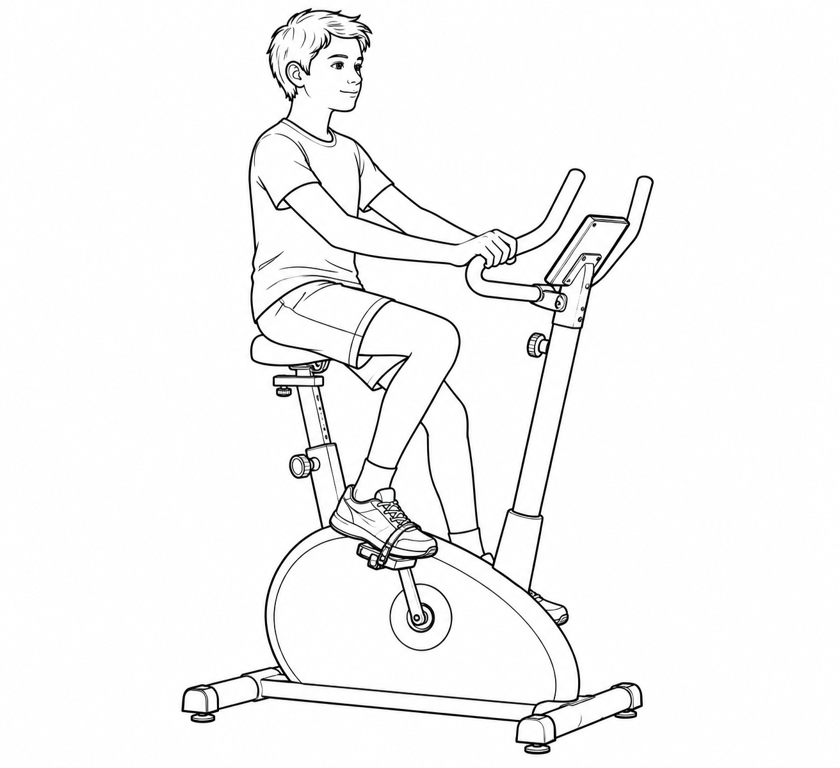
Easy stationary cycling
Only if the treating clinician permits cycling, pedal loading and the movement range. Cycling is not equivalent to complete offloading.
Use a stationary bike suited to your height; the physiotherapist adjusts the seat and supports for the permitted movement.
Pedal seated and slowly with minimal resistance; do not force a complete revolution if motion is still insufficient.
Do not stand on the pedals, sprint or increase duration and resistance together. Stop for joint pain or subsequent swelling.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
4. Impact and sport
After a favourable review
Goals
Gradually resume the required activity.
Physiotherapy plan
Only after favourable lesion review and impact clearance: alternate walking and straight running; after running is tolerated, add small hops with controlled landings.
After landings without deep pain or later swelling, progress to deceleration, direction changes and sport-specific training.
Precautions
Stop progression for deep pain, locking or swelling.
Criteria the treating team checks at the end of the pathway
Full training tolerated, including afterwards.
Return agreed with clinician and physiotherapist.
Illustrated exercise options
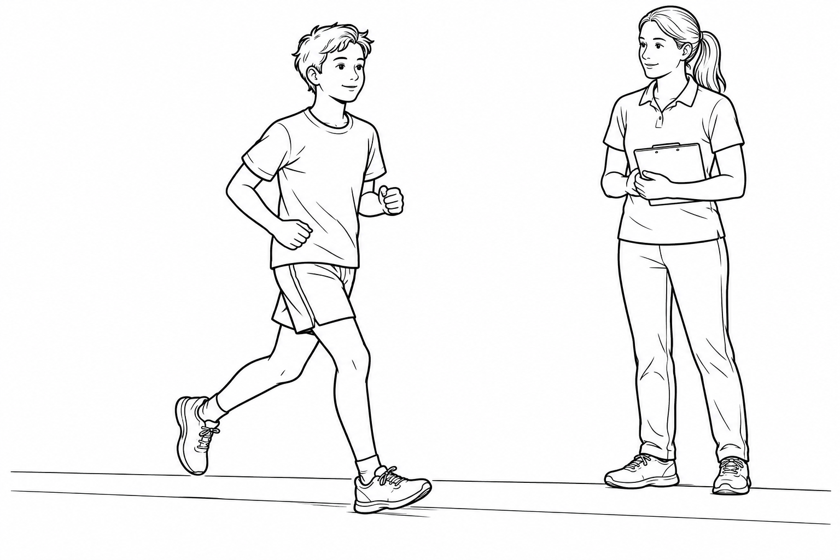
Straight-line walk–run progression
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
On level, even ground, alternate walking with short bouts of easy straight-line jogging according to the physiotherapist’s programme.
Keep an even gait without limping. Begin without sprinting, hills, jumping or direction changes.
Increase one demand at a time. If joint pain, limping or swelling occurs during the work or the next day, stop the progression and report it to the physiotherapist.
Dose and progression: Run/walk intervals, duration and recovery set by the physiotherapist for the procedure, age and response to loading; the phase does not provide an automatic dose.
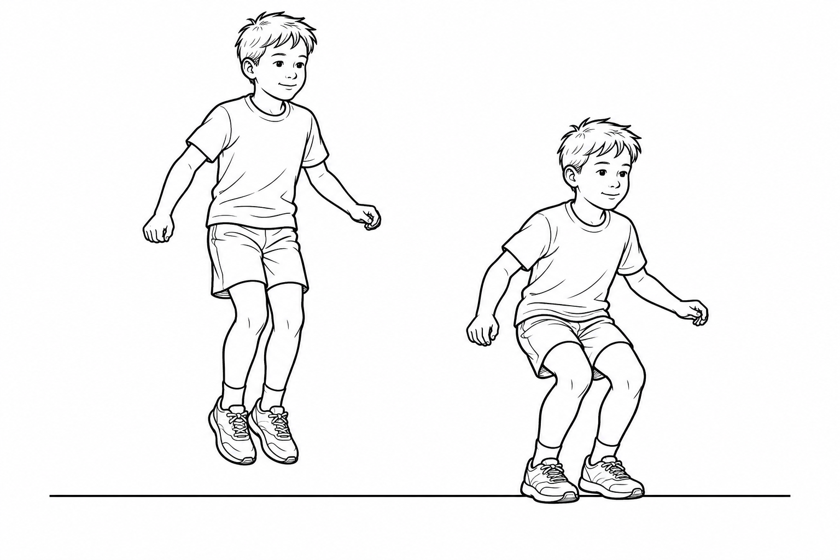
Small two-foot forward hops
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
With the physiotherapist, make one small two-foot forward hop on a firm, even surface, as illustrated.
Land on both feet with control and pause before repeating. The physiotherapist selects distance and number of hops; no sideways or single-leg hops without further instruction.
Stop for pain or loss of control and report pain or swelling afterwards.
Dose and progression: Initial attempts and dose selected by the physiotherapist; increase only after checking the subsequent response.
Planned braking and direction changes
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
With the physiotherapist, begin with controlled slowing and wide turns at low speed in agreed directions.
Control the trunk, knee and foot. Increase speed and turning angle separately; sharp, reactive or contact movements require further assessment.
Stop for pain, giving way or limping; also report swelling or pain after the session and the next day.
Dose and progression: Intervals, rests and recovery days selected for age, sport and previous level. No independent maximal tests; tolerate full training before competition.
Return to sport / full activity
Return follows lesion and functional assessment; no single threshold applies to everyone.
Lesion reassessed by the treating clinician, with imaging when indicated.
Document motion, quality and number of calf raises and single-leg stance control; compare across reviews without universal cutoffs.
Running and training without subsequent deep pain or swelling.
Warning signs: stop and contact the treating team
Joint locking, painful catching or new giving way: stop exercising and arrange reassessment.
Rest pain, recurrent swelling or new walking difficulty: stop progression and contact the treating clinician.
A very painful, hot, swollen joint, especially with fever or feeling unwell: urgent assessment, even without fever.
A cold, pale or numb foot under a cast/brace: go to emergency care immediately.
Guidelines and literature
Sources inform the pathway; they do not validate every dose for an individual child.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
Select the exact phase assigned by the treating team, then choose each prescribed activity. No exercise is selected automatically. The team sets loading, movement, aids, dose and frequency; missing instructions must be completed before use, including by hand.
Browse illustrated exercise options
Only for toes left free and if allowed; keep the cast or brace as prescribed.
Only after clearance for motion and brace removal for this exercise.
Only when some foot contact is permitted. The figure does not show a fully non-weight-bearing pattern: if contact is prohibited, you need specific instruction.
Only after clearance for resisted eversion and demonstration by the physiotherapist.
When ankle strengthening and resisted dorsiflexion are permitted; have the physiotherapist check the band setup.
Only after clearance for full weight bearing and calf strengthening.
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
Only if the treating clinician permits cycling, pedal loading and the movement range. Cycling is not equivalent to complete offloading.
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
Choose the current phase to prepare a printable sheet.
Phase safety summary ·
COMPLETE BEFORE EXERCISING — The treating team must complete the blank instructions, including handwritten entries, before this sheet is used.
Follow the assigned phase and instructions confirmed by the treating team; filling in fields does not authorise exercise.
No exercises assigned. This is a safety summary, not a complete exercise prescription.
Individual instructions for this phase
Loading (how much weight on the leg): ________________________________
Brace and crutches: ________________________________
Procedure and starting conditions
Record first: Lesion stability/site, weight bearing, any cast or brace, permitted motion and review date.
Progression: Loading, motion and impact require separate clearance. Do not remove immobilisation to follow an illustration. Functional checks are a practical checklist adapted from the sources, not validated paediatric return-to-sport tests.
Advice before starting
Perform only the exercises selected for you, at the prescribed dose. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Do not try running or hopping to check whether you have healed.
Report pain or swelling that develops after the session too.
Warning signs: stop and contact the treating team
Joint locking, painful catching or new giving way: stop exercising and arrange reassessment.
Rest pain, recurrent swelling or new walking difficulty: stop progression and contact the treating clinician.
A very painful, hot, swollen joint, especially with fever or feeling unwell: urgent assessment, even without fever.
A cold, pale or numb foot under a cast/brace: go to emergency care immediately.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
💬
💙
Any questions?
For information or questions, email me or view the locations and contact details.