Anterior Cruciate Ligament (ACL) Reconstruction
Five-phase pathway after ACL reconstruction in the skeletally mature patient: from early post-operative recovery to return to team, with objective criteria between phases.
Return to pivoting sport: not before 9 months, typically 9-12 months
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Changing phase restores its full exercise list. Timing alone does not determine the phase.
Exclude exercises if needed
19 of 19 exercise cards included
The full web page remains available. Your selection is not saved or shared.
This protocol is part of the post-operative pathway and must be adapted to the surgeon’s instructions and to the individual clinical response.
These documents are protocol templates for information and education only: they do not replace the rehabilitation prescription for the individual case. Timing, loading and progressions must always be adapted to the patient, the lesion pattern, the surgical technique used and the clinical course, in collaboration between orthopaedic surgeon, physiotherapist and, where appropriate, physiatrist. Progression is driven by objective criteria, not by the calendar alone.
At a glance — the full pathway
- Weight bearing
- Progressive weight bearing as tolerated from day one, unless the surgeon indicates otherwise (associated lesions, specific fixation).
- Brace
- Not routinely required; when prescribed, usually locked in extension for walking in the first weeks.
- ROM
- Full extension (0°) is the absolute priority; 90° flexion within 2 weeks, 125°+ within 6-8 weeks.
- Straight-line running
- Not before month 3, and only with full ROM, no effusion and quadriceps strength ≥70-80% of the contralateral side.
- Daily activities
- Sedentary work after 7-10 days; driving at 30-45 days; swimming and showering after wound healing (15-20 days).
- Return to sport
- Pivoting sport not before 9 months, with the full test battery passed (LSI ≥90%).
The anterior cruciate ligament prevents anterior translation of the tibia on the femur and controls rotation. After reconstruction, the graft undergoes a biological process of integration and revascularisation that takes time and cannot be accelerated: rehabilitation supports it, it does not force it.
Step by step
Each phase offers exercise options: perform only those selected by your clinician, without bringing later phases forward or automatically adding earlier exercises. Dosage, frequency and rests are individualised; the complete catalogue is not a single session.
Before surgery — Preoperative preparation (prehabilitation)
Indicatively 2-6 weeks before surgery, when the knee allows it: duration and need depend on the clinical picture, there is no mandatory minimum.
When it applies
- •When the clinical picture and surgical timing allow, the preoperative phase is an integral part of the pathway, not a side note.
- •It is particularly useful with a still swollen or stiff knee, an extension deficit or quadriceps inhibition after the injury.
- •It is carried out with the physiotherapist, with an agreed daily home programme.
Goals before surgery
- •Full extension, or symmetrical to the uninjured knee.
- •Near-full flexion.
- •Minimal effusion (a "dry" knee).
- •Walking without significant limp, ideally without crutches.
- •Good voluntary quadriceps control and activation, with no extension lag.
- •Strength recovery compatible with the clinical picture of the injured limb.
- •Education on brace, crutches, allowed weight bearing and the early post-operative phases.
Activities
- •Effusion and pain control (ice, elevation, load management).
- •Practical education on brace, crutches, allowed weight bearing and the goals of the first weeks.
- •Daily home programme, alongside physiotherapy sessions.
Preoperative exercises
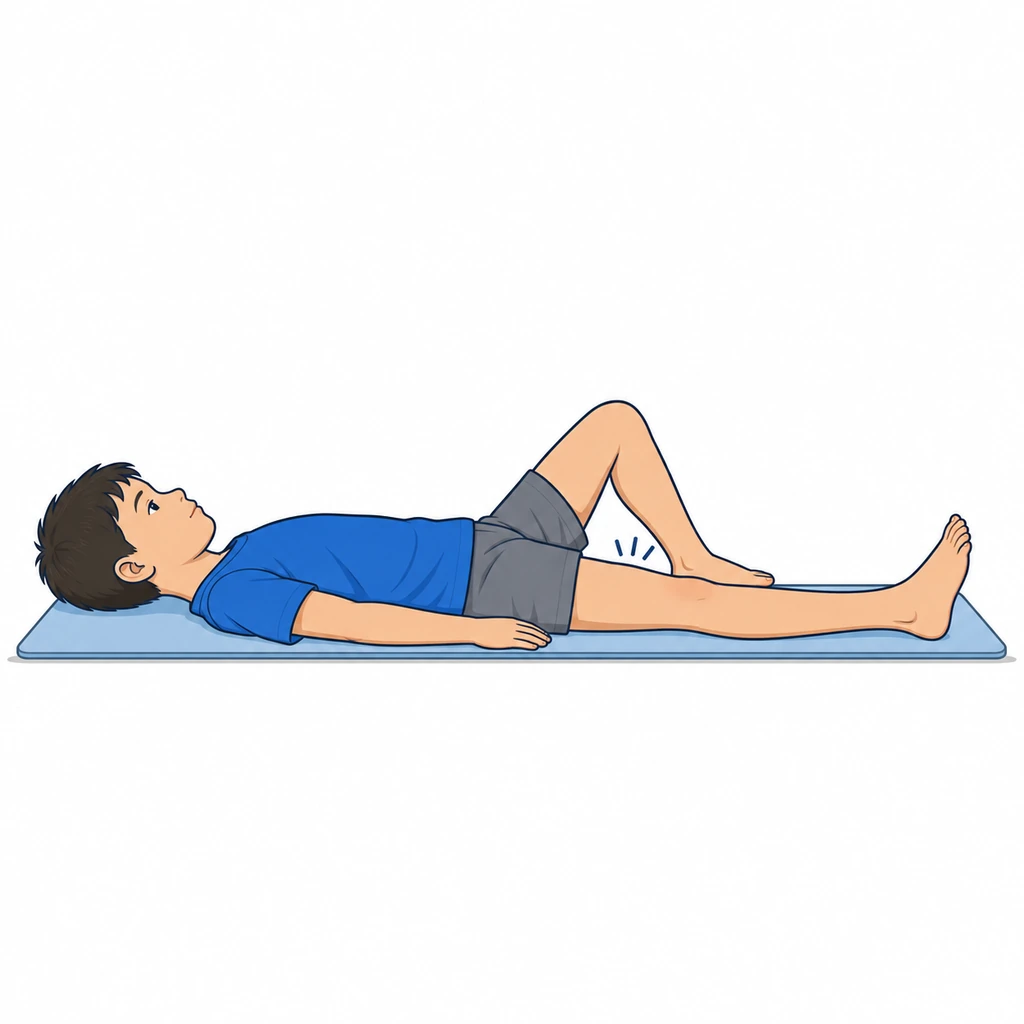
Quadriceps isometric contraction (quad set)
- •Lying down, knee straight in a neutral position on the surface; if proprioceptive feedback helps, place a small rolled towel under the knee.
- •Contract the quadriceps pushing the back of the knee toward the surface, hold, then release slowly.
- •Aim for a visible, global quadriceps contraction, without breath holding.
Dosage: Indicative: 10 contractions of 5 seconds, 2-3 times a day. To be adapted with the physiotherapist.
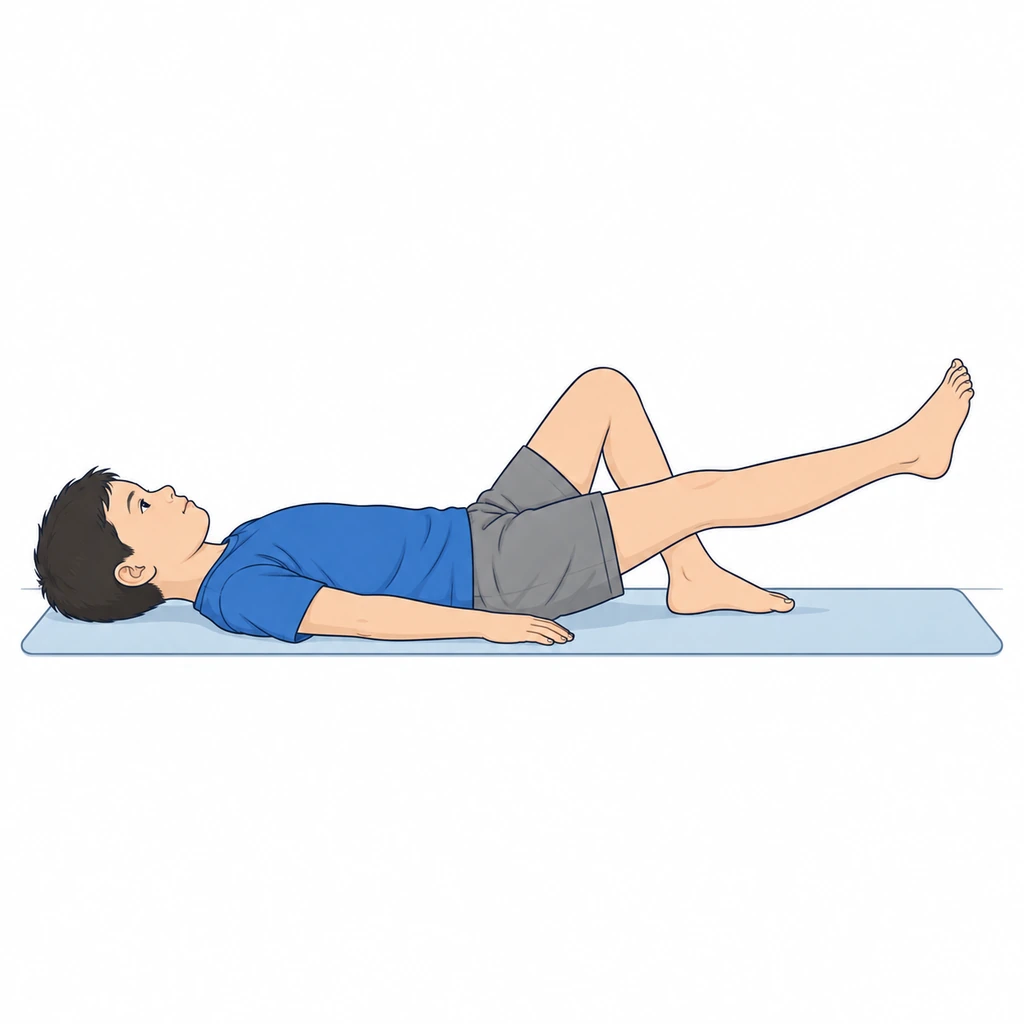
Straight leg raise (only if there is no extension lag)
- •First contract the quadriceps and lock the knee in full extension.
- •Lift the straight leg about 30 cm keeping the knee straight, then lower it slowly.
- •If the knee drops into flexion during the lift (extension lag), stop and work on quad sets first.
Dosage: Indicative: 2-3 sets of 8-10 repetitions. To be adapted with the physiotherapist.
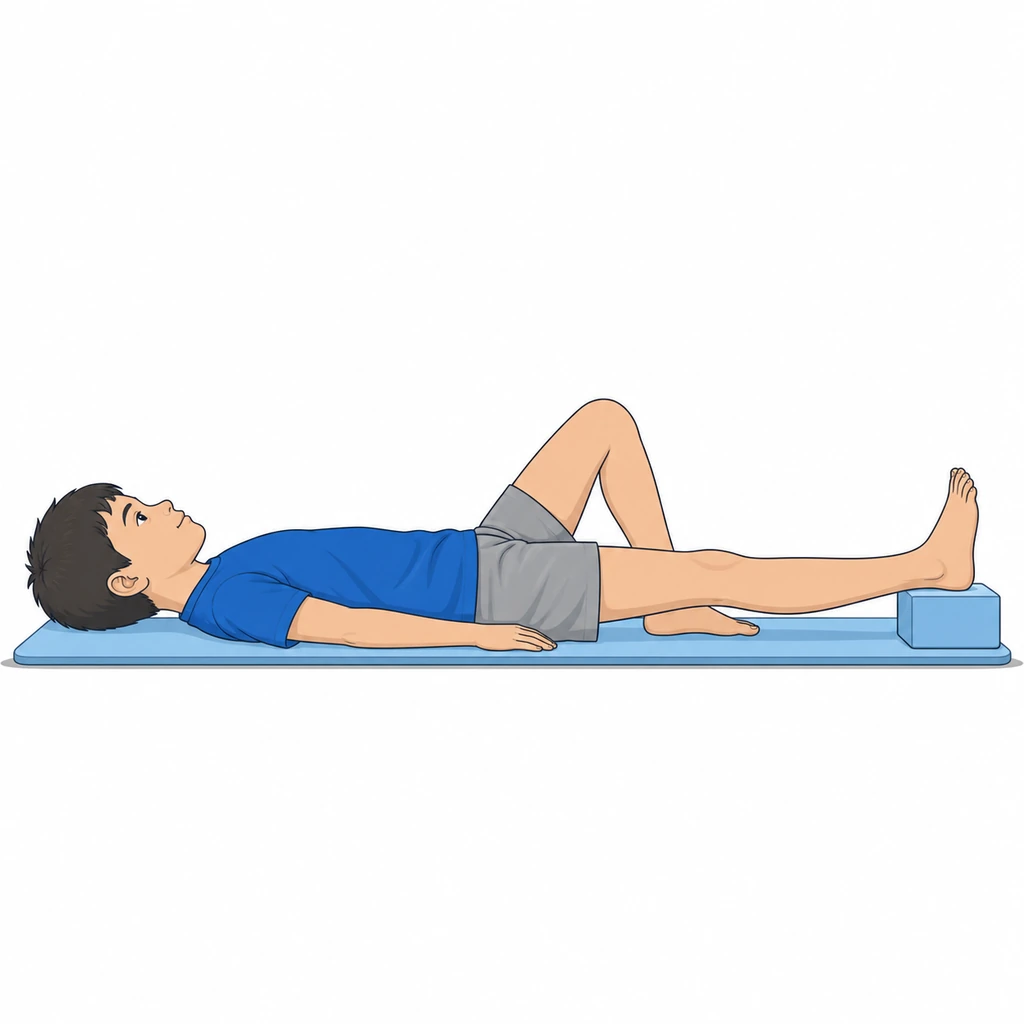
Extension recovery with the heel supported
- •Lying down, rest only the heel on a low support leaving the knee unsupported.
- •Let the knee drop under gravity with the thigh relaxed; a gentle quadriceps contraction can be added.
- •Do not force and do not push abruptly on the knee: extension returns with time and relaxation.
Dosage: Indicative: 3-5 minutes, several times a day if well tolerated.
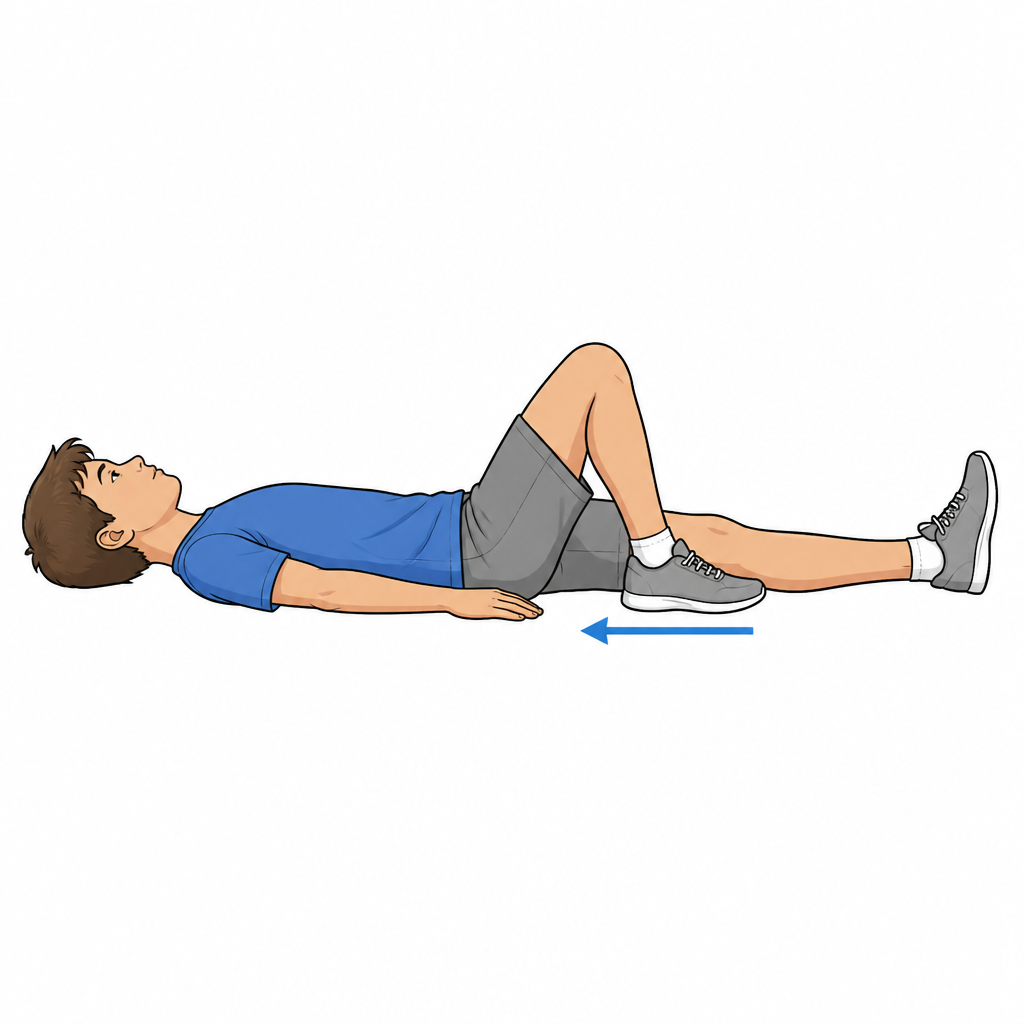
Heel slides / active-assisted flexion
- •Lying down, slide the heel toward the buttock keeping the foot in contact with the surface.
- •You may assist with your hands or a towel around the leg, staying within the pain-free range.
- •Return slowly to the start position, regaining full extension.
Dosage: Indicative: 10-15 repetitions, 2-3 times a day.
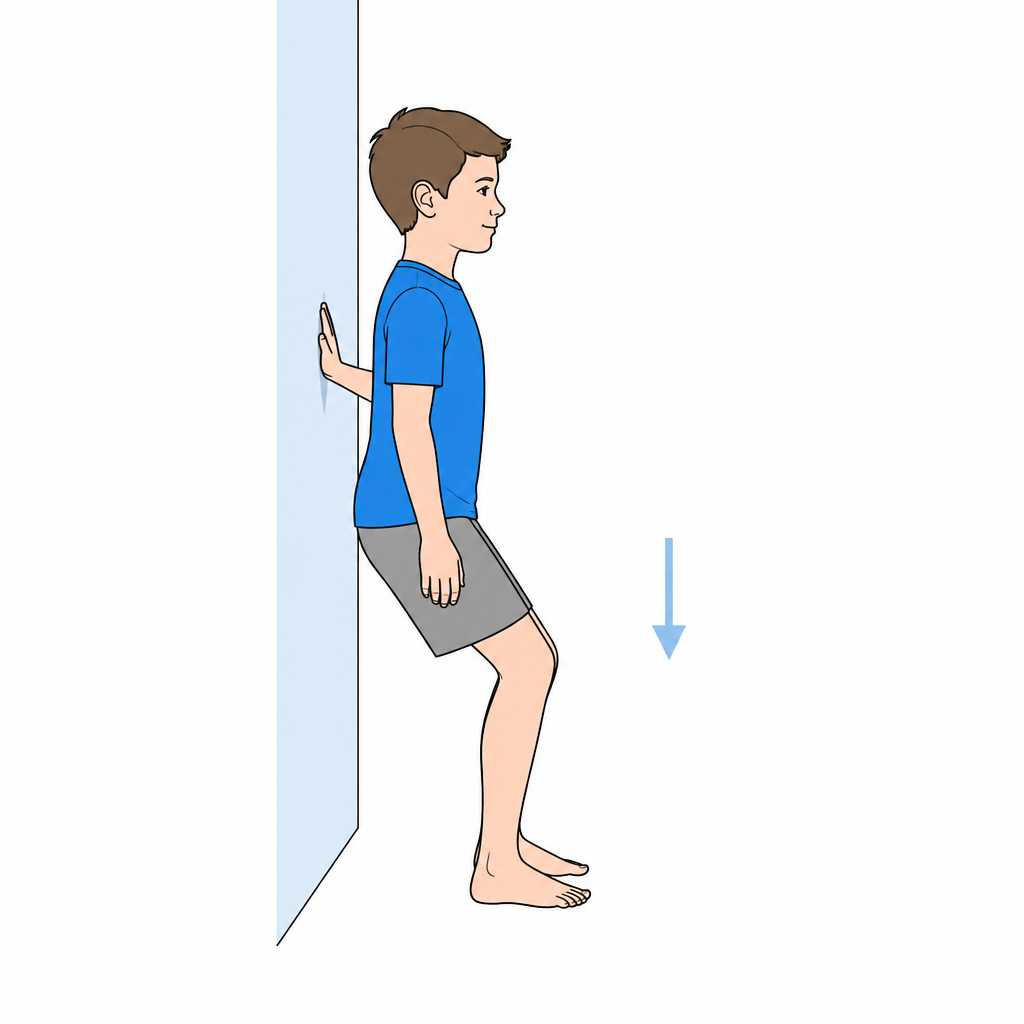
Mini squat or sit-to-stand within the tolerated range
- •Standing, bend the knees only within the pain-free range (usually within 45-60°), keeping the knee aligned over the foot.
- •Alternatively, stand up and sit down from a comfortable chair height, sharing weight between both legs.
- •Avoid knee valgus collapse and trunk twisting.
Dosage: Indicative: 2-3 sets of 8-12 repetitions, on alternate days or as advised.
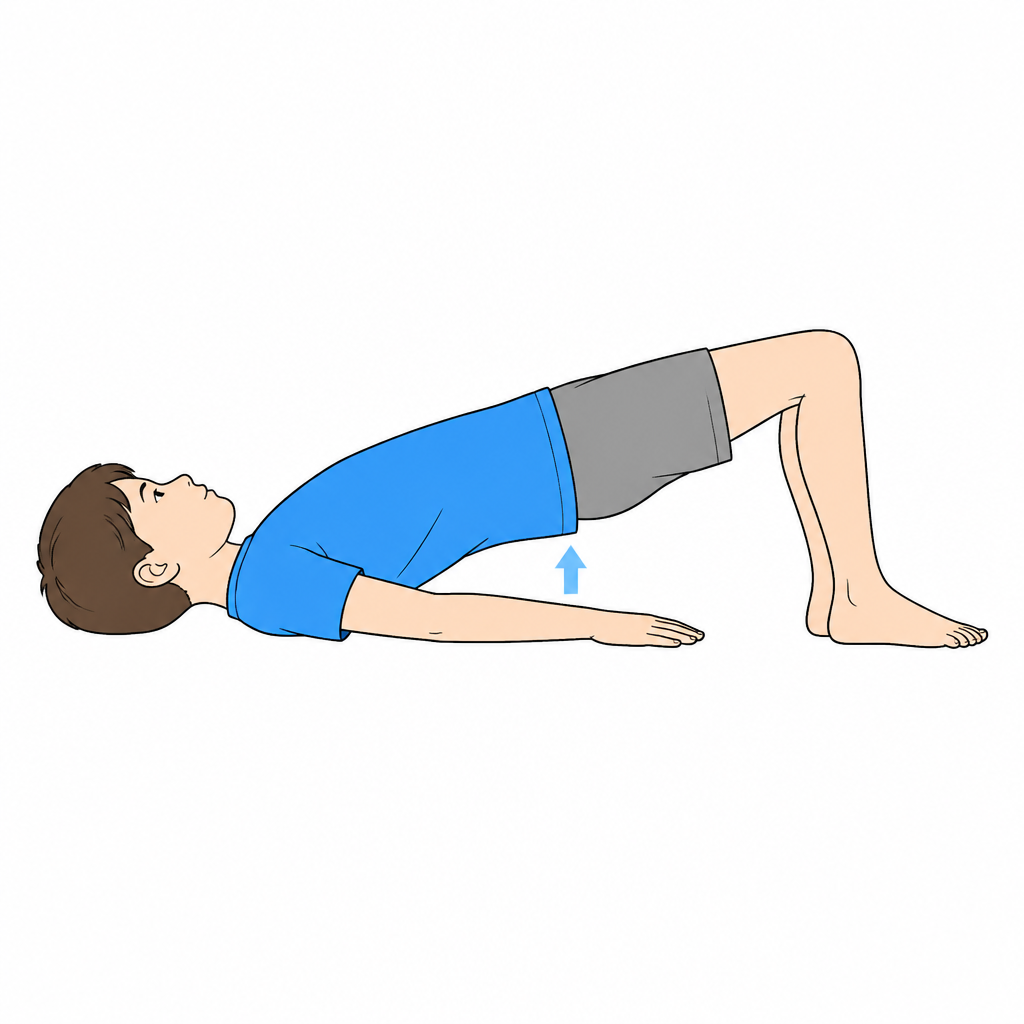
Bridge
- •Supine, knees bent and feet hip-width apart on the floor.
- •Lift the pelvis squeezing the glutes, without arching the back, then lower slowly.
Dosage: Indicative: 2-3 sets of 10-12 repetitions.
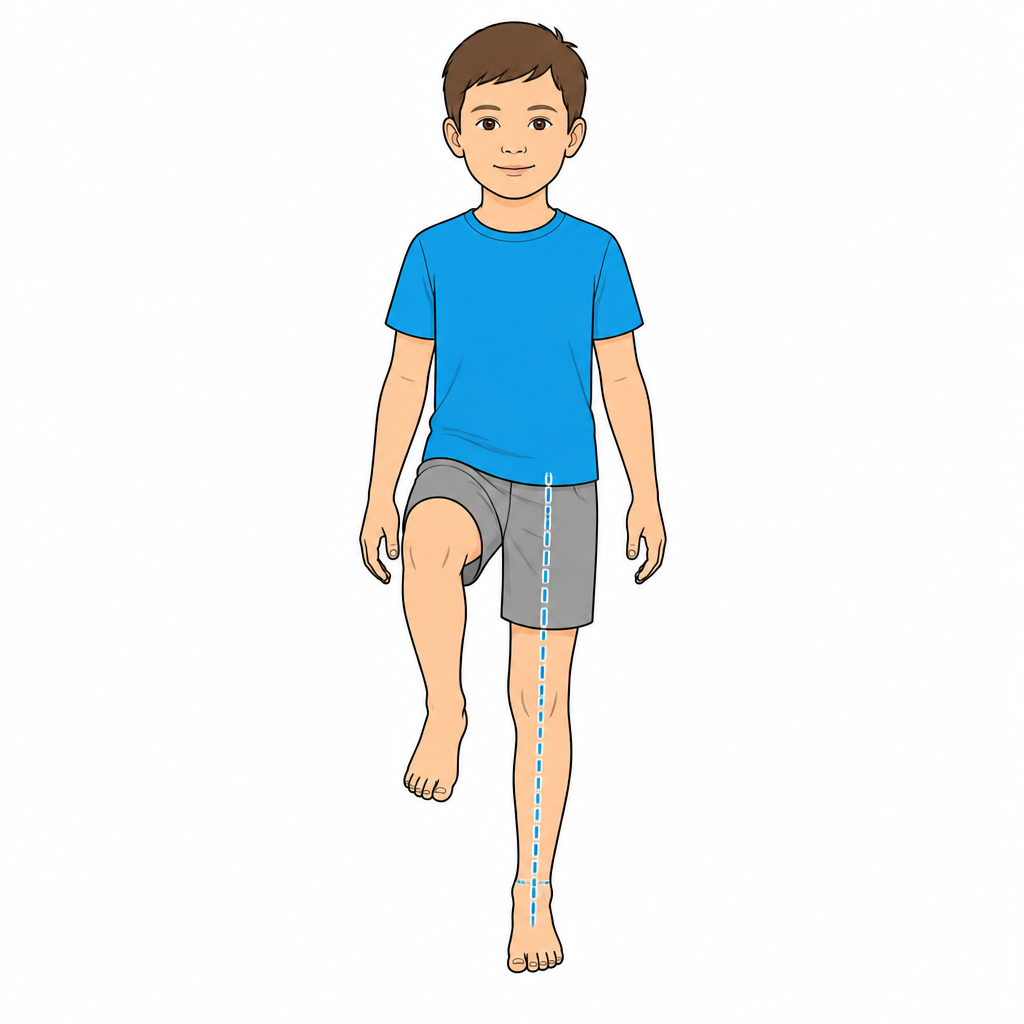
Single-leg balance (only if safe)
- •Standing near a support, load one leg keeping the knee slightly flexed and the pelvis level.
- •Stop if pain, giving-way sensation or instability appear.
Dosage: Indicative: 3-5 holds of 20-30 seconds per side.
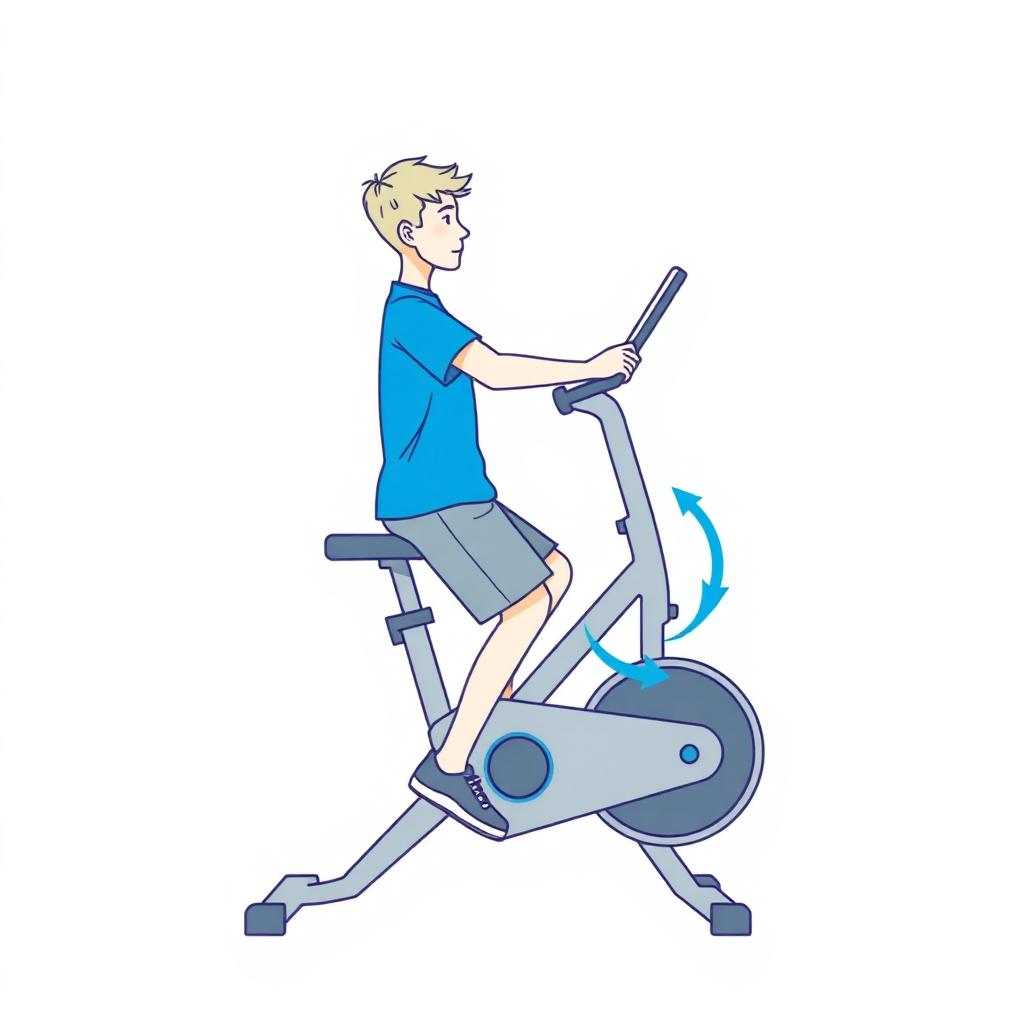
Stationary bike
- •To be introduced when range of motion and pain allow: raise the saddle if flexion is still limited.
- •Continuous pedalling at low resistance, pain-free and without increased swelling in the following hours.
Dosage: Indicative: 10-20 minutes, as tolerated.
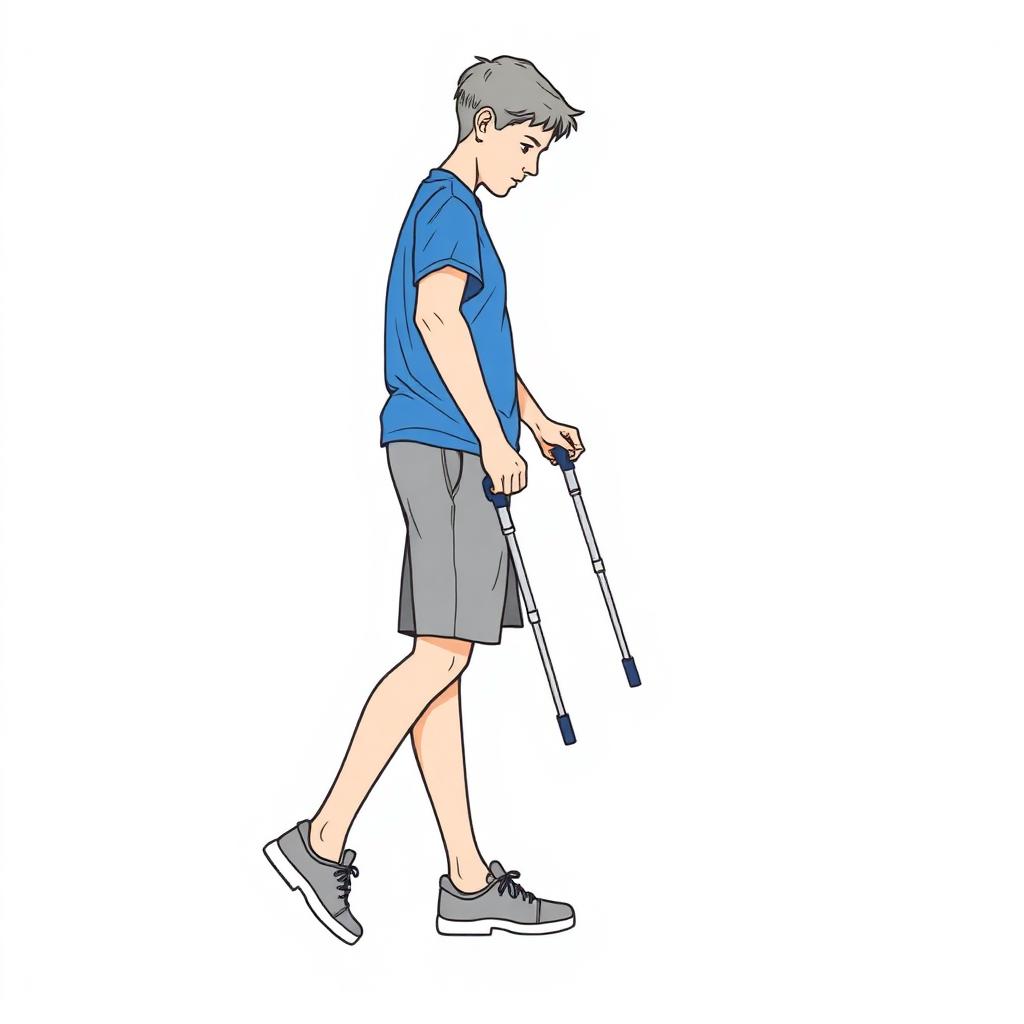
Crutch and weight-bearing training
- •Try the crutches before surgery, with correct height and the weight-bearing status set by the surgeon.
- •Practise on level ground, stairs and the entrance to your home, with someone assisting.
- •Also practise sitting, standing and moving in the bathroom while respecting the planned loading restrictions.
Dosage: At least one training session before admission; repeat until the technique is safe.
Readiness criteria for surgery
- ☐Full or symmetrical extension and near-full flexion.
- ☐A dry knee, or a stable minimal effusion.
- ☐Smooth gait, without antalgic limp.
- ☐Effective quadriceps contraction, with no extension lag on straight leg raise.
- ☐The young patient and family can use crutches and brace and understand the first post-operative weeks.
When surgery must not be delayed
- •Locked knee or bucket-handle meniscal tear: surgery should not be postponed to complete weeks of prehabilitation.
- •Associated lesions needing timely treatment (repairable chondral or osteochondral lesions, multiligament injuries, fractures).
- •Repeated giving-way episodes: not an automatic indication, but they may make it appropriate to bring forward the surgical decision, especially if they limit daily life or expose the knee to new meniscal or chondral injuries.
What to prepare at home and school
- •Organise movement at home: clear pathways, remove rugs, keep useful items within reach.
- •Prepare ice, a support for the heel, comfortable clothing and crutches already adjusted.
- •Inform school or the sports club: plan the absence, temporary exemption and gradual return.
- •Agree the first post-operative physiotherapy session in advance.
Preoperative preparation may improve pre-surgical strength and function and support early recovery after reconstruction. It is not a guarantee of the final outcome: the post-operative pathway remains decisive. Dosages and duration are indicative and must be adapted by the physiotherapist.
Phase 1 — Early post-operative recovery
Indicative timing: Weeks 0-2
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Achieve and maintain full knee extension
- •Reduce and control joint effusion
- •Restore voluntary quadriceps activation
What to do
- •Quadriceps isometrics in full extension, straight leg raise without extension lag
- •Patellar mobilisations, cryotherapy and compression, elevation
- •Correct gait with two crutches, progressive weight bearing as tolerated
- •Active-assisted flexion up to 90°, ankle mobility
Restrictions and precautions
- •Do not force flexion beyond 90° in this phase
- •Avoid prolonged standing and direct skin contact with ice
- •Keep the wound dry for 15-20 days
Exercises for this phase
1. Quadriceps isometric contraction (quad set)After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lie on your back with the leg supported and the knee within the authorised extension range.
- •Tighten the front of the thigh without lifting the leg or forcing the knee. Use a small support under the knee only if demonstrated by your physiotherapist.
- •Hold briefly and relax. Lifting the heel is neither a target nor proof of full extension.
Dosage: 10 contractions of 5 seconds, 4-6 times a day
2. Straight-leg raiseAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lying on your back, first tighten the thigh until the knee locks straight.
- •Lift the straight leg about 30 cm, hold 3 seconds and lower slowly.
- •If the knee bends while lifting, the quadriceps is not ready yet: go back to quad sets.
Dosage: 3 sets of 10, twice a day
Ready for the next phase when
- ☐Passive extension 0°, passive flexion 90°
- ☐Mild to moderate effusion in the anterior/medial compartment
- ☐Ability to hold the knee extended against gravity (no extension lag)
Note for the physiotherapist
Early full extension is the single strongest predictor of good functional outcome: regain it now, not later. Quadriceps control (quad set without lag) precedes any loading progression.
Phase 2 — Strength and neuromuscular control
Indicative timing: Weeks 2-12
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Regain single-leg balance
- •Restore thigh and posterior chain strength
- •Restore full range of motion
What to do
- •Straight leg raise in 4 directions, hamstring stretching, patellar mobilisations
- •Closed kinetic chain: isometric mini-squat, protected-range leg press, progression bilateral squat → goblet → split squat → lunge → step down → single leg squat
- •Leg curl for hamstrings, calf strengthening, ankle mobility work
- •Proprioception (wobble board, unstable surfaces), slow cycling with high saddle, walking in water
Restrictions and precautions
- •Progress only if the knee stays dry and pain-free over the following 24 hours
- •Caution with open kinetic chain in the 0-30° arc in the early weeks
Exercises for this phase
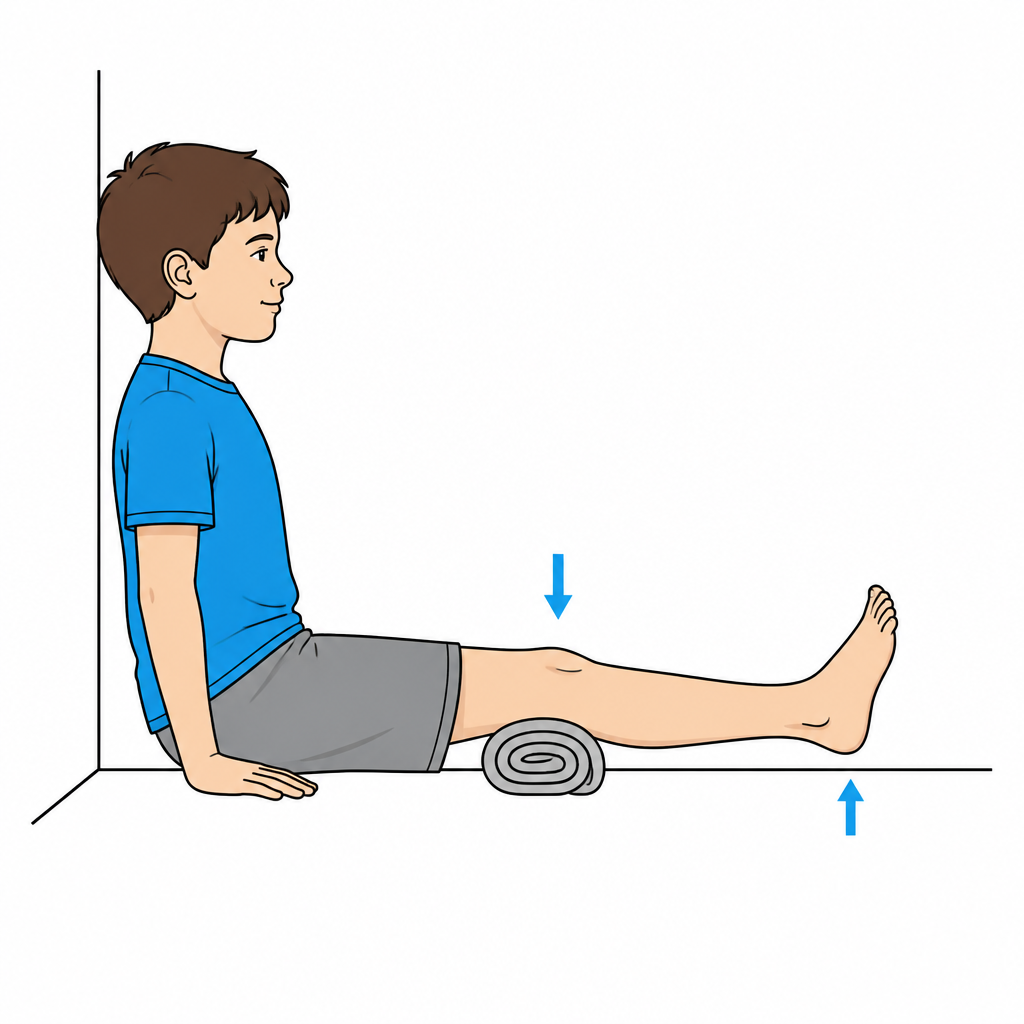
3. Global quadriceps recoveryAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sitting with a pillow under the slightly bent knee.
- •Extend the knee by pushing the heel forward, keeping the thigh on the pillow.
- •Aim for a full, even contraction of the whole thigh: isolating a single portion of the muscle is not useful.
Dosage: 3 sets of 12, once or twice a day
4. Mini-squat 0-45°After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Standing, feet hip-width apart, weight evenly distributed.
- •Bend the knees to about 45°, keeping the knees aligned over the feet.
- •Rise by pushing through the heels, without letting the knee collapse inwards.
Dosage: 3 sets of 12, 3-4 times a week
5. Glute bridgeAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lie on your back, knees bent, feet flat on the floor.
- •Lift the pelvis by squeezing the glutes until shoulders, hip and knee are aligned.
- •Lower slowly without arching the back.
Dosage: 3 sets of 12-15, on alternate days
6. Single-leg balanceAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Stand on one leg with the knee slightly bent and look ahead, after clearance for weight bearing.
- •Keep your eyes open on firm ground near a stable support; an adult must be able to assist the child.
- •Aim to keep your pelvis steady. If it tilts or you lose balance, put the other foot down, reduce the difficulty and ask your physiotherapist to check the movement.
Dosage: 3 x 30 seconds per side, daily
Ready for the next phase when
- ☐Passive extension 0°, passive flexion 125°+
- ☐No effusion
- ☐Stable single-leg balance and single leg squat without dynamic valgus
- ☐Documented progression of quadriceps strength (dynamometry or comparative isometric testing); thigh circumference, if measured in a standardised way, is only a complementary datum
Note for the physiotherapist
Dynamic medial knee collapse can involve hip adduction and internal rotation, knee abduction and foot movement. Assess movement quality and control with the physiotherapist; 2D video alone does not certify an individual’s reinjury risk.
Phase 3 — Running, agility and jumping
Indicative timing: Months 3-6
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Excellent jump, landing and rebound control
- •Agility programme and cardiovascular reconditioning
- •Full recovery of leg and core strength
What to do
- •Slow straight-line running, then figure-of-8 with progressively tighter radius
- •Guided, progressive plyometrics: pool → trampoline → sand → grass → hard surface
- •Agility and deceleration drills with focus on landing technique
- •Continued gym strengthening and neuromuscular work
Restrictions and precautions
- •No contact, no pivoting in uncontrolled situations
- •Pay attention to surface type and footwear
Exercises for this phase
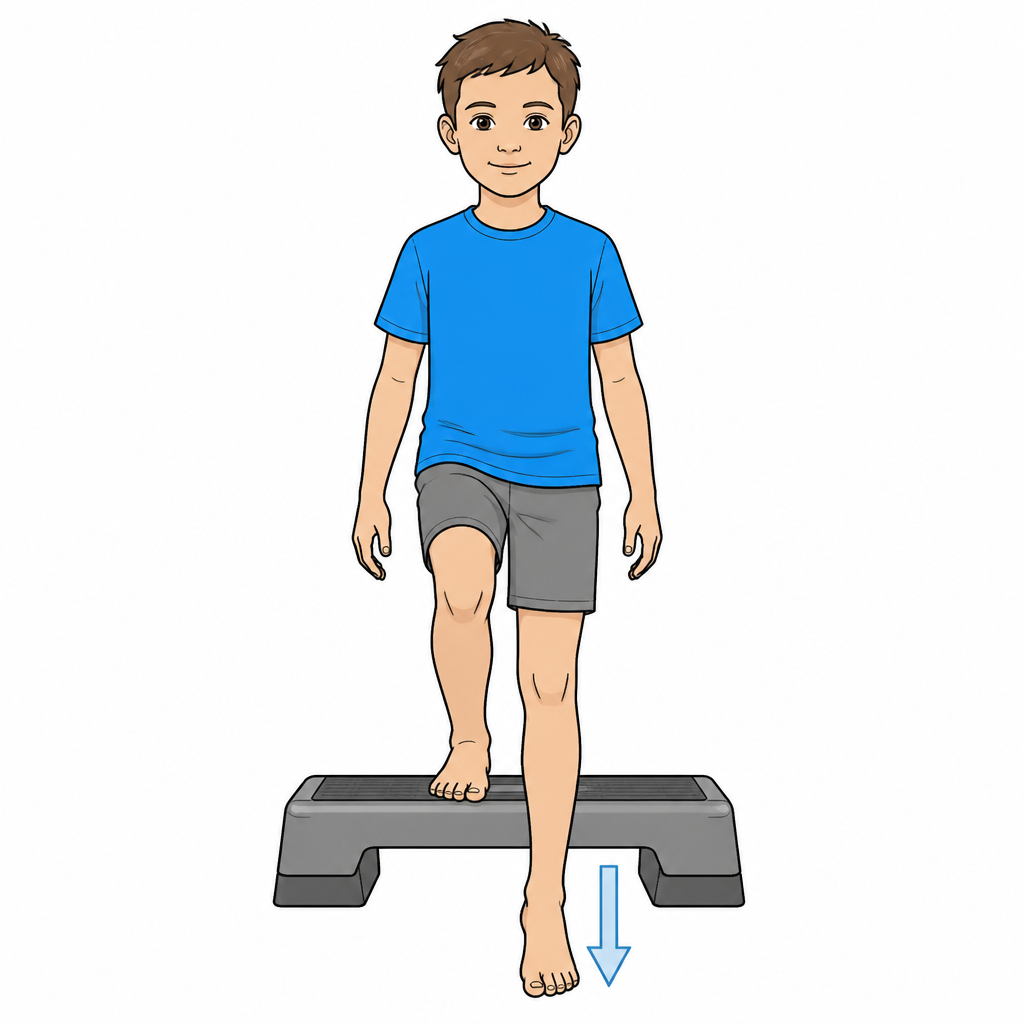
7. Controlled step-downAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Stand on a 15-20 cm step on the operated leg.
- •Lower slowly with the other foot, touching the floor with the heel, over 3 seconds.
- •The standing knee must stay aligned over the foot: if it collapses inwards, lower the step.
Dosage: 3 sets of 8-10 per side, 3 times a week

8. Low-impact conditioningAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Stationary bike with high saddle and minimal resistance, swimming (avoiding breaststroke early), elliptical.
- •Select cycling, pool exercise or other low-impact activity with your physiotherapist within the permitted load, range and resistance. Low impact does not mean no compression of the repaired area.
- •The rule is always the same: no swelling the next day.
Dosage: 20-30 minutes, 3-5 times a week
Ready for the next phase when
- ☐Confidence and correct landing technique, without dynamic valgus
- ☐Running and plyometrics tolerated without pain or effusion over 24-48 hours
- ☐Documented progression of quadriceps and hamstring strength; maximal hop testing belongs to the later sport-specific phases
Note for the physiotherapist
The keyword is technique: quality of deceleration and landing before volume and intensity. Isokinetic testing at the end of this phase documents the residual deficit.
Phase 4 — Return to team and sport
Indicative timing: From month 6-9
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Stable, solid knee with excellent neuromuscular control
- •Confident athlete ready to return
- •Recovery of sport-specific technical skills
What to do
- •Individualised programme supervised by a coach or physiotherapist experienced in injury recovery
- •Progressive simulation of sport-specific gestures (shooting, serving, ball skills)
- •Partial team training, then full training before match play
- •Isokinetic test before the outpatient review (around 6-7 months), brought to the appointment
Restrictions and precautions
- •No competitive match play before the full test battery is passed and 9 months have elapsed
Exercises for this phase
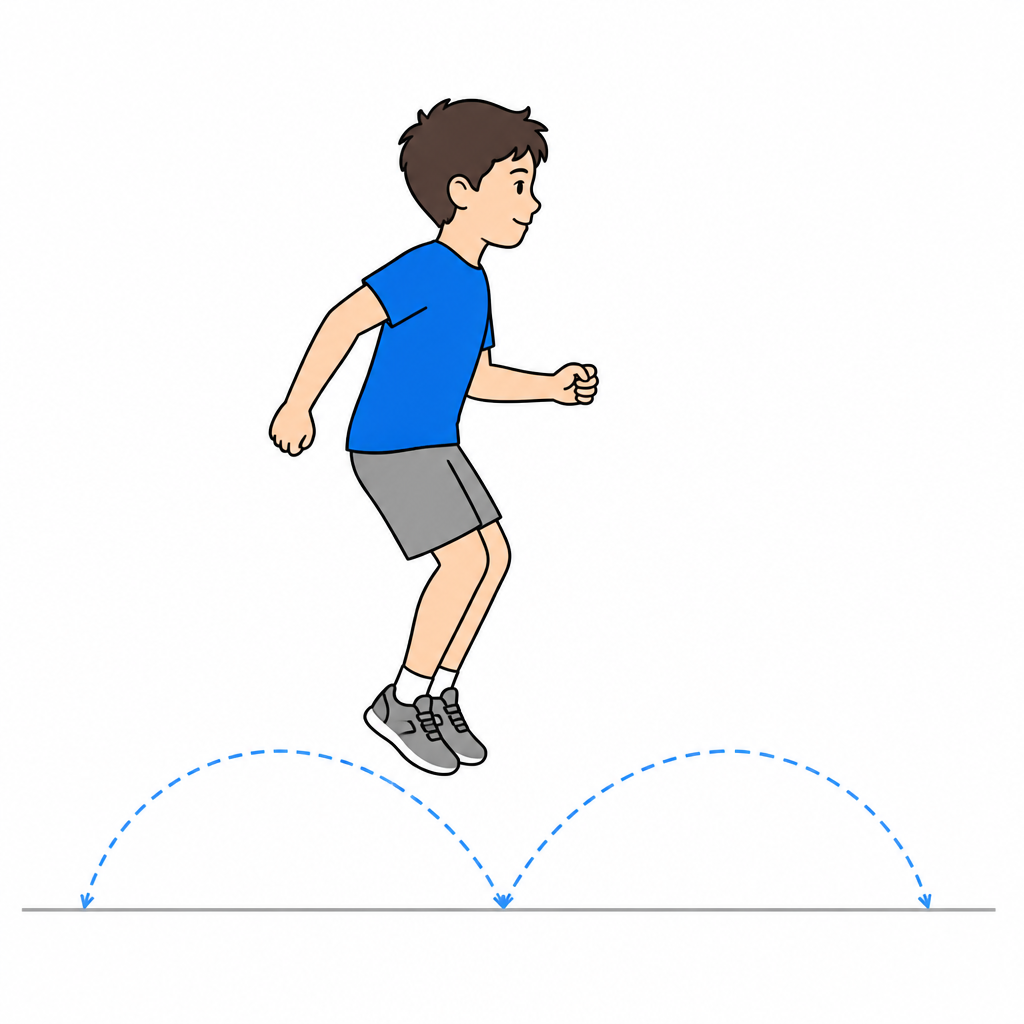
9. Progressive plyometricsAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Only after clearance for impact and demonstration by your physiotherapist, start with small two-foot hops on a stable surface.
- •Increase direction, height or single-leg work only within the agreed progression; do not add several challenges at once.
- •Aim for a controlled landing with knees and feet aligned. Stop for pain, giving way or loss of control; report swelling or worsening symptoms afterwards. Landing noise alone does not measure movement safety.
Dosage: 2-3 sets of 10-20 contacts, 2-3 times a week
Ready for the next phase when
- ☐Isokinetic muscle deficit no greater than 10% versus the healthy side
- ☐4 hop test battery with LSI ≥90% (reference value, not binding on its own)
- ☐IKDC ≥90 and adequate psychological readiness to return (also assessed with ACL-RSI, read as a trend over time rather than a mandatory threshold)
- ☐Full team training without symptoms
Note for the physiotherapist
Clearance is multifactorial: clinical assessment + scores (IKDC, ACL-RSI, Melbourne ACL RTS score) + functional tests. Low or worsening psychological readiness is associated with failure to return and with re-injury even when strength has recovered: interpret it in context and over time, not as a single cut-off.
Phase 5 — Re-injury prevention
Indicative timing: Ongoing, at least a 6-week structured programme
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Improve neuromuscular control in running, sprinting, cutting and jumping
- •Maintain balance between muscle groups
- •Make the programme part of the training routine
What to do
- •FIFA 11+ programme (adult or kids version) built into the team warm-up
- •Balance, endurance and strength work several times a week
- •Education of athlete, coach and strength coach
Exercises for this phase
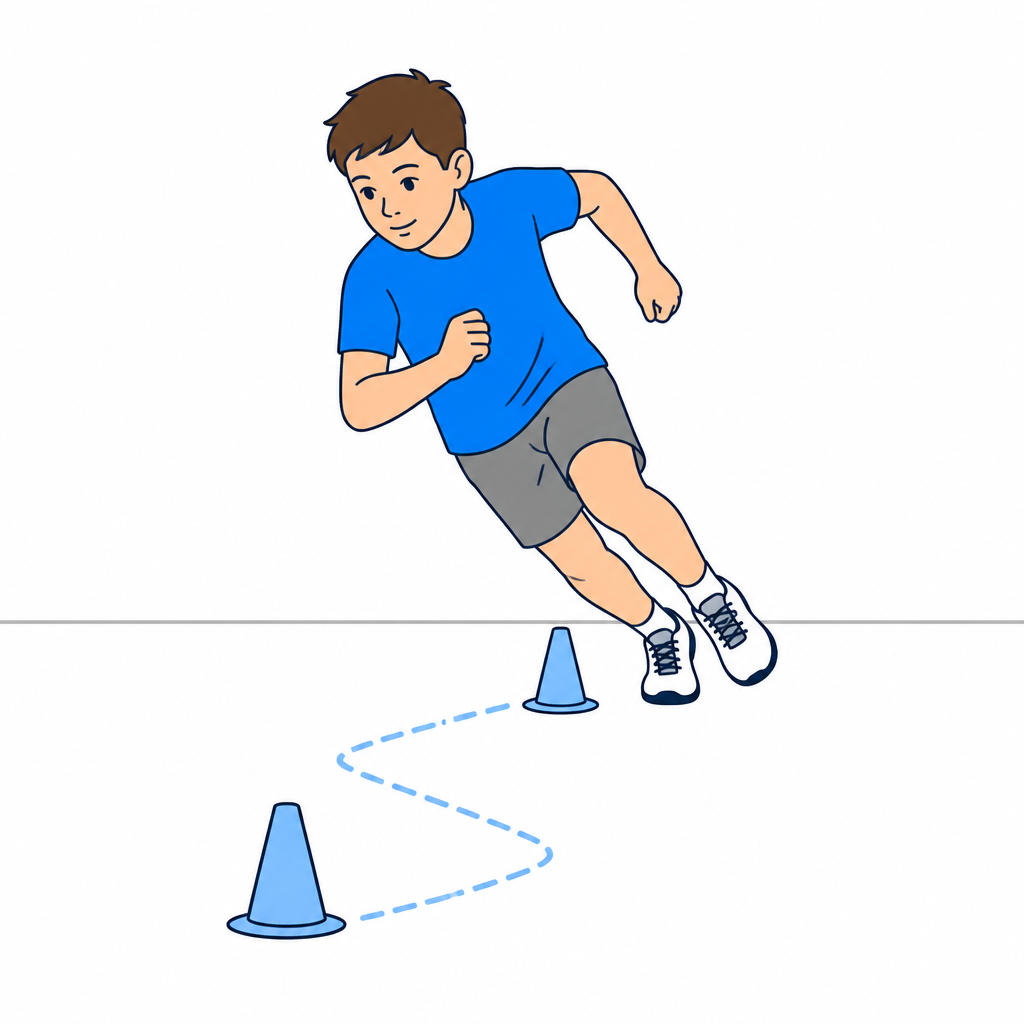
10. Agility and change of directionAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •After clearance, practise shuttle runs, figure-of-eight runs and cone slaloms: wide turns first, then sharper changes.
- •Add unanticipated direction changes only at the agreed stage, with the physiotherapist or trainer supervising the return to sport.
- •Stop for pain, the limb giving way or loss of movement control.
Dosage: 2 sessions a week, within training
Ready for the next phase when
- ☐Prevention programme performed consistently at least 2-3 times a week
- ☐No dynamic valgus at periodic checks
- ☐Strength symmetry maintained over time
Note for the physiotherapist
About 75% of ACL injuries occur without direct contact and a substantial proportion is preventable. Growing athletes and female athletes carry a clearly higher risk for the same activity.
If symptoms appear after a progression
If persistent pain, effusion or swelling, or loss of movement appears after moving to a new phase or increasing load, stop progression and contact the treating clinician or physiotherapist to review the programme. Seek prompt assessment for the red flags below. This document does not replace individual clinical assessment.
Return to sport / full activity
Pivoting and contact sport: not before 9 months post-op, typically 9-12 months.
- ☐4 hop test battery (single, triple, crossover, 6 m timed) with LSI ≥90%
- ☐Isokinetic quadriceps and hamstring strength with LSI ≥90% (deficit ≤10%)
- ☐Subjective IKDC ≥90
- ☐Adequate psychological readiness to return, assessed clinically and over time (ACL-RSI may be used as a reference, not as a binding cut-off)
- ☐No effusion, full and symmetrical ROM
- ☐Full team training without symptoms for at least 2-4 weeks
In published cohorts, each month of delay up to month 9 is associated with a lower re-injury risk: this is an observed association, not an individual guarantee. In patients under 20-25 years the risk of graft or contralateral rupture remains high: continuing the prevention programme after return is an integral part of the protocol. The Limb Symmetry Index has known limitations: on its own it is not sufficient, because the uninjured side may also be deconditioned; it should be combined with absolute strength values, movement quality and sport-specific demands.
Red flags: stop and contact us
- •Effusion that returns or increases after sessions: a sign of overload, reduce load and reassess
- •Loss of full extension or new extension lag
- •Joint locking or painful catching (suspected associated meniscal tear or cyclops lesion)
- •Persistent and worsening anterior knee pain
- •Subjective giving way or instability
- •Fever, redness, warmth or wound discharge (suspected infection: contact us immediately)
- •Calf pain with asymmetric swelling (suspected deep vein thrombosis: urgent assessment)
Author: Dott. Daniele Priano, Paediatric Orthopaedics. Content version: 9 September 2026.
Timings are indicative: progression depends on clinical and functional criteria and on the treating clinician’s instructions.
Full introduction and references at ortopediaevolutiva.com/en/rehabilitation/acl-reconstruction
Anterior Cruciate Ligament (ACL) Reconstruction — Dott. Daniele Priano, Pediatric Orthopaedics · Information document: it does not replace an in-person assessment.
 Latest online version
This protocol may be used and shared for clinical and informational purposes provided that attribution to the author and to the original source is kept intact. Republishing or distributing it as one’s own work is not allowed.
Other protocols

Any questions?
For information or questions, email me or view the locations and contact details.
Email: daniele.priano@ortopediaevolutiva.com