Pathway for an uncomplicated lateral ankle sprain: progressive loading, strength, balance and return to sport.
Phases may overlap: progression depends on severity and function, not a single deadline.
For physiotherapists: adapt exercises, dosage and progression to the injury or procedure, protection, permitted loading and movement; check clinical criteria, not elapsed time alone.
Scope and before starting
For an uncomplicated lateral ankle sprain after assessment excluding fracture, syndesmotic injury and osteochondral injury. These conditions need separate pathways.
Before starting
Record diagnosis, weight-bearing ability, pain, swelling and any brace. After injury, inability to walk or bony pain needs medical assessment.
Loading and protection
Progress weight bearing as tolerated, using crutches when needed. Severe injuries may need brief immobilisation; do not prolong it independently.
Walk within tolerance using the recommended aids; do not force the ankle. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Perform a small selection of exercises and check the response afterwards too.
You need to complete training before returning to competition.
Treatment phases and illustrated exercises
Exercises are shown in their assigned starting phase, with their instructions and precautions. The physiotherapist selects them for the individual plan; the complete protocol is not a prescription to perform them all.
Respect the minimum times and protection required for the procedure. Time alone does not authorise progression: the treating team checks the clinical criteria.
1. Symptoms and walking
First days
Goals
Control pain and swelling; make gait safe.
Physiotherapy plan
Protection and crutches if useful, progressing loading as tolerated.
Gentle active up/down motion and light isometrics in tolerated directions without lateral pain; elevation and protected cooling if useful.
Precautions
Avoid painful inversion, forced manoeuvres and sport.
Criteria the treating team checks before progression
Loading and walking improving.
Pain and swelling stable or decreasing.
Illustrated exercise options
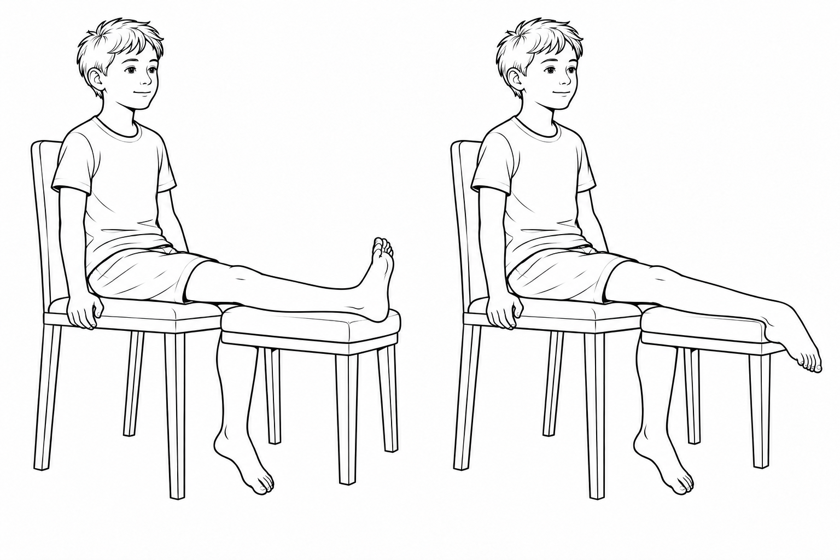
Unloaded ankle motion
Only after clearance for motion and brace removal for this exercise.
With the leg supported and foot free, slowly move the foot towards and away from you within the permitted range.
The figure shows the two directions, not the range to achieve. Do not use bands or manual pressure.
Stop for deep pain; do not add rotations unless authorised.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
2. Movement and strength
As gait improves
Goals
Restore mobility and basic strength.
Physiotherapy plan
Motion without forcing, then dynamic band strengthening in tolerated directions and calf raises once weight bearing is safe.
Firm-ground balance with support, then single-leg balance once gait is controlled.
Precautions
Do not add resisted inversion if it causes lateral pain.
Criteria the treating team checks before progression
Walking without a significant limp.
Weight-bearing exercises tolerated without increased swelling.
Illustrated exercise options
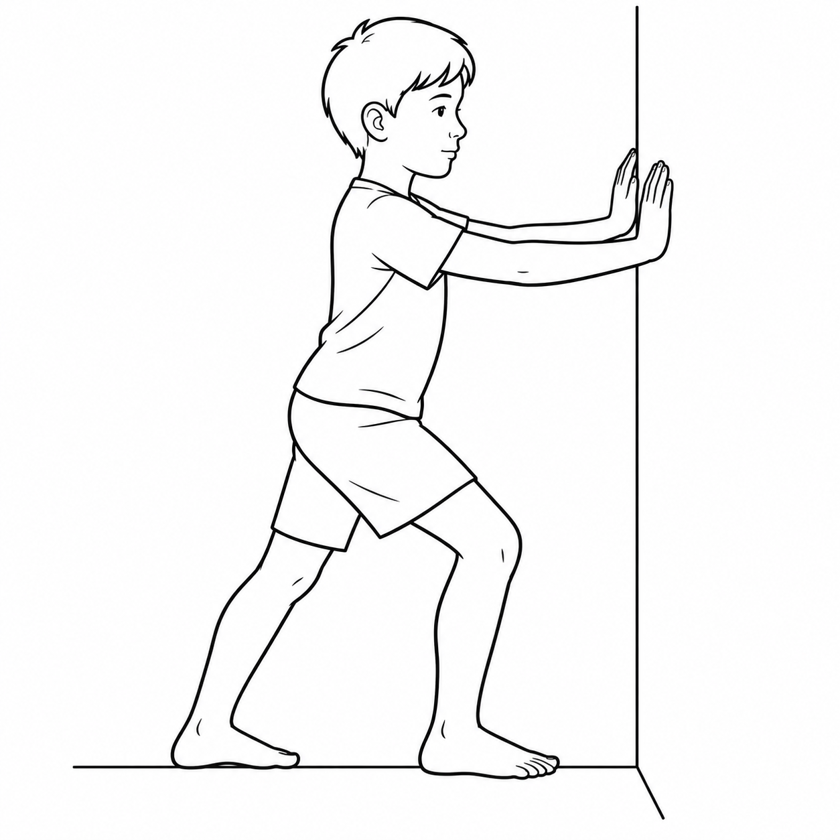
Gentle knee-to-wall mobility
Only for a dorsiflexion limitation assessed by the physiotherapist, after clearance for loading and motion in this position.
In the half-kneeling position shown, place the treated foot forwards; use your hands on the wall for control.
Move the knee a little towards the wall, keeping the heel down and staying within the permitted range.
Do not aim for a preset distance or push through pain or blocking at the front of the ankle. Return slowly to the starting position.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
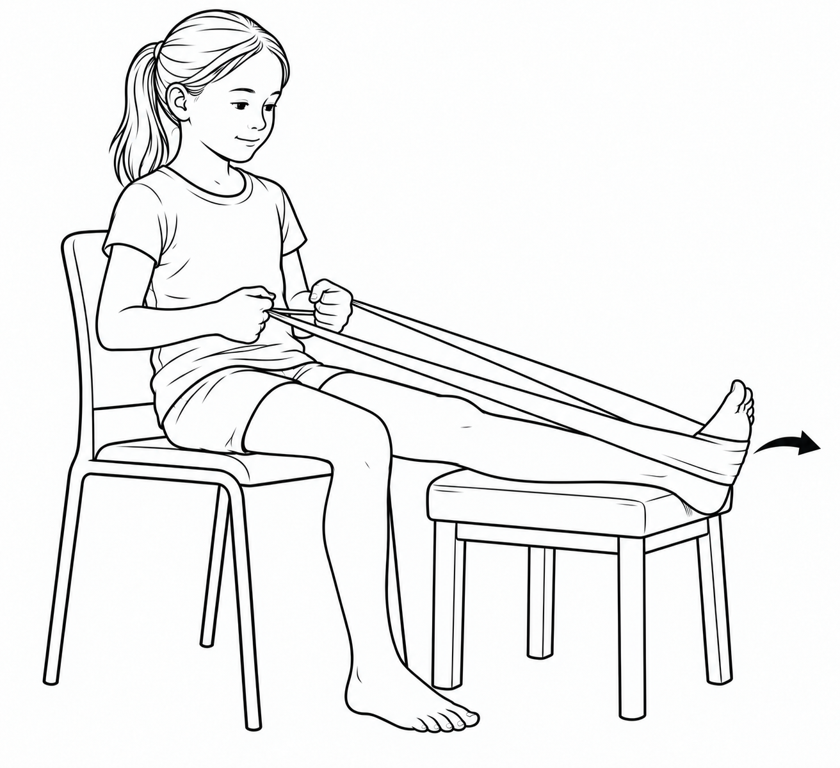
Resisted ankle plantarflexion
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Sit with the leg supported, loop the band around the forefoot and hold the ends towards your body as shown.
Slowly point the foot down within the permitted range, then return with control; the band must not press painfully on the foot.
The arrow shows only pointing the foot down: do not use one anchor for all four directions.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
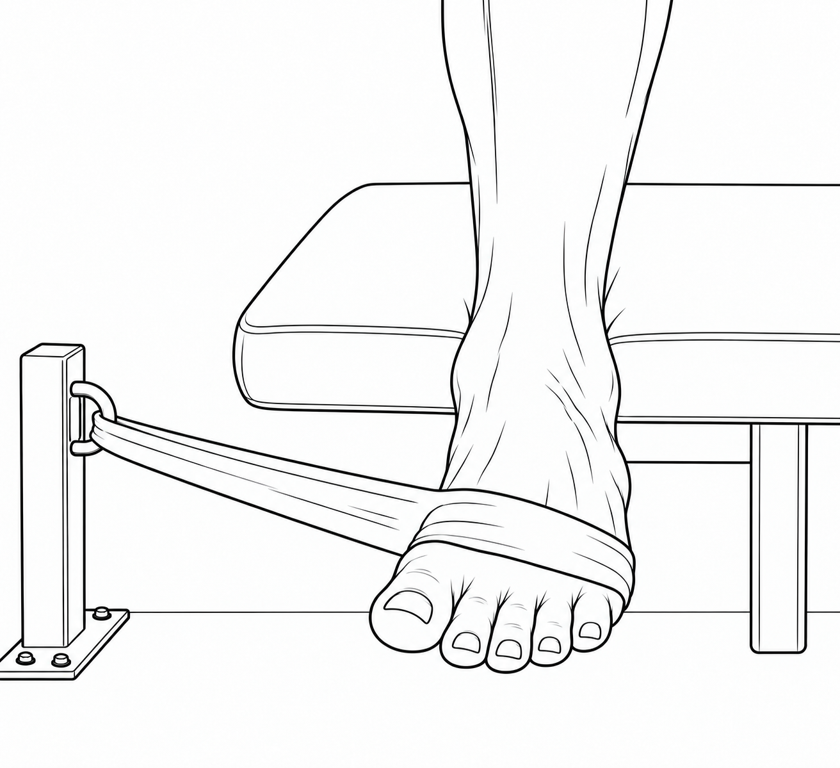
Resisted ankle eversion
Only after clearance for resisted eversion and demonstration by the physiotherapist.
Sit with the legs supported; have the band positioned to pull inwards, as shown.
Move the forefoot slightly outwards while keeping the leg still; the movement should not come from the hip.
Return slowly without letting the band snap back. Do not force end range; stop for deep pain.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
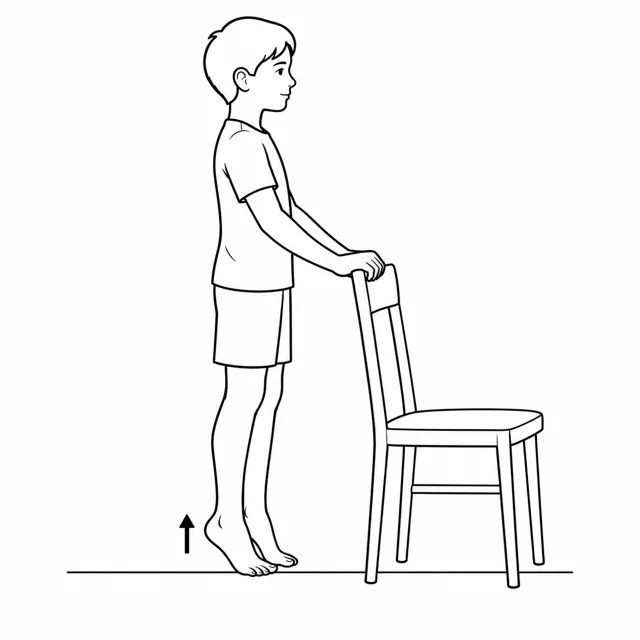
Supported double-leg calf raises
Only after clearance for full weight bearing and calf strengthening.
On a level floor, place your hands on a stable support as illustrated.
With both feet, slowly raise the heels and lower them with control.
Do not independently progress to one leg or a step edge. Stop for joint pain and monitor the subsequent response.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
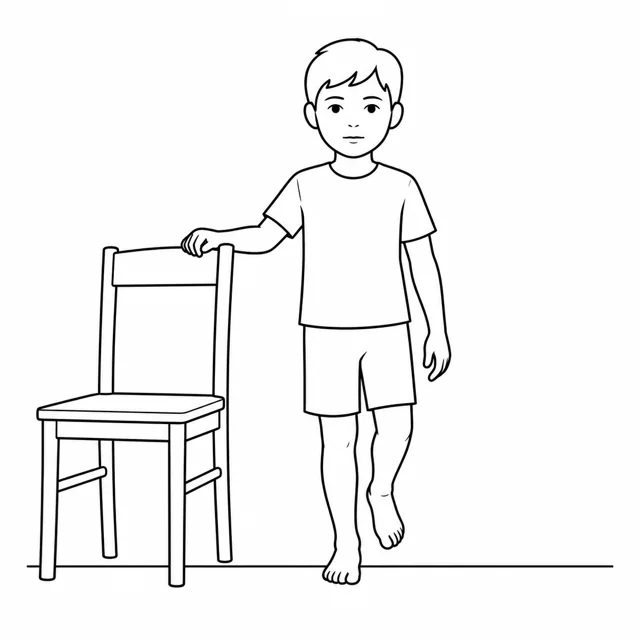
Firm-ground balance
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
On firm ground with eyes open, slightly lift the other foot while keeping the pelvis level.
Keep one hand on a stable support as illustrated; an adult must be able to assist the child.
Put the free foot down before losing control. Do not add cushions, closed eyes or perturbations.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
3. Control and impact
After basic functional recovery
Goals
Prepare running, jumping and deceleration.
Physiotherapy plan
Progress strength and dynamic balance; unstable surfaces only if useful and controlled.
Before running: nonlimping gait, adequate motion, strength, balance and push-off without increased pain or swelling; begin straight walk-run intervals. Add small landings and hops only after impact control.
Precautions
Do not progress with pain, giving way or deterioration after exercise.
Criteria the treating team checks before progression
Controlled, tolerated running and landings.
Confidence in weight bearing and no giving way.
Illustrated exercise options
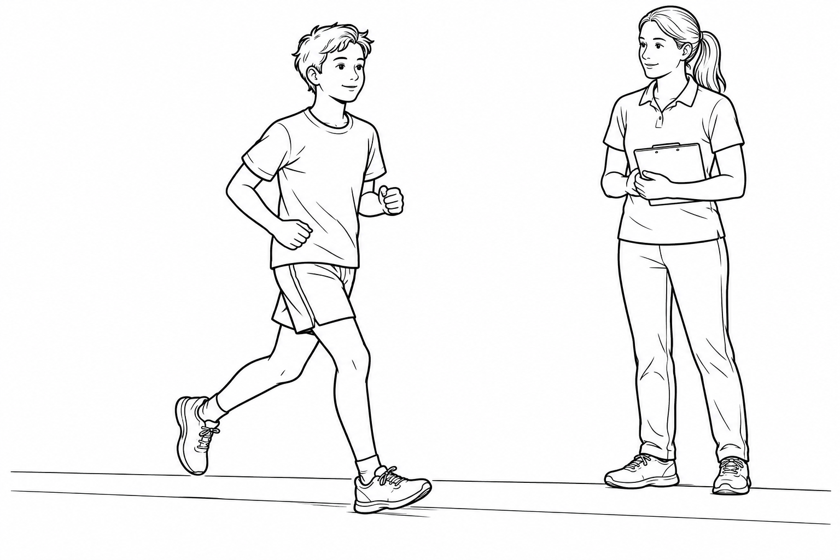
Straight-line walk–run progression
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
On level, even ground, alternate walking with short bouts of easy straight-line jogging according to the physiotherapist’s programme.
Keep an even gait without limping. Begin without sprinting, hills, jumping or direction changes.
Increase one demand at a time. If joint pain, limping or swelling occurs during the work or the next day, stop the progression and report it to the physiotherapist.
Dose and progression: Run/walk intervals, duration and recovery set by the physiotherapist for the procedure, age and response to loading; the phase does not provide an automatic dose.
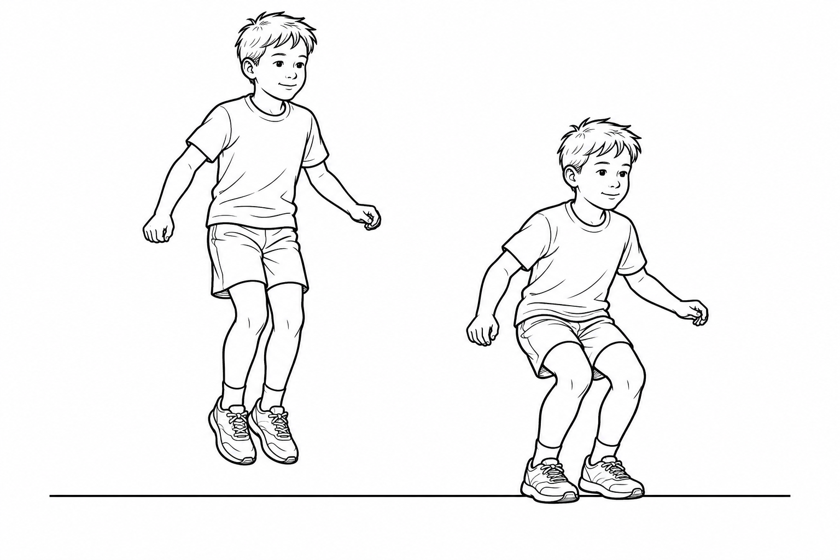
Small two-foot forward hops
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
With the physiotherapist, make one small two-foot forward hop on a firm, even surface, as illustrated.
Land on both feet with control and pause before repeating. The physiotherapist selects distance and number of hops; no sideways or single-leg hops without further instruction.
Stop for pain or loss of control and report pain or swelling afterwards.
Dose and progression: Initial attempts and dose selected by the physiotherapist; increase only after checking the subsequent response.
4. Sport and prevention
After required skills recover
Goals
Resume training and competition.
Physiotherapy plan
After tolerated running and landings, progress planned deceleration and direction changes to reactive sport tasks.
Partial then full training; maintain strength/balance, with bracing or taping if indicated.
Precautions
No competition before full training is tolerated.
Criteria the treating team checks at the end of the pathway
Full training without pain or new swelling.
Recovery of the domains below and a shared return decision.
Illustrated exercise options
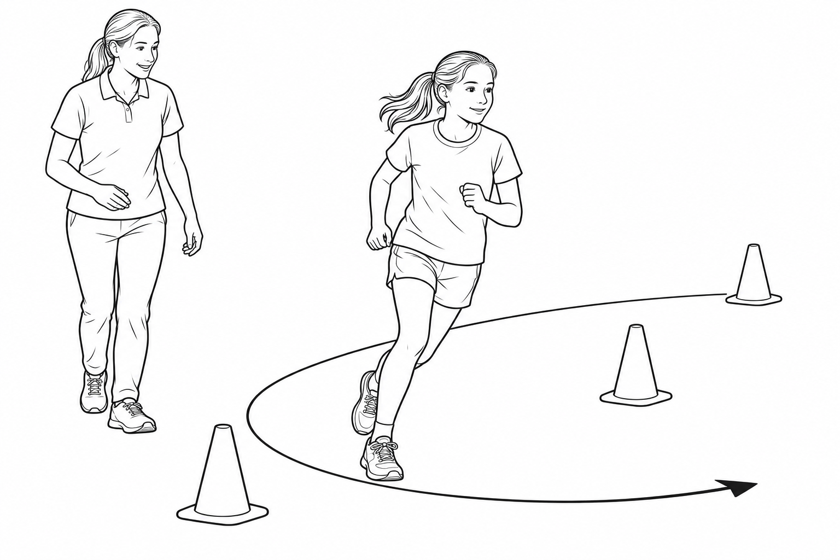
Planned braking and direction changes
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
With the physiotherapist, begin with controlled slowing and wide turns at low speed in agreed directions.
Control the trunk, knee and foot. Increase speed and turning angle separately; sharp, reactive or contact movements require further assessment.
Stop for pain, giving way or limping; also report swelling or pain after the session and the next day.
Dose and progression: Intervals, rests and recovery days selected for age, sport and previous level. No independent maximal tests; tolerate full training before competition.
Return to sport / full activity
Assess the PAASS domains; there is no universal numerical threshold validated for every child.
Pain during activity and the previous 24 hours, alongside swelling and the subsequent response.
Motion, strength, balance and dynamic control adequate for the required tasks.
Ankle confidence, no giving way and readiness to return.
Sport skills and full training tolerated.
Warning signs: stop and contact the treating team
Inability to walk after injury or focal bony pain (malleoli, navicular, fifth-metatarsal base): medical assessment to decide on imaging.
Pain above the ankle, locking, deep pain or repeated giving way: reassessment, without provocative home tests.
Worsening or non-improving pain or swelling: medical review. A very hot, swollen, painful joint needs urgent assessment even without fever; a cold or numb foot needs emergency care immediately.
Guidelines and literature
Sources inform the pathway; they do not validate every dose for an individual child.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
Select the exact phase assigned by the treating team, then choose each prescribed activity. No exercise is selected automatically. The team sets loading, movement, aids, dose and frequency; missing instructions must be completed before use, including by hand.
Browse illustrated exercise options
Only after clearance for motion and brace removal for this exercise.
Only for a dorsiflexion limitation assessed by the physiotherapist, after clearance for loading and motion in this position.
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Only after clearance for resisted eversion and demonstration by the physiotherapist.
Only after clearance for full weight bearing and calf strengthening.
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
Only after jump clearance and an on-the-spot landing check by the physiotherapist. The figure shows the forward progression, to introduce with them.
After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
Choose the current phase to prepare a printable sheet.
Phase safety summary ·
COMPLETE BEFORE EXERCISING — The treating team must complete the blank instructions, including handwritten entries, before this sheet is used.
Follow the assigned phase and instructions confirmed by the treating team; filling in fields does not authorise exercise.
No exercises assigned. This is a safety summary, not a complete exercise prescription.
Individual instructions for this phase
Loading (how much weight on the leg): ________________________________
Brace and crutches: ________________________________
Procedure and starting conditions
Before starting: Record diagnosis, weight-bearing ability, pain, swelling and any brace. After injury, inability to walk or bony pain needs medical assessment.
Loading and protection: Progress weight bearing as tolerated, using crutches when needed. Severe injuries may need brief immobilisation; do not prolong it independently.
Advice before starting
Walk within tolerance using the recommended aids; do not force the ankle. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
Perform a small selection of exercises and check the response afterwards too.
You need to complete training before returning to competition.
Warning signs: stop and contact the treating team
Inability to walk after injury or focal bony pain (malleoli, navicular, fifth-metatarsal base): medical assessment to decide on imaging.
Pain above the ankle, locking, deep pain or repeated giving way: reassessment, without provocative home tests.
Worsening or non-improving pain or swelling: medical review. A very hot, swollen, painful joint needs urgent assessment even without fever; a cold or numb foot needs emergency care immediately.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.