Combined pathway protecting the repaired meniscus while restoring ACL strength and function.
Sport resumes after timing and criteria for both procedures; meniscal repair does not shorten ACL recovery.
For physiotherapists: adapt exercises, dosage and progression to the injury or procedure, protection, permitted loading and movement; check clinical criteria, not elapsed time alone.
Scope and before starting
This pathway covers ACL reconstruction with meniscal repair, not meniscectomy. The physiotherapist needs the operative report for tear and repair type, stability, prescribed loading, ROM and brace. During each phase, the restriction protecting either procedure takes precedence.
Operative plan
Record tear type and location, repair stability, associated procedures and written limits: permitted weight bearing, knee bending and straightening (range of motion, ROM), and brace use.
Meniscal protection
A stable vertical tear may allow early loading with limited movement; repair of a complete radial tear or the meniscal attachment (root) often needs no weight bearing and protected flexion for about 6 weeks. Follow the prescription.
Impact
For at least 4 months avoid deep loaded knee bends, jumps and knee rotation. This precaution comes from expert consensus; repair type and follow-up may require longer protection.
Repair type determines early loading and motion. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
The physiotherapist increases exercises after checking the knee, strength and gait.
Both meniscus and ACL must be ready before competition.
Treatment phases and illustrated exercises
Exercises are shown in their assigned starting phase, with their instructions and precautions. The physiotherapist selects them for the individual plan; the complete protocol is not a prescription to perform them all.
Respect the minimum times and protection required for the procedure. Time alone does not authorise progression: the treating team checks the clinical criteria.
Preoperative preparation (prehabilitation)
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Goals
Full extension, or symmetrical to the uninjured knee.
Near-full flexion.
Minimal effusion (a "dry" knee).
Walking without significant limp, ideally without crutches.
Good voluntary quadriceps control and activation, with no extension lag.
Strength recovery compatible with the clinical picture of the injured limb.
Education on brace, crutches, allowed weight bearing and the early post-operative phases.
Preparation plan
Effusion and pain control (ice, elevation, load management).
Practical education on brace, crutches, allowed weight bearing and the goals of the first weeks.
Daily home programme, alongside physiotherapy sessions.
Precautions
Mechanical locking or a reducible bucket-handle tear: early treatment, without delaying to complete prehabilitation.
Meniscal tear with an indication for early repair, where delay reduces reparability.
Associated chondral or osteochondral lesions requiring timely treatment.
Criteria checked by the treating team
Full or symmetrical extension and near-full flexion.
A dry knee, or a stable minimal effusion.
Smooth gait, without antalgic limp.
Effective quadriceps contraction, with no extension lag on straight leg raise.
The young patient and family can use crutches and brace and understand the first post-operative weeks.
When preparation is useful
The preoperative phase can resemble that of isolated ACL reconstruction, but must respect pain, any joint locking and the meniscal tear pattern.
With a bucket-handle tear, mechanical locking or an indication for early repair, surgery takes priority.
Exercises must be filtered by the physiotherapist: deep loaded flexion and twisting are avoided.
Home and school preparation
Organise movement at home: clear pathways, remove rugs, keep useful items within reach.
Prepare ice, a support for the heel, comfortable clothing and crutches already adjusted.
Inform school or the sports club: plan the absence, temporary exemption and gradual return.
Agree the first post-operative physiotherapy session in advance.
Preoperative preparation may improve pre-surgical strength and function and support early recovery after reconstruction. It is not a guarantee of the final outcome: the post-operative pathway remains decisive. Dosages and duration are indicative and must be adapted by the physiotherapist.
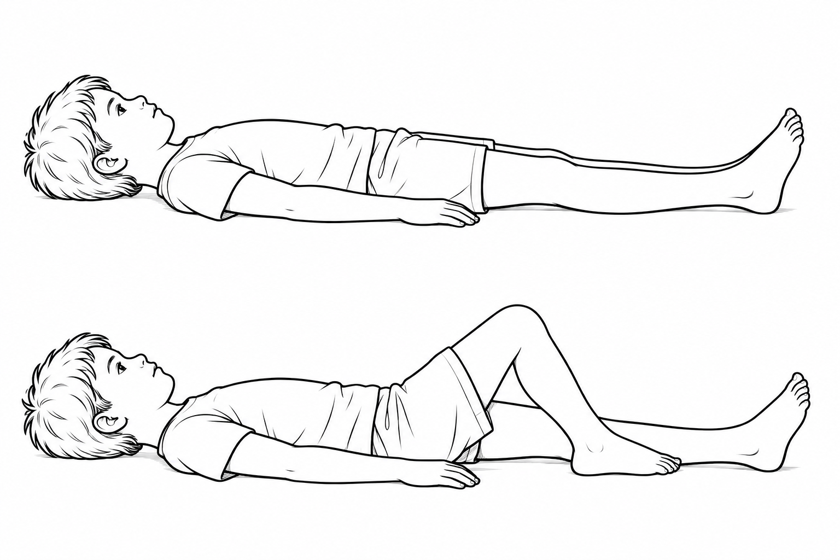
Quadriceps isometric contraction (quad set)
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Lying down, knee straight in a neutral position on the surface; if proprioceptive feedback helps, place a small rolled towel under the knee.
Contract the quadriceps pushing the back of the knee toward the surface, hold, then release slowly.
Aim for a visible, global quadriceps contraction, without breath holding.
Dose and progression: Indicative: 10 contractions of 5 seconds, 2-3 times a day. To be adapted with the physiotherapist.
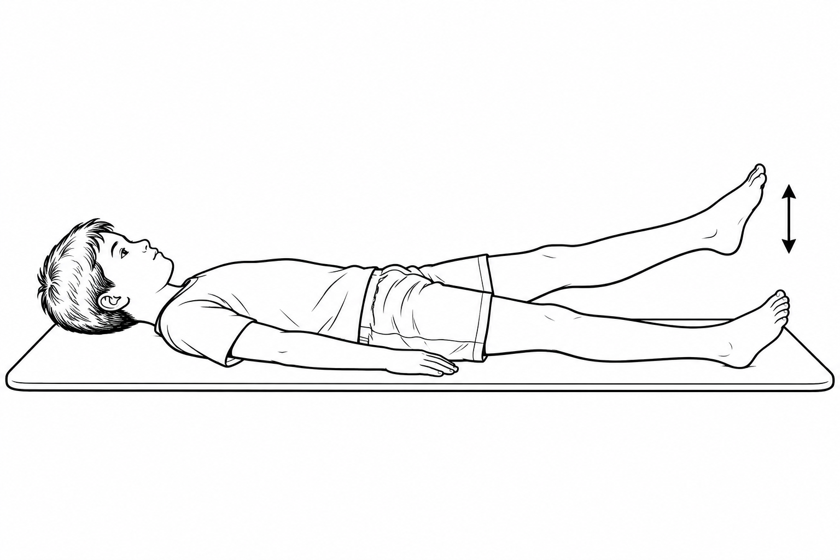
Straight leg raise (only if there is no extension lag)
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
First contract the quadriceps and lock the knee in full extension.
Lift the straight leg about 30 cm keeping the knee straight, then lower it slowly.
If the knee drops into flexion during the lift (extension lag), stop and work on quad sets first.
Dose and progression: Indicative: 2-3 sets of 8-10 repetitions. To be adapted with the physiotherapist.
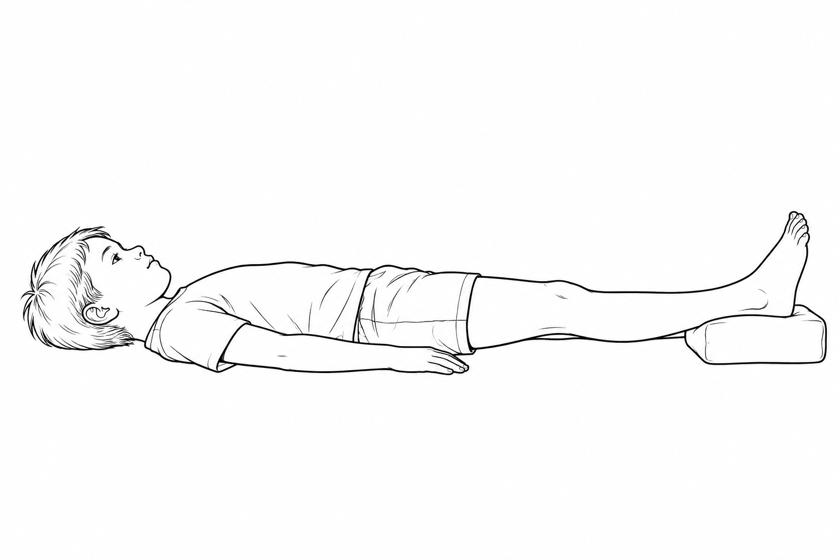
Extension recovery with the heel supported
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Lying down, rest only the heel on a low support leaving the knee unsupported.
Let the knee drop under gravity with the thigh relaxed; a gentle quadriceps contraction can be added.
Do not force and do not push abruptly on the knee: extension returns with time and relaxation.
Dose and progression: Indicative: 3-5 minutes, several times a day if well tolerated.
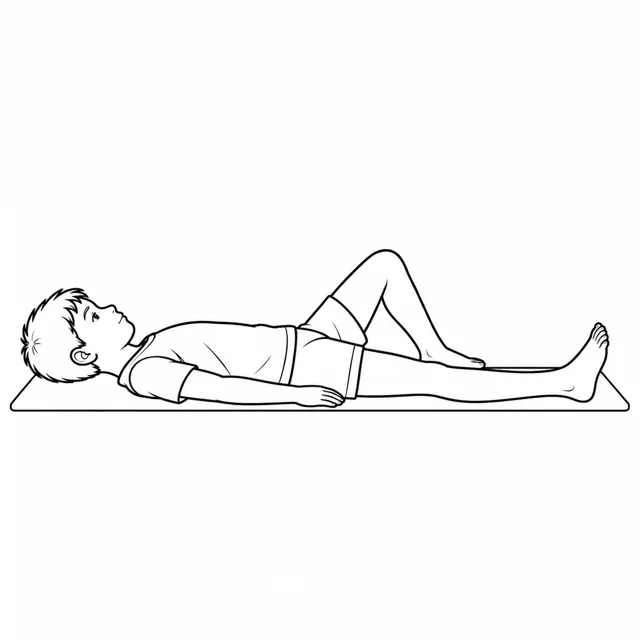
Heel slides / active-assisted flexion
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Lying down, slide the heel toward the buttock keeping the foot in contact with the surface.
You may assist with your hands or a towel around the leg, staying within the pain-free range.
Return slowly to the start position, regaining full extension.
Dose and progression: Indicative: 10-15 repetitions, 2-3 times a day.
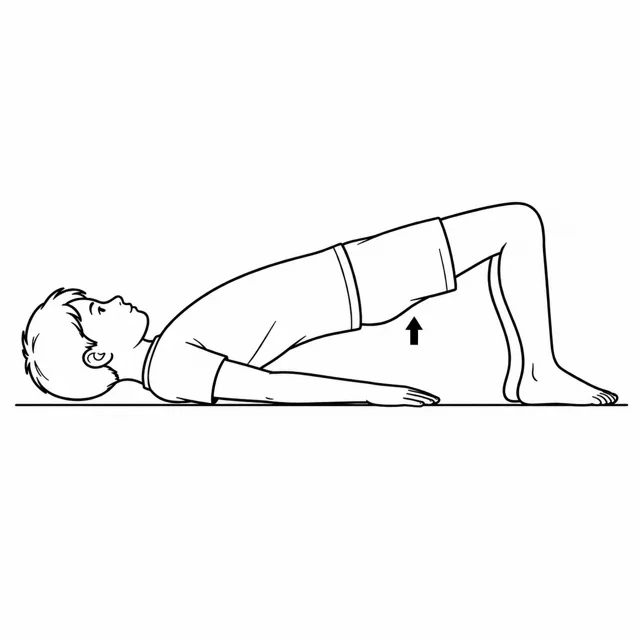
Bridge
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Supine, knees bent and feet hip-width apart on the floor.
Lift the pelvis squeezing the glutes, without arching the back, then lower slowly.
Dose and progression: Indicative: 2-3 sets of 10-12 repetitions.
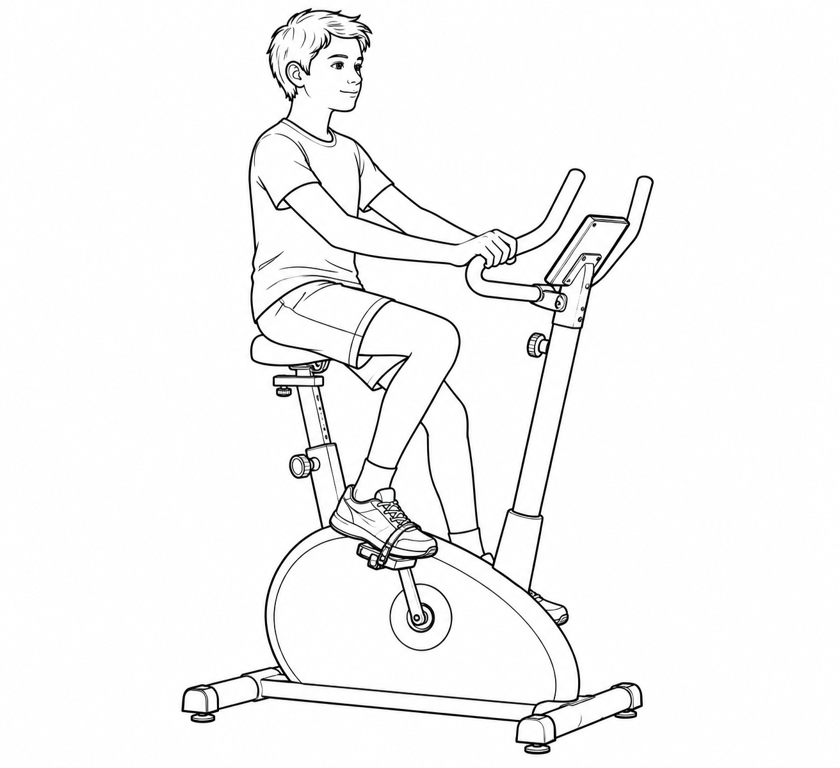
Stationary bike
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
To be introduced when range of motion and pain allow: raise the saddle if flexion is still limited.
Continuous pedalling at low resistance, pain-free and without increased swelling in the following hours.
Dose and progression: Indicative: 10-20 minutes, as tolerated.
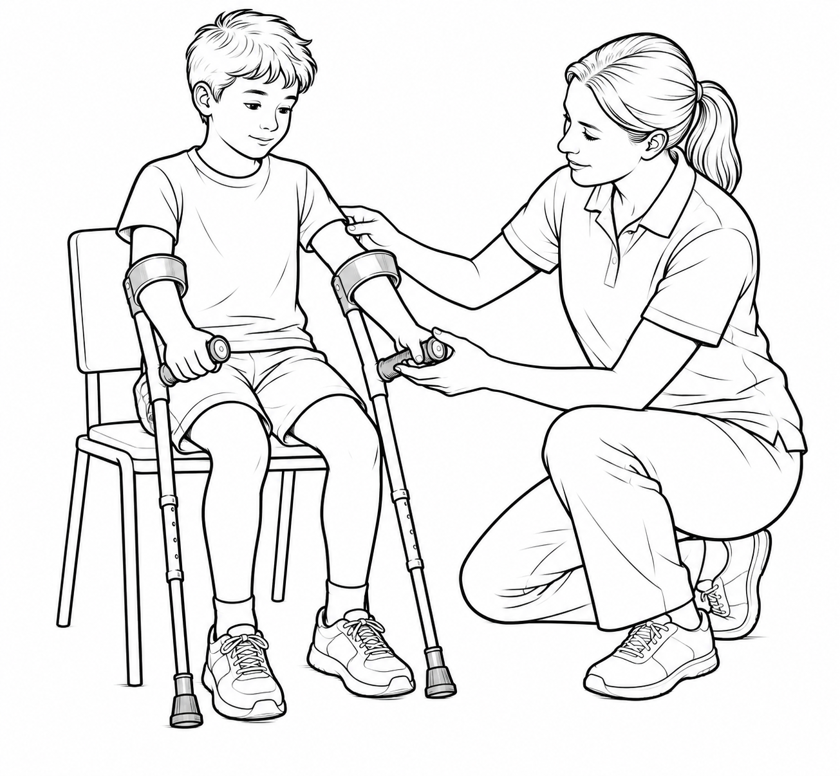
Crutch and weight-bearing training
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Try the crutches before surgery, with correct height and the weight-bearing status set by the surgeon.
Practise on level ground, stairs and the entrance to your home, with someone assisting.
Also practise sitting, standing and moving in the bathroom while respecting the planned loading restrictions.
Dose and progression: At least one training session before admission; repeat until the technique is safe.
Phase 1 · Protect both repairs
Early weeks; meniscal restrictions often last about 6 weeks
Goals
Control effusion and regain permitted extension.
Activate quadriceps without stressing the repair.
Physiotherapy plan
Quadriceps isometrics and ROM within written limits; straight-leg raise only if permitted and without lag.
Walk with prescribed aids, loading and brace.
Precautions
No loading, flexion or twisting beyond repair-specific limits.
Criteria the treating team checks before progression
Decreasing effusion and controlled quadriceps activation.
Safe use of aids and clarified next-step instructions.
Illustrated exercise options
Quadriceps isometric contraction (quad set)
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
Lie on your back with the leg supported and the knee within the authorised extension range.
Tighten the front of the thigh without lifting the leg or forcing the knee. Use a small support under the knee only if demonstrated by your physiotherapist.
Hold briefly and relax. Lifting the heel is neither a target nor proof of full extension.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
Controlled straight-leg raise
When motion and muscle activation are permitted and you can keep the knee straight without it sagging; practise first with the physiotherapist.
Lie on your back, position the other leg within its permitted range and keep the exercising leg as instructed; if both sides are treated, respect each side’s limits.
Tighten the thigh and slightly lift the leg while keeping the knee straight; lower it slowly.
If the knee bends during the lift, return to a supported quadriceps contraction. No ankle weights; do not remove a brace without permission.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
Phase 2 · Progressive loading and strength
After loading clearance, often between week 6 and month 4
Goals
Restore gait, ROM and strength according to repair.
Physiotherapy plan
Increase loading and gait practice as prescribed.
Dynamic strength with partial squats and steps only within cleared loading and range; single-leg balance after safe weight bearing.
Precautions
No jumps, knee rotation or deep loaded bends for at least 4 months; also respect repair-specific loading and motion limits.
Criteria the treating team checks before progression
Better gait and ROM without mechanical symptoms.
No reactive effusion and documented strength progression.
Illustrated exercise options
Double-leg bridge
When knee flexion, foot contact and pushing through both feet are allowed. This is not a non-weight-bearing exercise.
Lie on your back with knees bent within the permitted range and feet supported.
Slowly lift the pelvis using the buttock muscles, without arching the back or aiming for extra height.
Lower with control. No single-leg bridge, pelvic weights or forefoot-only support without further instruction.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
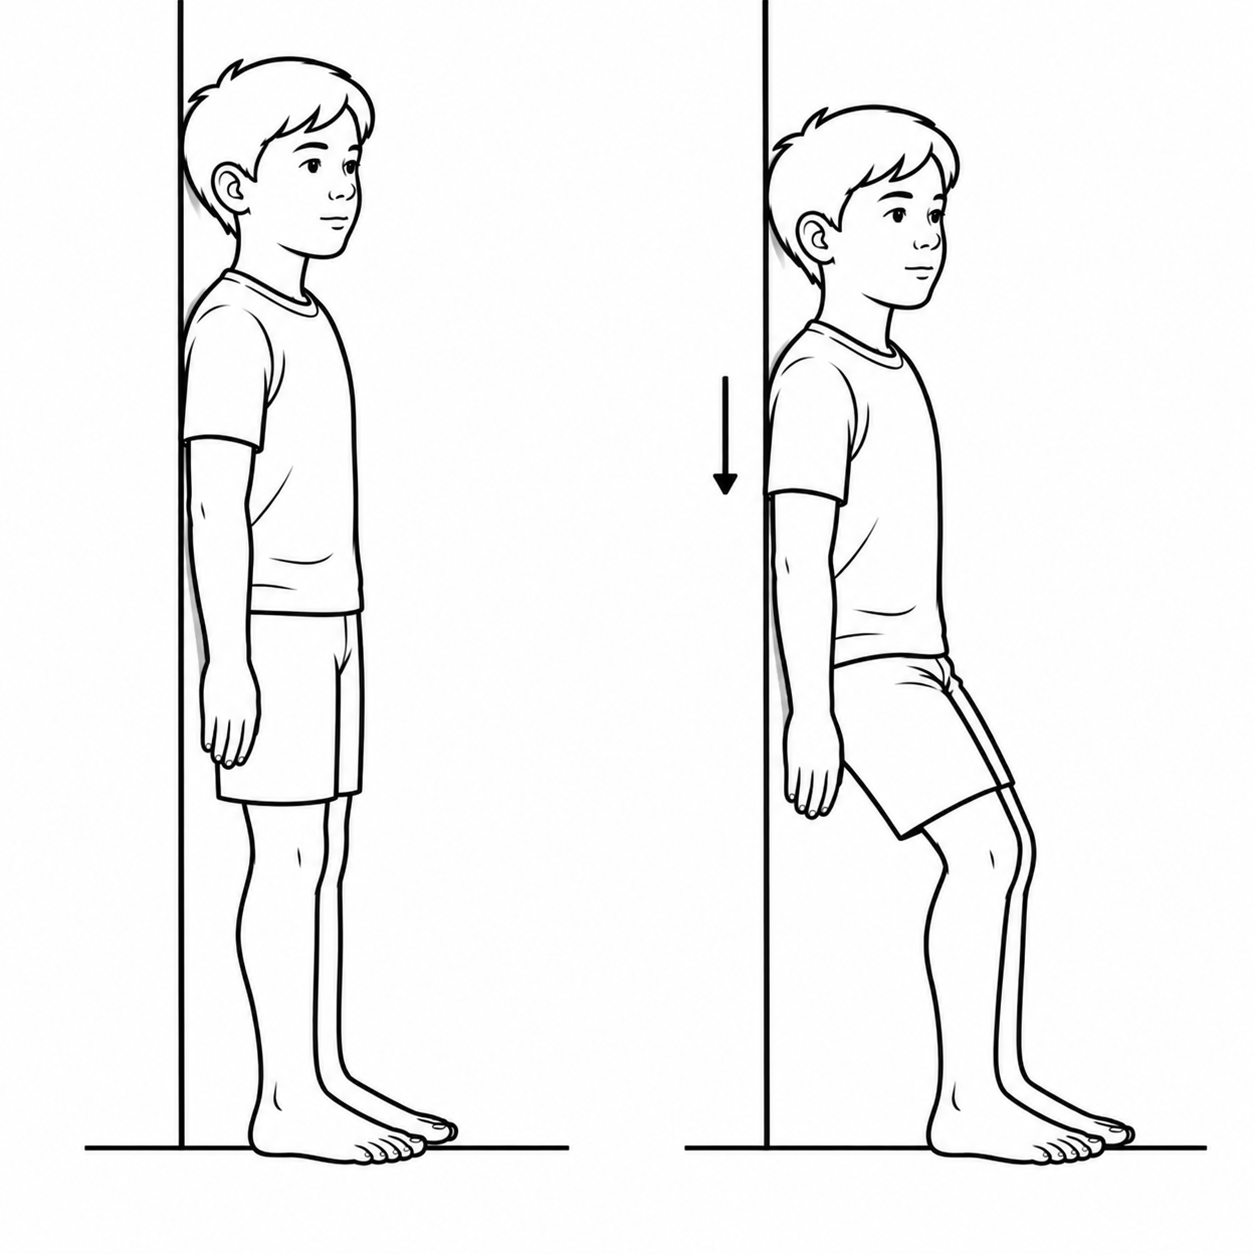
Wall-supported mini-squat
Only after clearance for full weight bearing and strengthening; use the range selected by the physiotherapist.
With your back against the wall as shown, place the feet slightly forward and keep within prescribed loading.
Slide down a short distance within the range set by the physiotherapist, with knees pointing in the same direction as the feet.
Return slowly. Do not copy the illustrated depth if it exceeds your prescribed limit.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
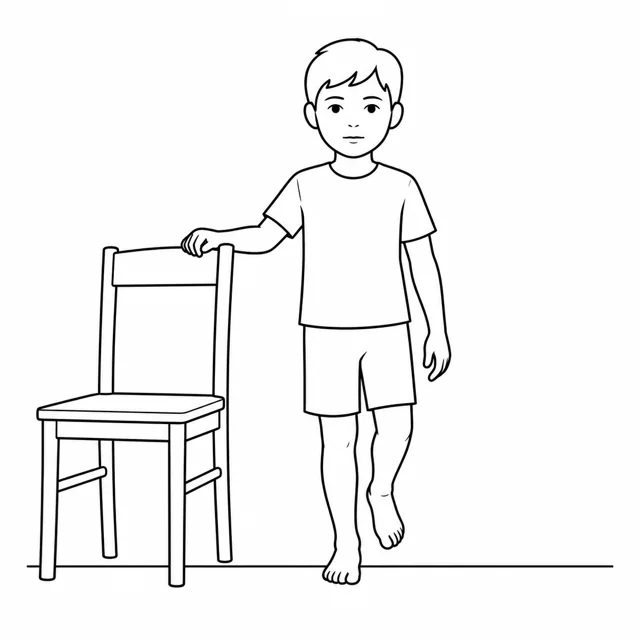
Firm-ground balance
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
On firm ground with eyes open, slightly lift the other foot while keeping the pelvis level.
Keep one hand on a stable support as illustrated; an adult must be able to assist the child.
Put the free foot down before losing control. Do not add cushions, closed eyes or perturbations.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
Easy stationary cycling
Only if the treating clinician permits cycling, pedal loading and the movement range. Cycling is not equivalent to complete offloading.
Use a stationary bike suited to your height; the physiotherapist adjusts the seat and supports for the permitted movement.
Pedal seated and slowly with minimal resistance; do not force a complete revolution if motion is still insufficient.
Do not stand on the pedals, sprint or increase duration and resistance together. Monitor pain, movement quality and swelling during the session and the next day. If they worsen, stop the activity that causes them and inform the team; absence of swelling alone does not authorise increasing the load.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
Phase 3 · Running and impact
After protection and criteria; complex repairs may take longer
Goals
Tolerate straight-line running then simple impact.
Physiotherapy plan
Before running, check restored extension, no effusion or meniscal symptoms and nonlimping gait; measure quadriceps strength with dynamometry/isokinetics if available and assess an age-appropriate step-down. Record both limbs' values without relying on an adult threshold alone; respect repair and ACL protection before walk-run intervals.
Jumps and landings only after at least 4 months, repair review and specific clearance; begin under supervision.
Precautions
Stop loaded flexion or impact if locking, persistent pain or effusion develops.
Criteria the treating team checks before progression
Functional ROM without effusion or mechanical symptoms.
Task-appropriate strength and control without later worsening.
Illustrated exercise options
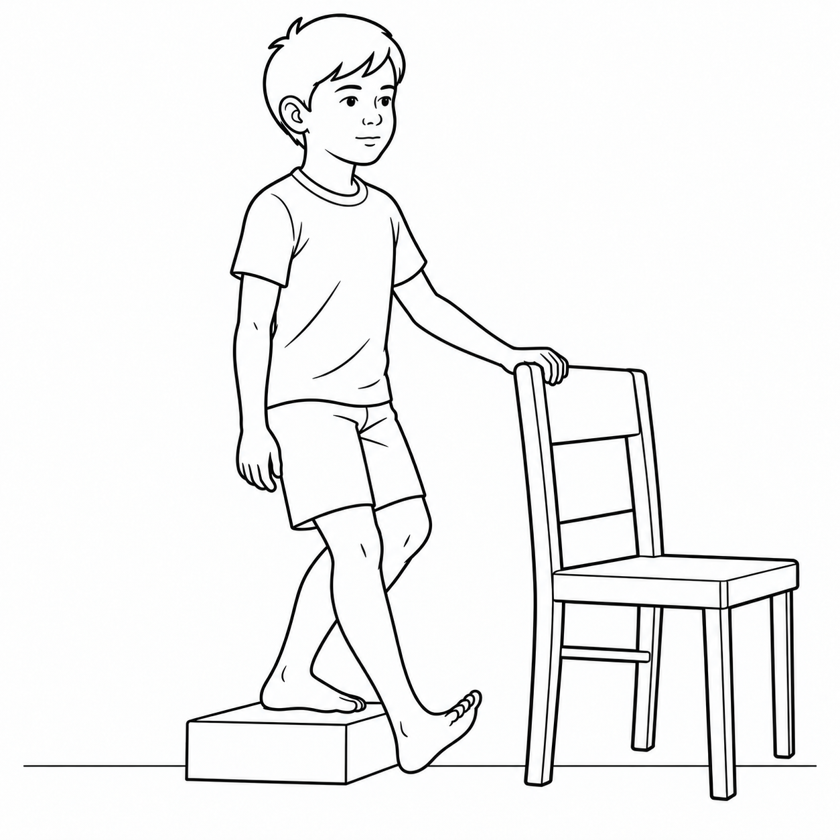
Controlled low step-down
Only after clearance for this exercise: the physiotherapist selects step height, loading and permitted flexion to protect the meniscal repair; there is no universal starting height. After recovering a controlled step-up and receiving clearance for single-leg eccentric work; walking clearance does not automatically permit it.
On a low step, stand on the treated leg and keep a hand on the rail as illustrated.
Slightly bend the knee and lower the free heel towards the floor without dropping down or twisting the pelvis.
Use the free foot and hand support to return as taught. Reduce height and range if movement control deteriorates.
Dose and progression: Use the sets, repetitions or duration, rests and frequency written in your individual handout. Stop before movement control deteriorates; do not choose the dose from the illustration.
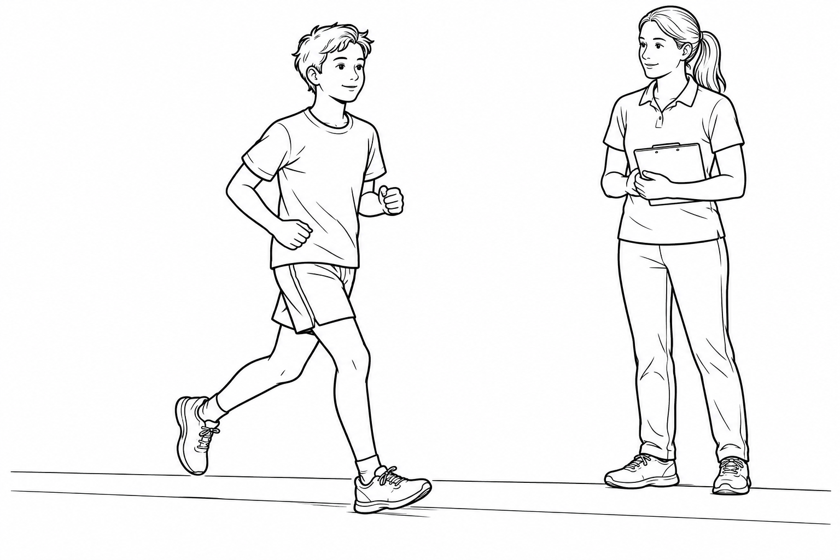
Straight-line walk–run progression
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
On level, even ground, alternate walking with short bouts of easy straight-line jogging according to the physiotherapist’s programme.
Keep an even gait without limping. Begin without sprinting, hills, jumping or direction changes.
Increase one demand at a time. If joint pain, limping or swelling occurs during the work or the next day, stop the progression and report it to the physiotherapist.
Dose and progression: Run/walk intervals, duration and recovery set by the physiotherapist for the procedure, age and response to loading; the phase does not provide an automatic dose.
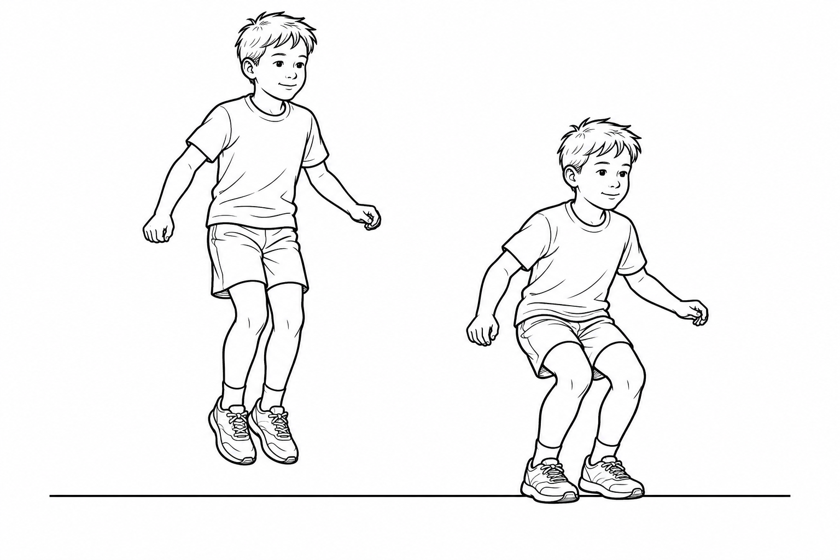
Small two-foot forward hops
No earlier than 4 months after meniscal repair and only after review and jump clearance; complex repairs may need longer. First check on-the-spot landings with the physiotherapist, then this forward progression.
With the physiotherapist, make one small two-foot forward hop on a firm, even surface, as illustrated.
Land on both feet with control and pause before repeating. The physiotherapist selects distance and number of hops; no sideways or single-leg hops without further instruction.
Stop for pain or loss of control and report pain or swelling afterwards.
Dose and progression: Initial attempts and dose selected by the physiotherapist; increase only after checking the subsequent response.
Phase 4 · Sport preparation
During later months, also respecting ACL healing time
Goals
Restore sport movement and confidence without irritating the meniscus.
Physiotherapy plan
Only after tolerated running and landing, progress planned deceleration and cutting to reactive tasks and individual training under supervision.
Move through partial then full training before competition.
Precautions
Meniscal healing alone does not clear pivoting sport.
Criteria the treating team checks at the end of the pathway
No locking, reactive effusion or giving way.
Strength, control and full training assessed together.
Illustrated exercise options
Planned braking and direction changes
No twisting for at least 4 months after repair; complex repairs may need longer. After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
With the physiotherapist, begin with controlled slowing and wide turns at low speed in agreed directions.
Control the trunk, knee and foot. Increase speed and turning angle separately; sharp, reactive or contact movements require further assessment.
Stop for pain, giving way or limping; also report swelling or pain after the session and the next day.
Dose and progression: Intervals, rests and recovery days selected for age, sport and previous level. No independent maximal tests; tolerate full training before competition.
Return to sport / full activity
Respect both repair healing and ACL recovery; for pivoting/contact sport after skeletal maturity, often no sooner than 9-12 months and later if needed.
No reactive effusion, locking or giving way.
Strength, movement and function measured with several age- and sport-appropriate tasks.
Full training and pivoting movements tolerated without symptoms.
Radial, root or complex repairs and associated procedures may prolong protection. With open growth plates, also use paediatric criteria and growth surveillance.
Warning signs: stop and contact the treating team
Fever or a red/draining wound: contact the team promptly.
Locking, persistent painful catching or loss of extension: stop and seek reassessment.
Increasing effusion or new giving way: reduce and inform the clinician.
New calf pain with swelling: seek urgent medical assessment the same day.
Sudden breathing difficulty or chest pain: seek emergency medical help immediately.
Guidelines and literature
Sources inform the pathway; they do not validate every dose for an individual child.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
Select the exact phase assigned by the treating team, then choose each prescribed activity. No exercise is selected automatically. The team sets loading, movement, aids, dose and frequency; missing instructions must be completed before use, including by hand.
Browse illustrated exercise options
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Indicatively 2-6 weeks, but only if the meniscal lesion allows it: with a locked knee or early indication there is no rigid target of completing weeks of prehabilitation.
Only when the exercise is cleared in the indicated phase, within prescribed loading and motion.
When motion and muscle activation are permitted and you can keep the knee straight without it sagging; practise first with the physiotherapist.
When knee flexion, foot contact and pushing through both feet are allowed. This is not a non-weight-bearing exercise.
Only after clearance for full weight bearing and strengthening; use the range selected by the physiotherapist.
After clearance for full weight bearing and single-leg support; practise first with the physiotherapist.
Only if the treating clinician permits cycling, pedal loading and the movement range. Cycling is not equivalent to complete offloading.
Only after clearance for this exercise: the physiotherapist selects step height, loading and permitted flexion to protect the meniscal repair; there is no universal starting height. After recovering a controlled step-up and receiving clearance for single-leg eccentric work; walking clearance does not automatically permit it.
Only after running clearance under this protocol and assessment of motion, strength and control. Also respect the protection period for the injury or operation.
No earlier than 4 months after meniscal repair and only after review and jump clearance; complex repairs may need longer. First check on-the-spot landings with the physiotherapist, then this forward progression.
No twisting for at least 4 months after repair; complex repairs may need longer. After tolerating straight-line running and receiving specific clearance for braking and direction changes. First practise with the physiotherapist; this is not an initial running exercise.
Choose the current phase to prepare a printable sheet.
Phase safety summary ·
COMPLETE BEFORE EXERCISING — The treating team must complete the blank instructions, including handwritten entries, before this sheet is used.
Follow the assigned phase and instructions confirmed by the treating team; filling in fields does not authorise exercise.
No exercises assigned. This is a safety summary, not a complete exercise prescription.
Individual instructions for this phase
Loading (how much weight on the leg): ________________________________
Brace and crutches: ________________________________
Procedure and starting conditions
Operative plan: Record tear type and location, repair stability, associated procedures and written limits: permitted weight bearing, knee bending and straightening (range of motion, ROM), and brace use.
Meniscal protection: A stable vertical tear may allow early loading with limited movement; repair of a complete radial tear or the meniscal attachment (root) often needs no weight bearing and protected flexion for about 6 weeks. Follow the prescription.
Impact: For at least 4 months avoid deep loaded knee bends, jumps and knee rotation. This precaution comes from expert consensus; repair type and follow-up may require longer protection.
Advice before starting
Repair type determines early loading and motion. If permitted loading or movements are missing from your handout, ask for these to be completed before starting.
The physiotherapist increases exercises after checking the knee, strength and gait.
Both meniscus and ACL must be ready before competition.
Warning signs: stop and contact the treating team
Fever or a red/draining wound: contact the team promptly.
Locking, persistent painful catching or loss of extension: stop and seek reassessment.
Increasing effusion or new giving way: reduce and inform the clinician.
New calf pain with swelling: seek urgent medical assessment the same day.
Sudden breathing difficulty or chest pain: seek emergency medical help immediately.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.
A framework to personalise with the orthopaedic clinician and physiotherapist, not a replacement for an individual prescription. Respect protection and clinical criteria, not dates alone.