Isolated meniscal repair
A meniscal repair pathway tailored to stable vertical, radial, root or complex tears. Weight bearing, ROM and return to sport require instructions specific to the repair performed.
Recovery depends on repair type and criteria; at least 4 months for vertical tears, often 6-9 months for radial, root or complex tears.
Prepare the visit handout
Use the condition and phase indicated by your clinician. You can leave out individual exercises; instructions, illustrations and safety advice remain together.
Changing phase restores its full exercise list. Timing alone does not determine the phase.
Exclude exercises if needed
11 of 11 exercise cards included
The full web page remains available. Your selection is not saved or shared.
This protocol is part of the post-operative pathway and must be adapted to the surgeon’s instructions and to the individual clinical response.
These documents are protocol templates for information and education only: they do not replace the rehabilitation prescription for the individual case. Timing, loading and progressions must always be adapted to the patient, the lesion pattern, the surgical technique used and the clinical course, in collaboration between orthopaedic surgeon, physiotherapist and, where appropriate, physiatrist. Progression is driven by objective criteria, not by the calendar alone.
At a glance — the full pathway
- Weight bearing and ROM: stable vertical tear
- Early weight bearing may be allowed; movement limits depend on repair stability and associated procedures.
- Weight bearing and ROM: complete radial or root tear
- Complete radial tear: non-weight bearing for 4-6 weeks; root tear: non-weight bearing for 6 weeks. Flexion is initially protected, often within 90°; the surgeon must specify duration and brace use.
- Complex or horizontal tears and associated procedures
- Use the specific prescription. Do not extend the early loading of a vertical repair to other patterns; the most restrictive requirement takes precedence.
- Deep flexion, jumping and rotation
- Avoid deep squats, jumping and knee rotation for at least 4 months and until cleared. Partial squats require a specifically permitted range.
- Running and sport
- Elapsed weeks alone do not provide clearance: adequate healing, no pain or effusion, recovered strength and control, and authorisation are required.
Repairing rather than removing the meniscus protects cartilage in the long term, but requires respect for biological healing times: the repair is vulnerable above all to the combination of load, deep flexion and rotation.
Step by step
Each phase offers exercise options: perform only those selected by your clinician, without bringing later phases forward or automatically adding earlier exercises. Dosage, frequency and rests are individualised; the complete catalogue is not a single session.
Before surgery — Short preoperative preparation
Short, conditional phase: a few days or some weeks, depending on symptoms and surgical timing; often around 1-2 weeks for elective surgery. There is no mandatory minimum.
When it applies
- •Only for elective surgery, with an unlocked knee and controllable symptoms.
- •There is no strong specific evidence that a preoperative phase improves the outcome of meniscal repair: the aim is to reach surgery with a less irritable knee and a prepared patient.
Goals before surgery
- •Reduction of effusion.
- •Recovery of extension.
- •Quadriceps activation.
- •Education on crutches, brace and the early post-operative restrictions (flexion and weight bearing).
Activities
- •Pain and effusion control with ice, elevation and activity management.
- •Practical trial of the crutches and brace to be used after surgery.
Preoperative exercises
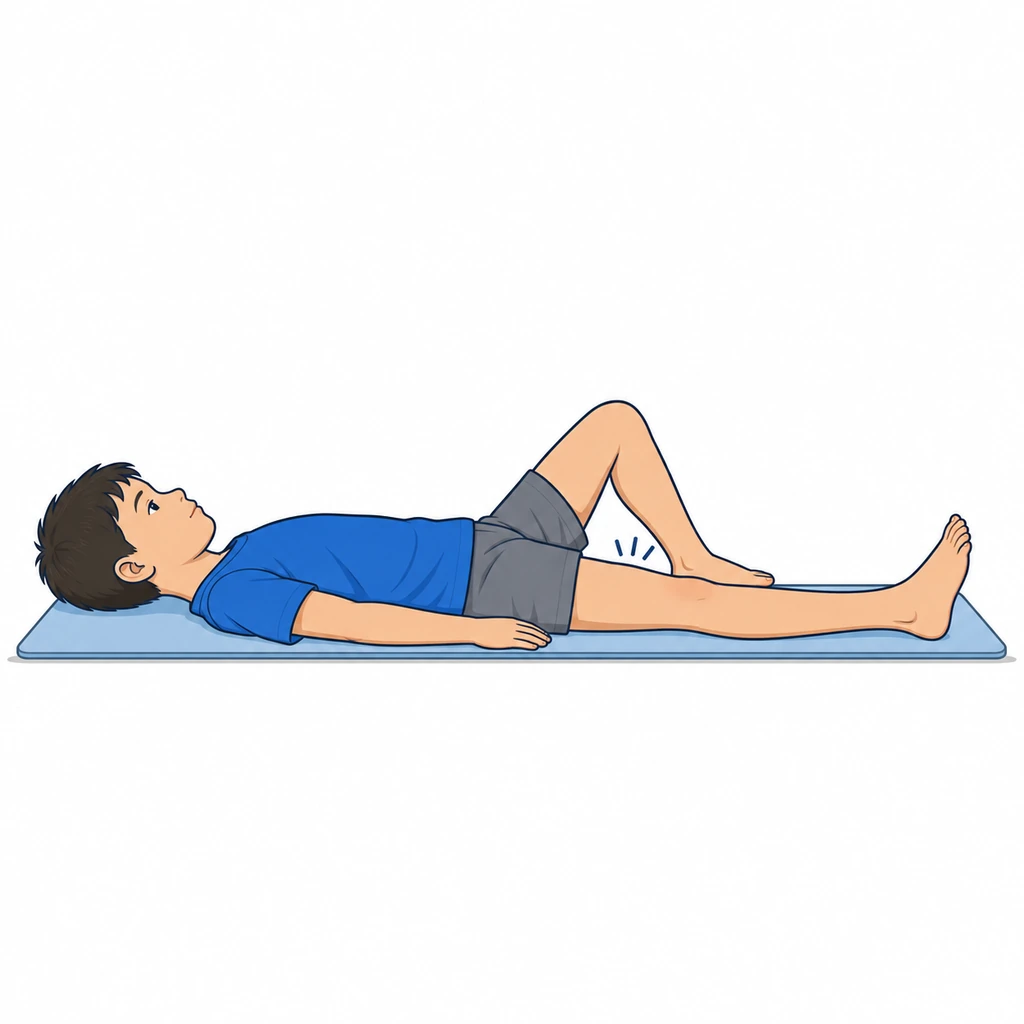
Quadriceps isometric contraction (quad set)
- •Lying down, knee straight in a neutral position on the surface; if proprioceptive feedback helps, place a small rolled towel under the knee.
- •Contract the quadriceps pushing the back of the knee toward the surface, hold, then release slowly.
- •Aim for a visible, global quadriceps contraction, without breath holding.
Dosage: Indicative: 10 contractions of 5 seconds, 2-3 times a day. To be adapted with the physiotherapist.
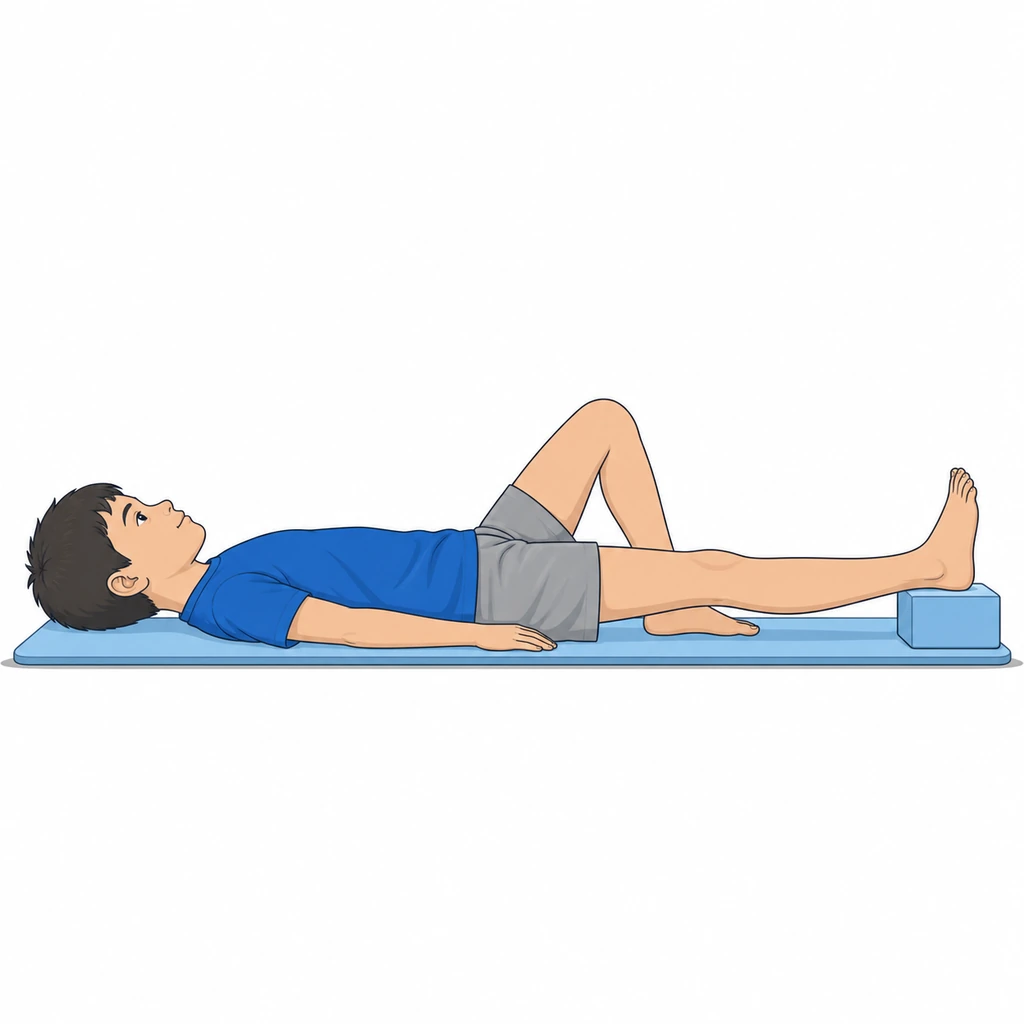
Extension recovery with the heel supported
- •Lying down, rest only the heel on a low support leaving the knee unsupported.
- •Let the knee drop under gravity with the thigh relaxed; a gentle quadriceps contraction can be added.
- •Do not force and do not push abruptly on the knee: extension returns with time and relaxation.
Dosage: Indicative: 3-5 minutes, several times a day if well tolerated.
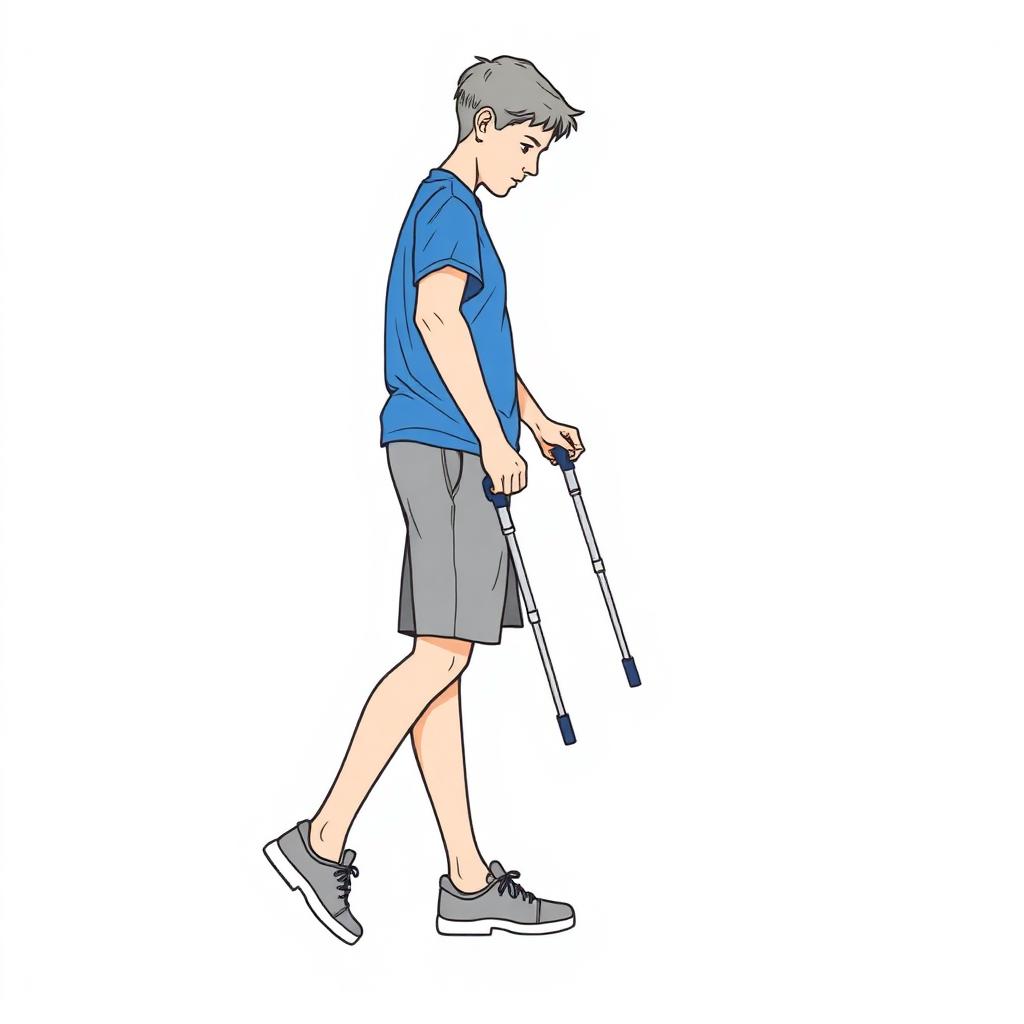
Crutch and weight-bearing training
- •Try the crutches before surgery, with correct height and the weight-bearing status set by the surgeon.
- •Practise on level ground, stairs and the entrance to your home, with someone assisting.
- •Also practise sitting, standing and moving in the bathroom while respecting the planned loading restrictions.
Dosage: At least one training session before admission; repeat until the technique is safe.
Readiness criteria for surgery
- ☐Extension regained or clearly improving.
- ☐Effusion reduced compared with the acute phase.
- ☐Voluntary quadriceps contraction present.
- ☐Patient and family informed about the flexion and loading restrictions expected after repair.
When surgery must not be delayed
- •Locked knee: surgery must not be delayed to complete preparation.
- •Tear requiring early treatment to preserve meniscal reparability.
What to prepare at home and school
- •Organise movement at home: clear pathways, remove rugs, keep useful items within reach.
- •Prepare ice, a support for the heel, comfortable clothing and crutches already adjusted.
- •Inform school or the sports club: plan the absence, temporary exemption and gradual return.
- •Agree the first post-operative physiotherapy session in advance.
Indicative dosages, to be adapted by the physiotherapist. This phase neither replaces nor delays the surgical indication.
Phase 1 — Protect the repair
Indicative timing: First 2 weeks; restrictions may last longer
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Control pain and effusion
- •Maintain permitted extension and activate the quadriceps
What to do
- •Brace, crutches and loading according to the repaired tear pattern
- •Quad sets; leg raise only without lag and if authorised
- •Assisted movement within the prescribed range without forcing
Restrictions and precautions
- •Radial and root repairs: follow the non-weight-bearing parameters
- •No jumping, pivoting, squatting or loaded flexion unless authorised
Exercises for this phase
1. Quadriceps isometric contraction (quad set)After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lie on your back with the leg supported and the knee within the authorised extension range.
- •Tighten the front of the thigh without lifting the leg or forcing the knee. Use a small support under the knee only if demonstrated by your physiotherapist.
- •Hold briefly and relax. Lifting the heel is neither a target nor proof of full extension.
Dosage: 10 contractions of 5 seconds, 4-6 times a day
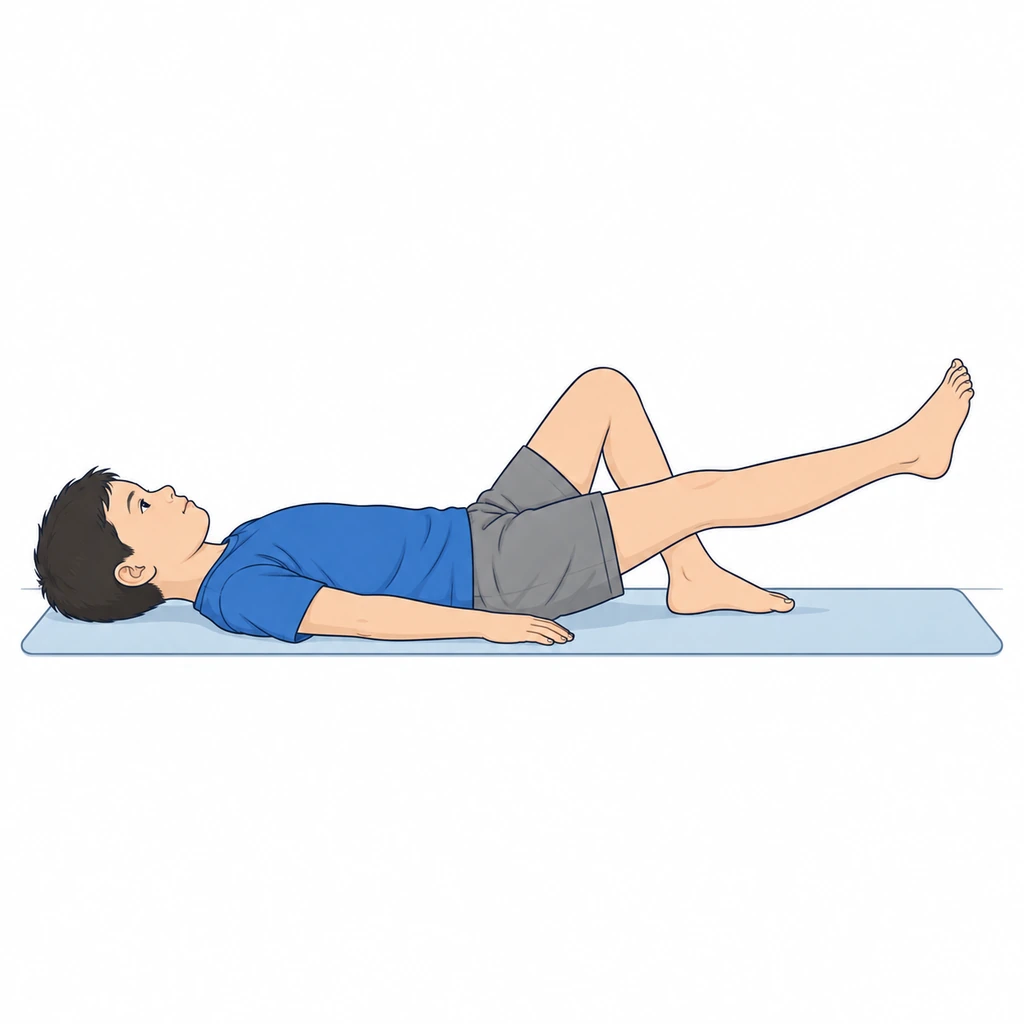
2. Straight-leg raiseAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lying on your back, first tighten the thigh until the knee locks straight.
- •Lift the straight leg about 30 cm, hold 3 seconds and lower slowly.
- •If the knee bends while lifting, the quadriceps is not ready yet: go back to quad sets.
Dosage: 3 sets of 10, twice a day
Ready for the next phase when
- ☐Pain and effusion decreasing
- ☐Safe use of aids
- ☐Scheduled review and subsequent restrictions clarified
Phase 2 — Protected mobility and control
Indicative timing: Weeks 2-6, maintaining repair-specific restrictions
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Recover movement within the allowed limit
- •Maintain activation without stressing the repair
What to do
- •Assisted movement within the prescribed range, without immediately seeking full flexion
- •Hip and core strengthening compatible with non-weight bearing
- •Stable vertical repairs: a mini-squat only within the range and from the date specifically authorised
Restrictions and precautions
- •No standing exercise while non-weight bearing is prescribed
- •Do not automatically introduce squats to 60°, steps or leg press
- •No twisting on a planted foot, jumping or deep flexion
No additional exercise cards are assigned here. Follow this phase’s indications and the programme selected by your physiotherapist; do not automatically continue or progress every previous exercise.
Ready for the next phase when
- ☐Biological protection period completed
- ☐Controlled effusion and effective quad set
- ☐Permission to progress weight bearing and ROM
Note for the physiotherapist
Pain and effusion guide dosage, but their absence does not cancel repair protection times.
Phase 3 — Progressive strength and gait recovery
Indicative timing: After initial protection, approximately week 6 to month 4
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Walk without aids when permitted
- •Progressively recover full ROM
- •Strength and single-leg control
What to do
- •Progress loading only after authorisation
- •Partial squats, steps and other selected exercises within the range allowed for the tear pattern
- •Cycling or alternatives only if compatible with loading and ROM
Restrictions and precautions
- •No deep loaded flexion, jumping or pivoting before at least 4 months and clearance
- •No automatic running at weeks 8-12
Exercises for this phase
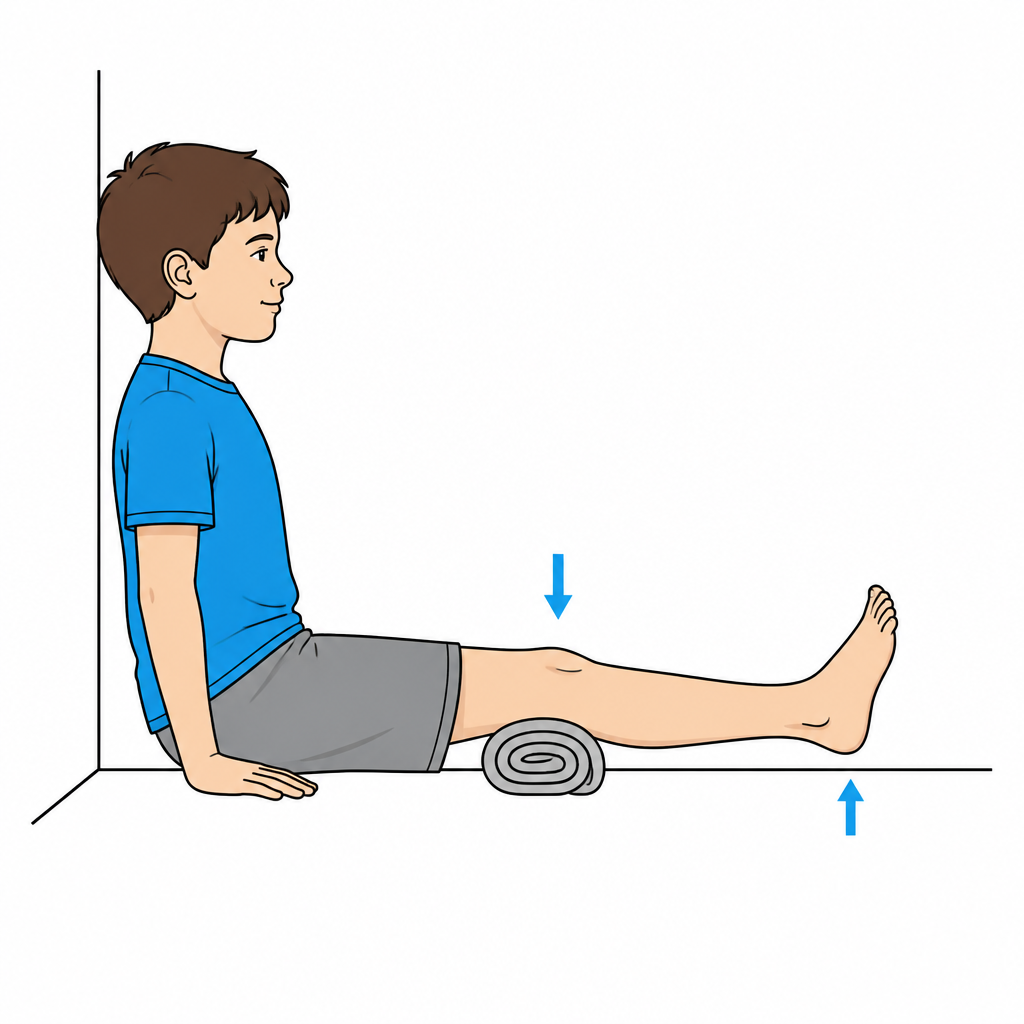
3. Global quadriceps recoveryAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Sitting with a pillow under the slightly bent knee.
- •Extend the knee by pushing the heel forward, keeping the thigh on the pillow.
- •Aim for a full, even contraction of the whole thigh: isolating a single portion of the muscle is not useful.
Dosage: 3 sets of 12, once or twice a day
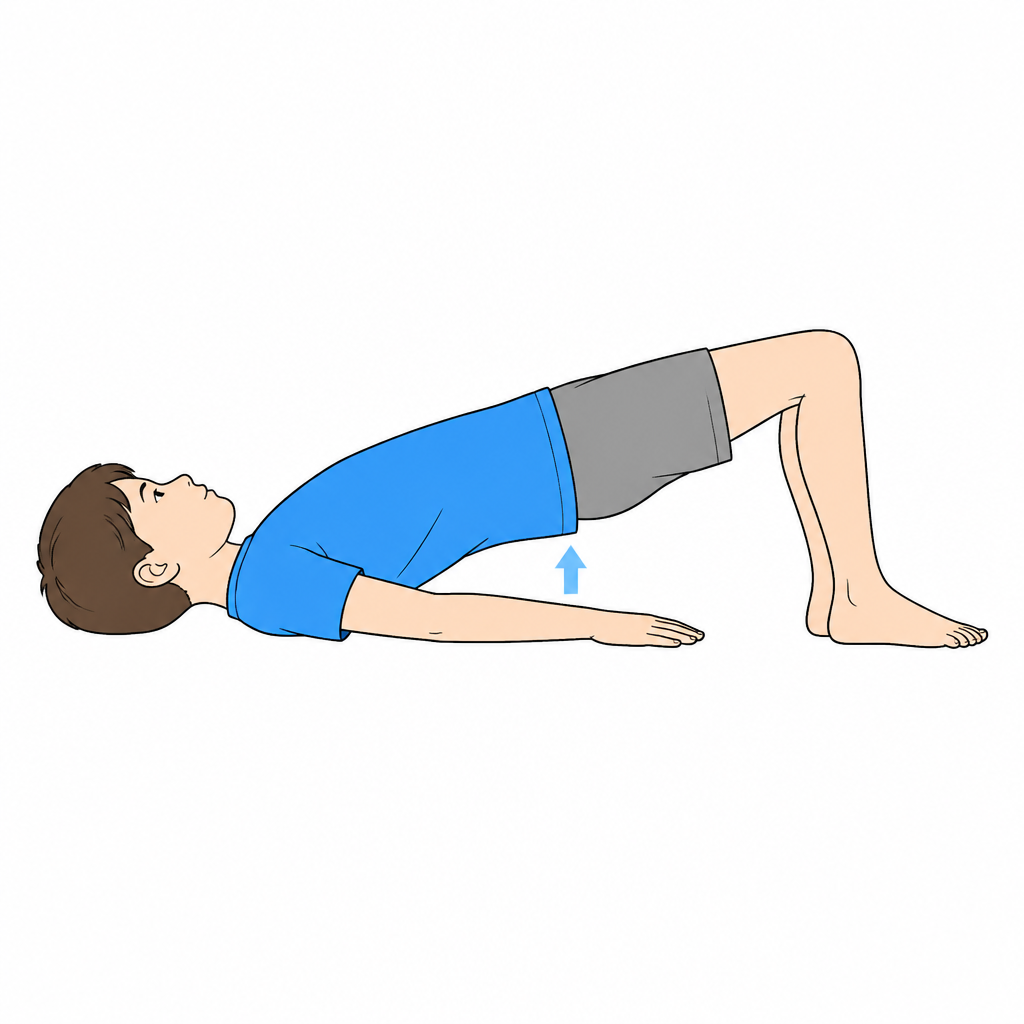
4. Glute bridgeAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Lie on your back, knees bent, feet flat on the floor.
- •Lift the pelvis by squeezing the glutes until shoulders, hip and knee are aligned.
- •Lower slowly without arching the back.
Dosage: 3 sets of 12-15, on alternate days
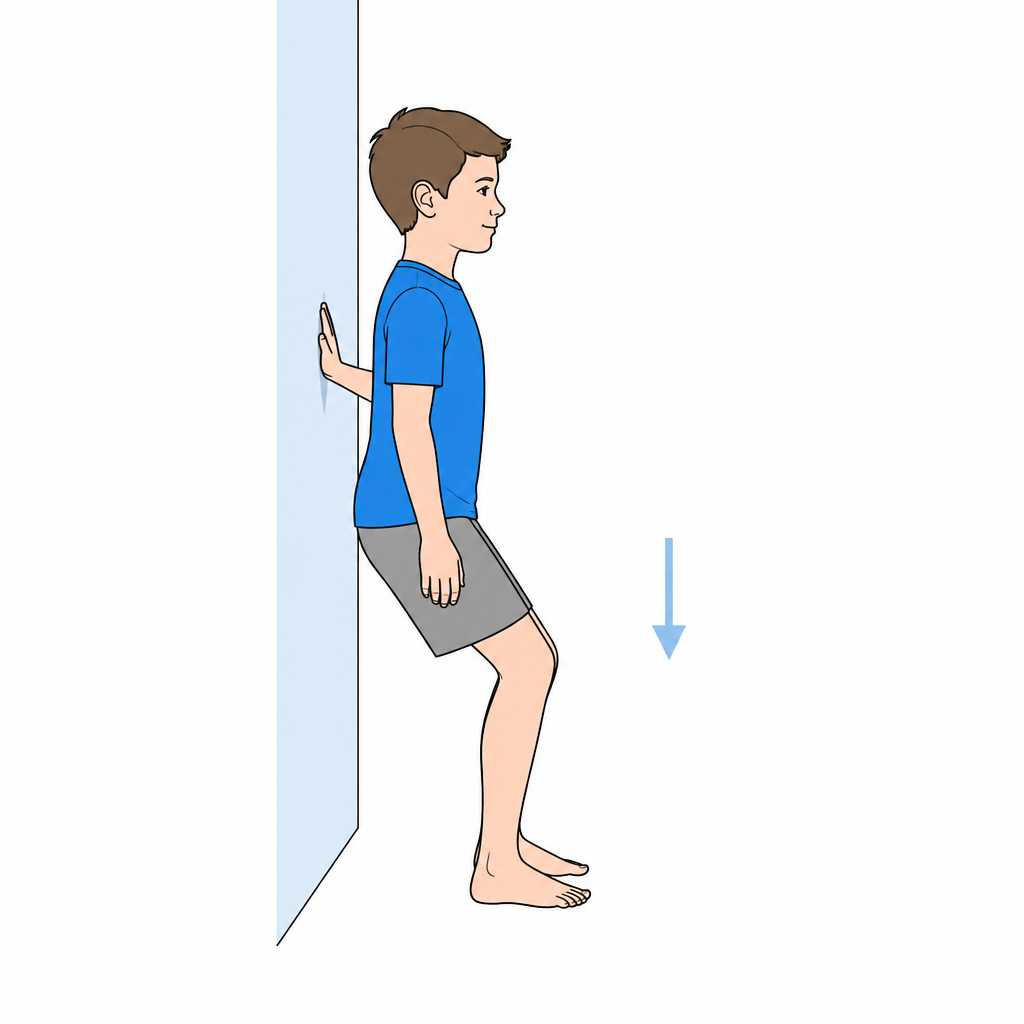
5. Mini-squat 0-45°After entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Standing, feet hip-width apart, weight evenly distributed.
- •Bend the knees to about 45°, keeping the knees aligned over the feet.
- •Rise by pushing through the heels, without letting the knee collapse inwards.
Dosage: 3 sets of 12, 3-4 times a week
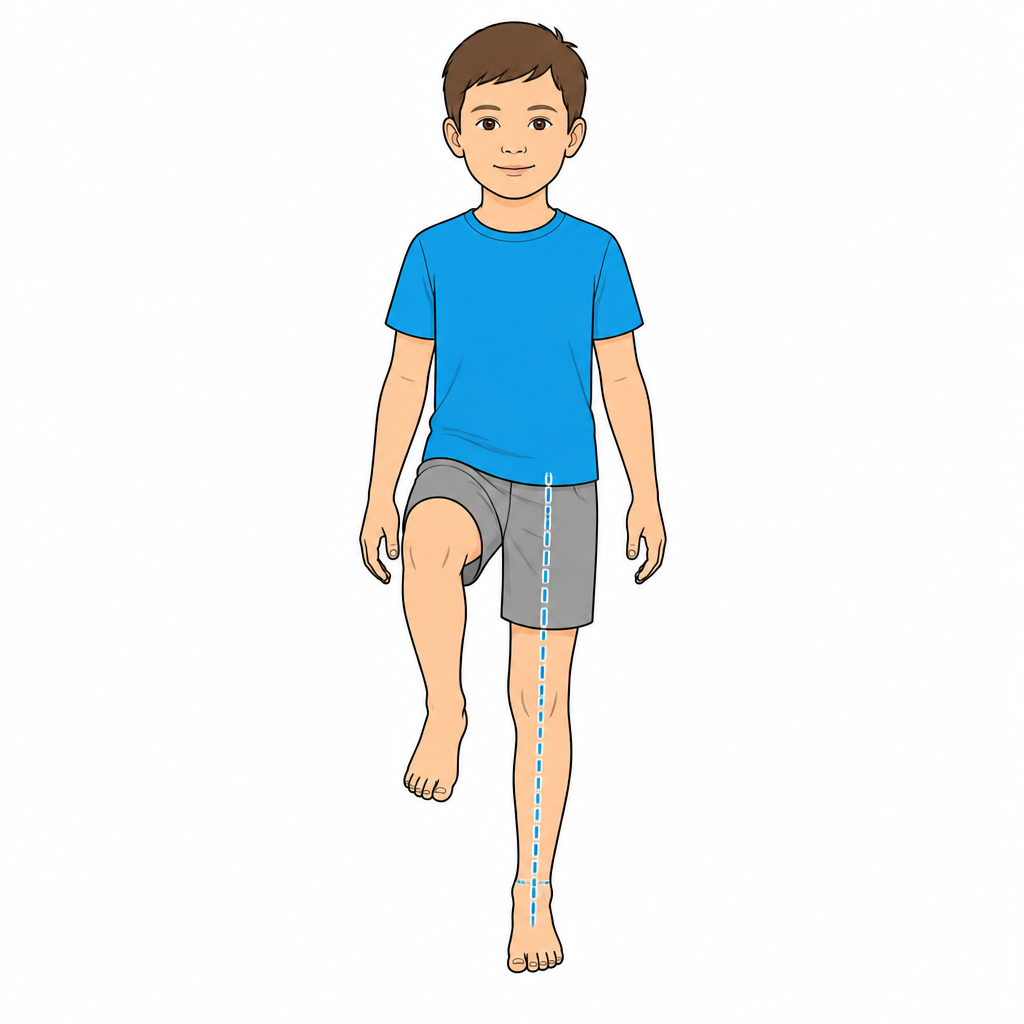
6. Single-leg balanceAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Stand on one leg with the knee slightly bent and look ahead, after clearance for weight bearing.
- •Keep your eyes open on firm ground near a stable support; an adult must be able to assist the child.
- •Aim to keep your pelvis steady. If it tilts or you lose balance, put the other foot down, reduce the difficulty and ask your physiotherapist to check the movement.
Dosage: 3 x 30 seconds per side, daily

7. Low-impact conditioningAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Stationary bike with high saddle and minimal resistance, swimming (avoiding breaststroke early), elliptical.
- •Select cycling, pool exercise or other low-impact activity with your physiotherapist within the permitted load, range and resistance. Low impact does not mean no compression of the repaired area.
- •The rule is always the same: no swelling the next day.
Dosage: 20-30 minutes, 3-5 times a week
Ready for the next phase when
- ☐Recovered ROM without joint-line pain
- ☐No reactive effusion
- ☐Adequate strength and control on tests selected by the physiotherapist
- ☐Permission to introduce impact
Phase 4 — Impact and return to sport
Indicative timing: Not before month 4; often 6-9 months for complex, radial or root repairs
The time window is indicative: progression depends on the criteria listed below, not on the calendar.
Goals
- •Tolerate progressive impact and sport-specific tasks
- •Recover strength and confidence
What to do
- •Straight-line running after clearance, then progressive jumping and direction changes
- •Individual training, then full team training before competition
- •Maintain strength and manage loading
Restrictions and precautions
- •Reduce loading and reassess joint-line pain, effusion or mechanical symptoms
Exercises for this phase
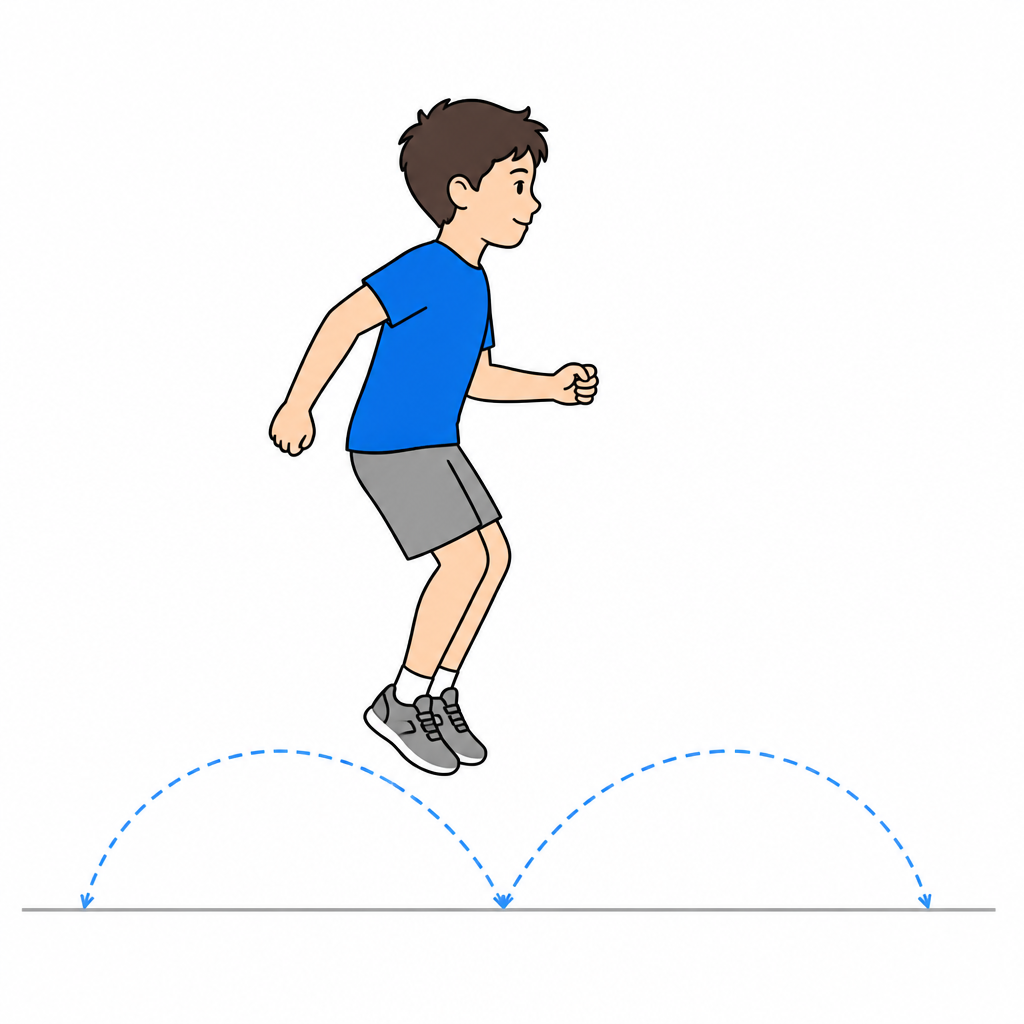
8. Progressive plyometricsAfter entering the indicated phase and receiving clearance for this exercise; respect prescribed load and range.
- •Only after clearance for impact and demonstration by your physiotherapist, start with small two-foot hops on a stable surface.
- •Increase direction, height or single-leg work only within the agreed progression; do not add several challenges at once.
- •Aim for a controlled landing with knees and feet aligned. Stop for pain, giving way or loss of control; report swelling or worsening symptoms afterwards. Landing noise alone does not measure movement safety.
Dosage: 2-3 sets of 10-20 contacts, 2-3 times a week
Ready for the next phase when
- ☐Strength and function tests completed with sound technique
- ☐No pain, effusion or locking
- ☐Full training tolerated
- ☐Shared clearance with the surgeon
If symptoms appear after a progression
If persistent pain, effusion or swelling, or loss of movement appears after moving to a new phase or increasing load, stop progression and contact the treating clinician or physiotherapist to review the programme. Seek prompt assessment for the red flags below. This document does not replace individual clinical assessment.
Return to sport / full activity
At least 4 months for vertical repairs; commonly 6-9 months for radial, root or complex repairs, with criteria met and surgeon clearance.
- ☐Hop tests with LSI ≥90%
- ☐Quadriceps and hamstring strength LSI ≥90%
- ☐No mechanical symptoms (locking, catching) and no joint-line pain
- ☐High IKDC score
- ☐Sport-specific functional tests passed without compensation
Red flags: stop and contact us
- •Joint-line pain that persists or recurs later after surgery
- •Joint locking or inability to fully extend
- •Recurrent effusion after loading: suspected repair failure
- •Painful catching or a feeling of instability
- •Fever, redness or discharge from the surgical wound
- •Calf pain with asymmetric swelling (suspected deep vein thrombosis)
Author: Dott. Daniele Priano, Paediatric Orthopaedics. Content version: 9 September 2026.
Timings are indicative: progression depends on clinical and functional criteria and on the treating clinician’s instructions.
Full introduction and references at ortopediaevolutiva.com/en/rehabilitation/isolated-meniscal-repair
Isolated meniscal repair — Dott. Daniele Priano, Pediatric Orthopaedics · Information document: it does not replace an in-person assessment.
 Latest online version
This protocol may be used and shared for clinical and informational purposes provided that attribution to the author and to the original source is kept intact. Republishing or distributing it as one’s own work is not allowed.
Other protocols

Any questions?
For information or questions, email me or view the locations and contact details.
Email: daniele.priano@ortopediaevolutiva.com